

Written by Sarah Mitchell, Health Content Writer | Medically Reviewed by Dr. Amanda Reyes, PharmD | Last Updated: September 2026
Retatrutide while breastfeeding is not something current research supports, mainly because no studies have measured whether the peptide passes into breast milk or how it might affect a nursing infant. Retatrutide is still an investigational compound, and healthcare providers generally recommend pausing its use during lactation until more data becomes available.
Weight management peptides like Retatrutide, Semaglutide, and Tirzepatide work by mimicking hormones that regulate appetite and blood sugar, and while research on their use during pregnancy and breastfeeding continues to expand, current clinical guidance leans toward caution rather than certainty. Nursing mothers who are curious about timing, safer alternatives, or what providers actually recommend will find the details below, including why the data gap exists and how to plan a return to weight management after breastfeeding ends.
Key Takeaways
- Retatrutide while breastfeeding is not currently recommended, since no clinical studies have measured how the peptide transfers into breast milk or affects a nursing infant.
- Retatrutide remains an investigational compound, meaning long term safety data during lactation simply does not exist yet.
- Weight management peptides such as Semaglutide, Tirzepatide, and Liraglutide carry similar cautions during breastfeeding because of limited human research.
- Healthcare providers typically recommend pausing peptide therapy during breastfeeding and revisiting treatment once weaning is complete.
- Nursing mothers interested in Retatrutide should speak with a licensed healthcare provider before starting, restarting, or continuing use.
The Direct Answer: Retatrutide While Breastfeeding Is Not Currently Recommended
Every major weight management peptide, including Retatrutide, shares one thing in common when it comes to breastfeeding: an absence of controlled human data. Retatrutide is a triple agonist that targets GLP-1, GIP, and glucagon receptors, and while it has shown notable results in clinical trials for weight management, those trials have not included breastfeeding participants. Without that data, no healthcare provider can confidently state that Retatrutide is safe for a nursing infant.
This does not mean Retatrutide is proven harmful. It means the research simply has not been done. Large peptide molecules like Retatrutide are generally thought to break down in an infant’s digestive system rather than being absorbed intact, which is a reassuring pattern seen with other injectable peptides. Still, likely low risk is different from confirmed safe, and most providers prefer to wait for confirmed safety before recommending a treatment during lactation.
In practice, nursing mothers who bring up Retatrutide during a checkup are usually met with the same response from their provider: a request to wait. Providers who work with new mothers regularly see how quickly milk supply can shift with even small changes in appetite or caloric intake, which is one reason appetite suppressing peptides raise more caution than other medication categories during this stage of life.
What Retatrutide Is and Why Lactation Research Is Missing
Retatrutide belongs to a newer class of peptide therapies designed to activate three separate hormone receptors at once. This triple action is part of why Retatrutide has drawn attention in metabolic health circles, since combining GLP-1, GIP, and glucagon receptor activity may produce more pronounced effects on appetite regulation and energy expenditure than single target medications. Because Retatrutide is still investigational, questions about Retatrutide while breastfeeding come up often among mothers who are already tracking metabolic health peptides for themselves or their household.
Because Retatrutide has not gone through the years of postmarket monitoring that older medications rely on to build a breastfeeding safety profile, it simply lacks the track record that shapes clinical guidance. Medications that have been available for decades, like certain insulin formulations, have decades of real world reporting behind them. Retatrutide does not have that history yet, and lactation studies are typically among the last research priorities addressed for any new compound, since researchers usually wait for broader safety and efficacy data first.
This gap is not unique to Retatrutide. Newer medications across many drug classes, not just weight management peptides, tend to carry a similar wait and see label until enough nursing mothers have used them under medical supervision for researchers to draw reliable conclusions. For a compound as new as Retatrutide, that process is still in its early stages, which is why the guidance around Retatrutide while breastfeeding continues to be cautious rather than definitive.
Table 1: How Common Weight Management Peptides Are Viewed During Breastfeeding
| Peptide | Class | Breastfeeding Guidance |
|---|---|---|
| Retatrutide | GLP-1, GIP, and glucagon triple agonist | Not recommended, no lactation data available |
| Semaglutide | GLP-1 receptor agonist | Not recommended, limited human lactation data |
| Tirzepatide | GLP-1 and GIP dual agonist | Not recommended, limited human lactation data |
| Liraglutide | GLP-1 receptor agonist | Not recommended, insufficient lactation research |

Things To Know
- Retatrutide has a long half-life, meaning any exposure that did occur could linger in the body longer than shorter-acting medications.
- No pediatric outcome data exists for infants exposed to Retatrutide through breast milk.
- Appetite suppression from Retatrutide could reduce a nursing mother’s caloric intake, which may influence milk supply.
- Providers typically recommend waiting until breastfeeding ends before starting or resuming Retatrutide.
- Every nursing mother’s health situation is different, so individualized medical guidance should always take priority over general information found online.
Why Timing Matters After Having a Baby
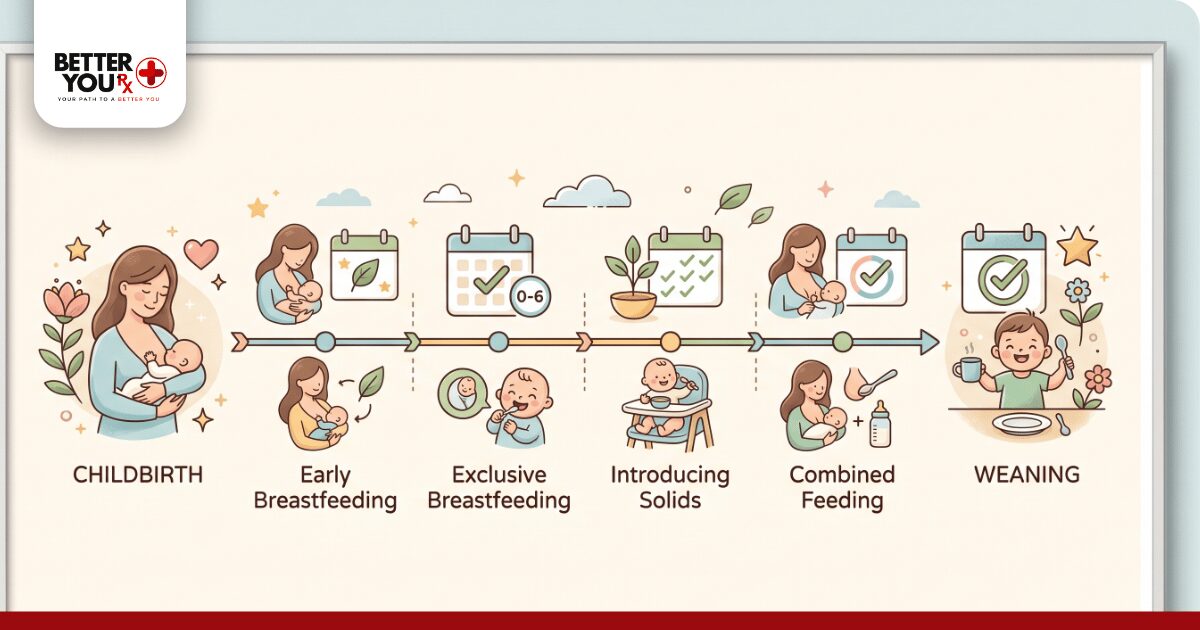
The postpartum period is a demanding stretch for any new mother, and it is common to want to jump back into a weight management routine as soon as possible. Patients often tell their providers that they feel pressure to bounce back quickly, but most clinicians actually recommend the opposite approach when a mother is breastfeeding. The body needs adequate calories and hydration to maintain milk supply, and introducing an appetite suppressing peptide during this window can work against that goal.
Most healthcare providers follow established clinical protocols when prescribing metabolic medications after childbirth, which generally means confirming that breastfeeding has ended or that a mother has chosen not to breastfeed before introducing a compound like Retatrutide. This reflects how little is known about Retatrutide while breastfeeding and how sensitive infant development is during the first year of life. It is not a punishment or a delay for its own sake.
For example, a mother who is six months into breastfeeding and beginning to introduce solid foods to her baby may find her provider is more open to a conversation about timing than a mother who is exclusively nursing a newborn. Every situation is different, and factors like how often a baby is nursing, whether supplementation is already part of the routine, and a mother’s overall health history all shape that conversation.
Table 2: Postpartum Weight Management Timeline
| Stage | What To Focus On | When Peptide Therapy May Be Considered |
|---|---|---|
| First 6 weeks postpartum | Recovery, hydration, establishing milk supply | Not appropriate during this stage |
| Active breastfeeding | Maintaining caloric intake and hydration for milk production | Generally paused until weaning |
| Weaning process | Gradual reduction in nursing sessions | Discuss timing with a provider |
| After breastfeeding ends | Full return to personal health goals | May be reintroduced with medical guidance |
Which Option Is Best for Nursing Mothers Who Want To Manage Weight
For mothers who are breastfeeding and still want to work toward their weight goals, the safest path usually starts with the basics: balanced nutrition, gentle movement once cleared by a provider, adequate sleep when possible, and support from a lactation consultant if milk supply is a concern. These strategies will not replicate the results of a peptide like Retatrutide, but they do not carry the same uncertainty either.
Some mothers ask about switching to an older, more established medication instead of waiting entirely. This is a conversation worth having with a provider, since a small number of diabetes medications have a longer track record during lactation than newer weight management peptides. That said, most weight focused GLP-1 and multi-agonist options, including Retatrutide, Semaglutide, and Tirzepatide, are generally placed in the same wait until after breastfeeding category by prescribers, because the newer the compound, the less real world exposure data exists. A licensed healthcare provider connected through a prescription referral service like Better You Rx can help evaluate timing and options based on individual health history.
Once breastfeeding has ended, many women revisit their options with a provider. Medications like Saxenda, Wegovy, and Mounjaro are commonly discussed alternatives once a mother is cleared to resume weight management treatment, and a provider can help determine which option fits a person’s health history and goals.
Buy Wegovy from Canada
Original price was: $609.99.$596.99Current price is: $596.99.
For readers comparing Retatrutide to other peptides before or after breastfeeding, the Retatrutide vs Tirzepatide comparison walks through how the two compounds differ, while the Retatrutide side effects overview covers what to expect once treatment resumes. Readers who are still early in their research may also find the what does Retatrutide do explainer helpful for understanding the basics before scheduling a consultation.
Common Misconceptions About Retatrutide While Breastfeeding
“If it works for weight loss, it must be fine in small amounts while nursing.” Peptides do not work like over the counter supplements, and small amounts is not a standard that has been studied for Retatrutide during lactation. Even minimal exposure has not been evaluated in nursing infants, so there is no dose considered confirmed safe.
“Pumping and dumping after a dose solves the problem.” Because Retatrutide has a long half-life lasting several days, a single pumping session will not clear it from the body the way it might with a fast acting medication. This makes short term workarounds far less effective for long acting peptides.
“Natural supplements are a safer substitute while breastfeeding.” Many appetite suppressing supplements marketed as natural have even less regulation and research behind them than prescription peptides. Assuming a product is safer because it is labeled natural is not supported by available evidence.
Wrapping Up: What This Means for Nursing Mothers
Retatrutide while breastfeeding is not a combination that current research supports, and the most honest, helpful answer for nursing mothers is to pause peptide therapy until breastfeeding ends. This is not about restricting a mother’s options forever. It is about protecting a nursing infant during a stage of life when almost nothing is known about how these newer peptides interact with breast milk. Waiting a matter of months, while relying on safer and well established strategies in the meantime, protects both weight management goals and a baby’s wellbeing. For more information on breastfeeding and medication safety in general, Mayo Clinic’s guide to breastfeeding and medications offers additional context.
Frequently Asked Questions About Retatrutide While Breastfeeding
Can I take reta peptides while breastfeeding?
No, reta peptides are not recommended while breastfeeding. Reta peptides, including Retatrutide, carry the same caution as any other newer peptide during lactation, since no confirmed safety data exists yet.
Can I take weight loss peptides while breastfeeding?
No, most weight loss peptides are not recommended during breastfeeding. This includes Retatrutide, Semaglutide, and Tirzepatide, since none of these compounds have enough lactation research to confirm safety. Diet, movement, and provider support are safer options while nursing.
Can I take retatrutide after having a baby?
Yes, but typically only after breastfeeding has ended. Once a mother has weaned or chosen not to breastfeed, a provider can evaluate whether Retatrutide fits her individual health history and goals.
Are any GLP-1 safe for breastfeeding?
Currently, no GLP-1 medication has confirmed safety data for breastfeeding. Semaglutide, Tirzepatide, and Retatrutide are all generally placed in the same insufficient data category, so providers typically recommend pausing this medication class during lactation.
Can breastfeeding moms take peptides?
Most peptide therapies, including weight management options, are not recommended for breastfeeding mothers. Exceptions are decided case by case with a provider, since a small number of older, well studied medications may be considered when medically appropriate.
Sources
- Mayo Clinic – Breastfeeding and Medications: What’s Safe, an overview of how medications interact with lactation and breast milk transfer.
- Journal of Human Lactation – Peer reviewed research on peptide and hormone therapy considerations during breastfeeding.
- American Family Physician – Clinical guidance on medication safety and prescribing decisions during lactation.
- Academy of Breastfeeding Medicine – Clinical protocols addressing maternal medication use while nursing.
Medical Disclaimer
This article is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or changing any medication or treatment, including during pregnancy or breastfeeding. Better You Rx is a prescription referral service with a licensed contracted dispensing department, and does not provide medical advice.

