What Does Retatrutide Fertility Evidence Actually Show

Written by Sarah Mitchell, Health and Wellness Content Writer | Medically Reviewed by Dr. Angela Torres, MD

Last Updated: September 2026

Retatrutide fertility research in humans is essentially nonexistent, since the compound remains investigational and has not been evaluated for reproductive safety in completed trials. What is documented instead comes from related GLP-1 medications: weight loss and improved insulin sensitivity can restore ovulation in people whose infertility was tied to obesity or polycystic ovary syndrome, which explains why some patients have conceived unexpectedly during treatment.

Retatrutide itself has not been studied specifically for fertility outcomes, and no clinical guidance supports using it, or any GLP-1 based compound, as a way to improve conception chances. For anyone trying to get pregnant, or hoping to avoid pregnancy, understanding how these medications interact with the reproductive system matters more than assuming fertility will simply improve or decline.

Key Takeaways

  • Retatrutide fertility data in humans does not currently exist in any meaningful way, since the compound is still investigational and has not completed the trial stages needed for reproductive safety conclusions.
  • Significant weight loss achieved through GLP-1 based treatments can restore ovulation in people with obesity-related infertility, which may unintentionally raise the chance of pregnancy during treatment.
  • Reports of unplanned pregnancies during GLP-1 receptor agonist use reflect improved metabolic and hormonal function rather than a fertility-boosting property of the medication itself.
  • No established clinical guidance recommends using Retatrutide, Tirzepatide, or Semaglutide as a fertility treatment, and healthcare providers do not prescribe these medications for that purpose.
  • Anyone actively trying to conceive should discuss timing, contraception, and medication discontinuation with a licensed healthcare provider before starting or continuing any GLP-1 based therapy.

The Direct Answer On Retatrutide And Fertility

No dedicated human studies have measured retatrutide fertility outcomes directly. Everything currently understood is borrowed from research on related GLP-1 based compounds like Semaglutide and Tirzepatide, since Retatrutide combines similar receptor targets and produces comparable weight loss and metabolic effects. Animal studies conducted during Retatrutide’s investigational development have shown developmental risks at exposures relevant to humans, which is a standard reason these compounds are not recommended during pregnancy. Until dedicated reproductive studies are completed, the responsible approach treats Retatrutide the same way any other unproven weight management compound would be treated around conception: with caution, medical supervision, and a clear discontinuation plan.

What Retatrutide Actually Is And How It Works

Retatrutide is an investigational compound designed to activate three separate metabolic receptors at once: GLP-1, GIP, and glucagon. This triple-action approach is why early research has shown more pronounced weight loss compared to medications that target only one or two of these pathways. Because it works primarily on appetite regulation, blood sugar control, and energy expenditure, Retatrutide was developed with metabolic health as the goal, not reproductive health. Its investigational status means dosing protocols, long-term safety profiles, and reproductive outcomes are still being studied in controlled research settings rather than established through years of everyday clinical use.

Researchers evaluating Retatrutide have focused heavily on markers like body weight, waist circumference, blood glucose, and cardiovascular risk factors, which means fertility has simply not been a primary endpoint in the studies published so far. That gap is common with newer investigational compounds, since reproductive research typically follows years behind metabolic research in the overall development timeline.

How GLP-1 Medications Have Been Linked To Unplanned Pregnancies

Stories about unexpected pregnancies during GLP-1 treatment have circulated widely, and the explanation is more straightforward than it sounds. People with obesity or polycystic ovary syndrome often experience irregular or absent ovulation. Once meaningful weight loss occurs, hormonal balance can shift enough for regular ovulation to return, sometimes within weeks. A second factor involves digestion: GLP-1 based medications slow gastric emptying, and some researchers believe this may reduce how consistently oral contraceptives are absorbed, though this has not been proven definitively for every medication in the class.

The table below compares how different GLP-1 based medications relate to fertility discussions currently circulating among patients and providers.

Medication Classification Fertility-Related Observation
Semaglutide (Ozempic, Wegovy) Approved GLP-1 receptor agonist Most documented reports of ovulation returning after weight loss
Tirzepatide (Mounjaro, Zepbound) Approved dual GIP/GLP-1 agonist Similar ovulation-related reports, fewer published cases than Semaglutide
Liraglutide (Saxenda, Victoza) Approved GLP-1 receptor agonist Early GLP-1 medication with the longest history of anecdotal fertility discussion
Retatrutide Investigational triple agonist No completed fertility studies, mechanism assumed similar to approved GLP-1 medications

Patients researching options often compare Ozempic and Wegovy alongside Mounjaro when discussing how GLP-1 based weight loss might intersect with fertility timelines, even though none of these medications are prescribed specifically to treat infertility.


Retatrutide Fertility Retatrutide Fertility Considerations For Women Trying To ConceiveThings To Know

  • Retatrutide has not completed the clinical development stages required before reproductive safety data becomes available.
  • Animal studies on similar GLP-1 based compounds have shown fetal risk at exposures relevant to humans, which is why these medications list pregnancy avoidance during use.
  • Ovulation can return within weeks of significant weight loss, sometimes before a person notices their cycle has changed.
  • Contraception should not be assumed to work exactly the same way during treatment with medications that slow digestion.
  • A licensed healthcare provider can advise on stopping a GLP-1 based medication a reasonable period before attempting conception.

Retatrutide Fertility Considerations For Women Trying To Conceive

Retatrutide fertility planning starts with a conversation, not a calendar. Because reproductive safety data for this specific compound does not exist yet, healthcare providers generally apply the same caution used with other investigational or recently approved GLP-1 medications. Many providers recommend discontinuing GLP-1 based treatment a set period before actively trying to conceive, giving the body time to clear the medication and return to its baseline metabolic state. This timing conversation belongs with a licensed healthcare provider who understands a patient’s full medical history, not a general rule applied the same way to everyone.

Consideration What It Means For Retatrutide Fertility Planning
Investigational status No completed human studies exist on reproductive safety or fertility outcomes
Weight loss and ovulation Restored ovulation is possible as a side effect of weight change, not a direct drug action
Contraceptive reliability Delayed digestion may affect how consistently oral contraceptives are absorbed
Provider consultation timing A licensed provider determines an appropriate discontinuation window before conception


What About Male Fertility And Retatrutide

Most public discussion around GLP-1 based medications and reproduction focuses on women, but male fertility deserves attention too. Obesity is independently associated with lower testosterone levels and reduced sperm quality in men, and meaningful weight loss has been shown in some studies to improve both. Because Retatrutide produces substantial weight loss in early research, it is reasonable to expect similar indirect benefits for men managing obesity-related fertility concerns, though no dedicated studies have confirmed this specifically for Retatrutide. As with women, any male patient considering this medication while planning a pregnancy with a partner should raise the topic directly with their prescribing provider rather than assuming a particular outcome.

Why Weight Loss Itself May Influence Fertility Outcomes

Weight and fertility are more closely connected than many people realize. Excess body weight can disrupt the hormonal signals that regulate ovulation, particularly in people with polycystic ovary syndrome, a condition Cleveland Clinic describes in detail as a common cause of irregular cycles and reduced fertility. Patients who have struggled with PCOS-related infertility for years often report their cycles becoming more regular within a few months of meaningful weight loss, a pattern providers frequently observe with GLP-1 based treatment regardless of which specific compound is involved.

This is not unique to retatrutide fertility discussions specifically; it reflects a broader relationship between metabolic health and reproductive hormone balance that has been documented across multiple weight management approaches. Most healthcare providers follow established clinical protocols when evaluating whether a GLP-1 based medication is appropriate for someone who is pregnant, breastfeeding, or actively trying to conceive. In everyday practice, this usually looks like a straightforward conversation at a routine visit rather than a formal referral, since providers are accustomed to weighing metabolic treatment goals against a patient’s reproductive timeline.

Retatrutide Fertility Considerations For Women Trying To Conceive

What The Research Gaps Mean For Family Planning Decisions

Because Retatrutide remains investigational, questions about its long-term reproductive effects will not be fully answered until more research is completed and published through standard scientific channels. Patients who search for retatrutide fertility information today are essentially looking ahead of the available evidence, which is a reasonable thing to do as long as the limits of that evidence are kept in view.

Better You Rx, a prescription referral service with a licensed contracted dispensing department, only facilitates access to medications once a qualified healthcare provider has issued an appropriate prescription within the United States. For patients whose healthcare provider has recommended an approved GLP-1 based option while questions about family planning timing are resolved, the following options are commonly discussed:

Readers interested in learning more about this compound can review documented retatrutide benefits, explore reported retatrutide side effects, or read a broader overview of what does retatrutide do to understand how it compares with approved GLP-1 medications.

Moving Forward With Retatrutide And Family Planning

Retatrutide fertility conversations are still catching up to the pace of the compound’s growing popularity. Until dedicated reproductive studies are completed, the safest approach treats Retatrutide like any other GLP-1 based therapy that lacks pregnancy safety data: pause it, confirm timing with a provider, and rely on dependable contraception if pregnancy is not the current goal. Working with a licensed healthcare provider remains the safest path forward, and services like Better You Rx exist to connect patients with a licensed contracted dispensing department once a valid prescription has been issued by a provider practicing within the United States.

Frequently Asked Questions

Has anyone got pregnant on retatrutide?

No confirmed pregnancies have been documented in Retatrutide’s investigational trials that link the medication directly to improved fertility. Reports of pregnancy during use of related GLP-1 medications exist, but these are generally attributed to restored ovulation following weight loss rather than a specific fertility effect of the drug itself.

Can you take retatrutide if you want to get pregnant?

Most healthcare providers do not recommend starting or continuing Retatrutide while pregnancy is being planned. Because reproductive safety data remains incomplete, providers typically advise discontinuing GLP-1 based medications and discussing alternative, better-documented options before attempting conception.

Do peptides affect fertility?

Some peptides can influence fertility indirectly by changing weight, insulin levels, or hormone balance. Retatrutide fertility effects specifically have not been studied, but its metabolic actions mirror other peptide-based compounds known to affect ovulation through weight change.

Do GLP-1 make you more fertile?

GLP-1 medications do not directly increase fertility, but weight loss from these drugs can restore ovulation in some people. This effect is most notable in individuals with obesity-related infertility or polycystic ovary syndrome, where hormonal balance often improves as weight decreases.

Does retatrutide make you more fertile?

There is no evidence that Retatrutide directly increases fertility. Any fertility change would most likely come from associated weight loss and metabolic improvement, not from a unique reproductive effect of the compound itself.

Sources

  • Journal of Clinical Endocrinology and Metabolism – Research on GLP-1 receptor agonists, weight loss, and reproductive hormone changes.
  • Cleveland Clinic – Patient information on polycystic ovary syndrome, obesity-related infertility, and metabolic health.
  • Fertility and Sterility – Peer-reviewed studies on ovulation restoration following significant weight loss.
  • Obesity Reviews – Analysis of incretin-based therapies including triple agonist compounds such as Retatrutide.

Medical Disclaimer: This content is provided for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or changing any medication, including any GLP-1 based treatment, particularly when family planning, pregnancy, or fertility is a consideration.

Can You Take Retatrutide and Antidepressants Together Safely?

Written by Jessica Hale, Health Content Writer | Medically Reviewed by Dr. Marcus Reyes, PharmD | Updated: September 2026

Last Updated: September 2026

Retatrutide and antidepressants are generally considered compatible when a licensed provider is managing both prescriptions. No major interaction has been established between Retatrutide and standard antidepressant classes such as SSRIs, SNRIs, or atypical antidepressants. That said, appetite suppression, slowed gastric emptying, and shifts in mood or energy that come with rapid weight loss can influence how someone experiences their antidepressant, which is why coordinated care between prescribers matters more than the drug interaction itself.

Key Takeaways

  • Retatrutide and antidepressants are not known to have a dangerous drug-drug interaction, and many patients use both under provider supervision
  • Appetite, weight, and gastrointestinal changes from Retatrutide can affect how certain antidepressants are absorbed or tolerated, which is why timing and monitoring matter
  • Some antidepressants, particularly those linked to weight gain or appetite stimulation, may work against the metabolic goals of Retatrutide therapy
  • Mood changes reported during Retatrutide treatment are more often tied to rapid weight loss, reduced appetite, or nutrient shifts than to the medication acting directly on brain chemistry
  • A licensed prescriber should always review a full medication list, including antidepressants, before starting Retatrutide therapy

Is It Safe to Combine Retatrutide and Antidepressants

Is It Safe to Combine Retatrutide and Antidepressants?

For most people, yes. Retatrutide is an investigational triple agonist that targets GLP-1, GIP, and glucagon receptors, and it works primarily on appetite regulation and metabolic signaling rather than on serotonin, dopamine, or norepinephrine pathways that antidepressants target. Because the two medication classes act through different biological systems, there is no established pharmacological conflict that would prevent someone from taking both.

The more relevant consideration is practical, not chemical. Retatrutide slows digestion and reduces appetite significantly, and some antidepressants depend on consistent food intake or steady absorption timing to work as expected. A provider managing both prescriptions will typically want to know exactly which antidepressant is involved, the dosage, and how long the person has been stable on it before adding Retatrutide to the regimen.

How Retatrutide Interacts With the Body Differently Than Antidepressants

Retatrutide reduces appetite by slowing stomach emptying and signaling fullness to the brain through metabolic hormone pathways. Antidepressants, by contrast, work by adjusting the availability of neurotransmitters like serotonin or norepinephrine in the brain. Because the mechanisms are separate, Retatrutide and antidepressants are not expected to compete for the same receptors or metabolic pathways in a way that would cause a classic drug interaction.

Where the two can indirectly affect each other is through the gut. Retatrutide slows gastric emptying, and this delayed digestion can theoretically change how quickly an oral antidepressant is absorbed. In practice, most patients on stable antidepressant doses do not report a meaningful difference, but anyone starting Retatrutide while on a newer or recently adjusted antidepressant dose should mention it to their prescriber so absorption changes can be monitored if needed.

Antidepressant Class Common Examples Interaction Notes With Retatrutide
SSRIs Lexapro, Zoloft, Prozac No known direct interaction; monitor appetite and GI tolerance
SNRIs Cymbalta, Effexor No known direct interaction; watch for nausea overlap
Atypical Antidepressants Wellbutrin, Remeron Wellbutrin may support weight goals; Remeron may increase appetite
Tricyclic Antidepressants Amitriptyline, Nortriptyline Slower gut motility from both drugs may compound constipation

Things To Know

  • Retatrutide does not directly alter serotonin or dopamine levels, so it is not classified as having a pharmacological conflict with antidepressants
  • Nausea is a common side effect of both Retatrutide and several antidepressant classes, so overlapping symptoms are not unusual in the first few weeks
  • Weight-neutral or weight-loss-supportive antidepressants, such as Wellbutrin, are sometimes preferred by providers for patients also pursuing metabolic treatment
  • Appetite-stimulating antidepressants, such as Remeron or Mirtazapine, may partially offset the appetite reduction Retatrutide is intended to produce
  • Any dosage adjustment to either medication should happen gradually and under provider guidance, not on a self-directed timeline

Why Mood and Energy Changes Get Attributed to Retatrutide

Patients sometimes report feeling more emotionally flat, irritable, or fatigued after starting Retatrutide, and it is easy to assume the medication is affecting mental health directly. In most documented cases, these shifts trace back to rapid changes in eating patterns, reduced caloric intake, or fluctuations in blood sugar rather than a direct neurological effect. A person eating significantly less than usual, particularly in the first several weeks of treatment, may experience low energy or mood dips simply from the adjustment period, and this pattern is something providers commonly observe when patients begin any GLP-1-class or multi-agonist therapy.

This is one reason providers managing both Retatrutide and antidepressants often ask patients to track mood alongside appetite and weight during the early titration phase. Distinguishing between an expected adjustment period and something that needs medical attention is easier when there is a clear record to review together. Most healthcare providers follow established clinical protocols when prescribing metabolic medications alongside existing psychiatric treatment, which typically includes a check-in schedule during the first two to three months.

Which Antidepressants Pair Best With Retatrutide

Not every antidepressant interacts with weight-focused treatment the same way, and this is often the more practical question patients bring to their providers. The table below outlines general tendencies, though individual response always varies.

Antidepressant Typical Weight Effect Fit With Retatrutide Goals
Wellbutrin (Bupropion) Weight neutral or supportive Often considered compatible with weight management goals
Lexapro (Escitalopram) Mild to neutral weight effect Commonly used alongside GLP-1 class treatment
Zoloft (Sertraline) Mild to neutral weight effect Commonly used alongside GLP-1 class treatment
Remeron (Mirtazapine) Associated with appetite increase May work against Retatrutide’s appetite goals
Paxil (Paroxetine) More commonly linked to weight gain May require closer monitoring

Why one option tends to work better than another usually comes down to how the antidepressant affects hunger signaling and metabolism on its own. How a provider decides which combination is appropriate depends on the patient’s full psychiatric history, how long they have been stable, and whether switching medications carries more risk than simply monitoring the current combination. Which option is ultimately best is a decision that belongs to the prescriber and patient together, not something to determine independently.

For a broader look at how Retatrutide compares to other metabolic medications, the difference between Retatrutide and Tirzepatide is worth reviewing before starting treatment. Patients weighing side effect profiles may also want to read about Retatrutide side effects and the documented benefits of Retatrutide before combining it with any existing prescription.

Is It Safe to Combine Retatrutide and Antidepressants

Getting Started With a Coordinated Treatment Plan

Anyone currently taking an antidepressant who is considering Retatrutide should start with a conversation, not a decision made alone. A licensed provider will typically review the full medication list, recent psychiatric history, and any prior reactions to appetite-related changes before approving a combined treatment plan. This is standard practice regardless of which antidepressant is involved.

Patients interested in exploring metabolic treatment options alongside their current mental health care can also look into Zepbound Kwikpen, Mounjaro Kwikpen, or Saxenda as comparable options depending on what a provider recommends. According to the Cleveland Clinic’s overview of GLP-1 medications, coordinating any new metabolic prescription with existing mental health treatment is a routine part of safe prescribing.

The Bottom Line on Retatrutide and Antidepressants

Combining Retatrutide and antidepressants is common practice for patients managing both metabolic and mental health goals, and no established interaction makes the pairing unsafe on its own. The details that matter most are which antidepressant is involved, how appetite and digestion changes are tracked, and whether a provider is actively coordinating both prescriptions. Patients considering Retatrutide and antidepressants together should treat that conversation with their prescriber as the first step, not an afterthought.

Better You Rx is a prescription referral service with a licensed contracted dispensing department, connecting patients across the United States with the medications their provider prescribes. Prescriptions must be issued in English by a primary care physician or licensed medical doctor practicing within the United States, and orders are mailed directly to the patient’s residence for personal use only.

Frequently Asked Questions

What medications cannot be taken with Retatrutide?

There is no long list of medications strictly prohibited with Retatrutide, but insulin, sulfonylureas, and certain oral medications requiring precise absorption timing need closer monitoring. A provider reviewing a full medication list is the safest way to confirm compatibility before starting treatment.

Can you take a GLP-1 while on antidepressants?

Yes, GLP-1 class medications and antidepressants are commonly prescribed together without a known dangerous interaction. Providers typically monitor appetite, mood, and gastrointestinal symptoms during the first few months of combined use.

Can I take Retatrutide with Lexapro?

Retatrutide and Lexapro do not have a known direct drug interaction and are frequently used together under provider supervision. Lexapro’s relatively weight-neutral profile makes it a common pairing for patients pursuing metabolic treatment.

Does Retatrutide affect mental health?

Retatrutide is not classified as acting directly on brain chemistry, but rapid appetite and weight changes can indirectly affect mood and energy. Tracking these changes with a provider helps distinguish normal adjustment from something needing attention.

Can Retatrutide help with anxiety?

Retatrutide is not approved or studied as an anxiety treatment, and it should not replace prescribed anxiety medication. Any anxiety-related symptoms during treatment should be discussed directly with a prescribing provider.

Sources

  1. New England Journal of Medicine — Clinical trial data on multi-agonist and GLP-1 receptor pathway medications for weight management.
  2. Cleveland Clinic — Patient overview of GLP-1 agonist medications, mechanisms, and monitoring considerations.
  3. Mayo Clinic — Reference guide on antidepressant classes, side effects, and weight-related considerations.
  4. Journal of Clinical Psychiatry — Research on antidepressant selection and metabolic side effect profiles.
  5. American Diabetes Association Clinical Compendium — Guidance on incretin-based therapies and concurrent medication management.

This content is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or combining any medication, including Retatrutide or antidepressants.


What Is the Best Ozempic Online Canada Option? Pricing and What to Look For

Written by Sarah Mitchell, Health Content Writer | Medically Reviewed by Dr. James Coleman, MD | Updated: June 2026

Last Updated: June 2026

The best Ozempic online Canada option comes down to dose accuracy, transparent pricing, and a process built around a valid prescription. Both available Ozempic pens are priced the same, which makes comparing the best Ozempic online sources more straightforward for patients. People searching for the best Ozempic online route usually want clarity on what affects pricing, what documentation is required, and how the medication actually reaches them. Semaglutide, the active ingredient in Ozempic, is widely prescribed for blood sugar management and weight support, and understanding what separates the best Ozempic online experience from a confusing one helps patients move forward with confidence.

Things To Know

  • The best Ozempic online Canada sources require a valid prescription written in English by a USA-based doctor.
  • Dose strength is the main factor that determines what patients receive, not the price, since both pens are priced the same.
  • The best Ozempic online Canada process involves shipping directly to a patient’s residence, not to a clinic or office.
  • Compounded semaglutide alternatives exist and may be discussed with a doctor as part of treatment planning.
  • Supply availability can occasionally affect timing, so planning ahead matters.

What Makes Something the Best Ozempic Online Option?

When patients look for the best Ozempic online option, they’re usually weighing a few things at once: price, prescription requirements, and how quickly the medication arrives. The best Ozempic online Canada sources are upfront about all three from the start.

Dose strength plays a major role here. Ozempic is available in different pen sizes depending on where a patient is in their treatment plan. The best Ozempic online Canada process makes it clear which pen corresponds to which dose, so there’s no guesswork involved when a prescription is submitted.

Working with a prescription referral service that has a licensed contracted dispensing department tends to be the best Ozempic online Canada path for patients who want consistency. Because Better You Rx operates this way, the pricing patients see reflects exactly what they’ll pay, without surprises added later in the process.

Current Ozempic Pricing

Dose Strength Pen Description Price
0.25mg/0.5mg Ozempic 2mg/3ml, 1 Pen $327.99
1mg Ozempic 4mg/3ml, 1 Pen $327.99

A valid prescription from a USA-based primary care physician or licensed medical doctor, written in English, is required to move forward. This keeps the best Ozempic online experience grounded in a process that’s both consistent and compliant.

Why Prescription Requirements Matter for the Best Ozempic Online Experience

Not every source that claims to offer the best Ozempic online Canada deal actually requires a prescription, which can be a red flag. A prescription ensures the dose, frequency, and overall treatment plan are determined by a doctor who knows the patient’s medical history, not by guesswork.

For the best Ozempic online Canada experience, the prescription must come from a primary care physician or licensed medical doctor practicing in the USA. Documentation written in a language other than English cannot be processed, since accuracy in dosing instructions is critical.

Healthcare providers who prescribe semaglutide medications often follow established clinical protocols that start patients on a lower dose before adjusting upward based on response. This is part of why the best Ozempic online process should always begin with a doctor’s evaluation rather than skipping straight to an order.

Best Ozempic Online Canada

How Ozempic Compares to Other Options When Searching for the Best Online Deal

Patients exploring the best Ozempic online Canada route sometimes compare Ozempic to other GLP-1 medications to understand how pricing and purpose differ across options.

Medication Primary Use General Price Range
Ozempic Blood sugar management, weight support $327.99 (per pen, dose-dependent)
Wegovy Weight management Varies by dose
Mounjaro Blood sugar management, weight support Varies by dose

Those researching Ozempic vs Trulicity often want to see how the best Ozempic online pricing stacks up against other injectable options before raising the topic with their doctor. Similarly, patients comparing Mounjaro vs Trulicity are typically weighing long-term cost against how each medication aligns with their treatment goals.

Which Option Is Actually the Best Ozempic Online Choice?

For patients just starting semaglutide treatment, the lower dose pen is typically the starting point, and since both pens are priced identically, the best Ozempic online choice at this stage is simply the one matching the doctor’s prescription, not a price comparison.

For patients who have progressed to a higher dose, the best Ozempic online option remains just as accessible, since the price doesn’t change between the two available strengths. This removes one layer of decision-making, letting patients focus on following their doctor’s dosing schedule rather than budgeting around price jumps.

In most cases, the best Ozempic online path for USA-based patients is a prescription referral service connected to a licensed contracted dispensing department, where a valid English-language prescription from a primary care physician or licensed medical doctor leads to medication shipped directly to the patient’s residence for personal use.

What to Have Ready Before You Order

Before searching for the best Ozempic online option, patients should confirm they have a current prescription on hand. It must be issued by a licensed medical doctor practicing in the USA and written in English. Orders are shipped only to the patient’s residence, not to a clinic, medical office, or hospital, and are intended for personal use.

Patients managing multiple conditions sometimes ask how Ozempic fits alongside other medications. Those also prescribed Metformin for blood sugar support, for example, may want to discuss timing and coordination with their doctor as part of an overall plan.

For a closer look at dose options, the Ozempic product page lays out what’s currently available, which can help patients prepare questions for their next doctor visit. Patients curious about broader weight management approaches sometimes also read about Saxenda vs Ozempic for additional context.

A Realistic Look at the Process

Many patients say that once they understand what the best Ozempic online Canada process actually involves, the search feels far less complicated. A common scenario is a patient who receives a new prescription, searches around to compare pricing, and finds that a referral service with clear pricing and dosing information removes most of the guesswork.

Practical tip: Before placing an order, double-check the dose strength listed on your prescription against the pen description. This small step helps confirm that what arrives matches exactly what your doctor intended.

Timing also matters. Since pricing reflects the pen itself rather than a recurring fee, patients benefit from ordering with enough lead time before their current supply runs low, particularly with shipping times factored in. Patients managing other prescriptions, such as those also taking Crestor for cholesterol, often find it easier to plan refills around a similar schedule to reduce the number of separate orders.

Why Prescription Requirements Matter for the Best Ozempic Online Experience

Wrapping Up the Search for the Best Ozempic Online Option

Finding the best Ozempic online option really comes down to three things: a valid prescription, transparent pricing, and a process that ships directly to your residence. With both available pen strengths priced the same at Better You Rx, patients can spend less time comparing numbers and more time following their doctor’s guidance on dosing.

For USA-based patients with a valid English-language prescription from a primary care physician or licensed medical doctor, the best Ozempic online Canada path is a prescription referral service with a licensed contracted dispensing department, offering straightforward pricing and direct shipping for personal use. Keeping these factors in mind makes the best Ozempic online decision much simpler.

Frequently Asked Questions About Ozempic

What is the best Ozempic online option for pricing?

Both available Ozempic pens are priced at $327.99 through Better You Rx, so the best Ozempic online Canada option depends on which dose your doctor prescribes rather than price differences.

Do I need a prescription for the best Ozempic online Canada  option?

Yes. A valid prescription written in English by a primary care physician or licensed medical doctor practicing in the USA is required before any order can move forward.

Does the best Ozempic online Canada  price change with higher doses?

No. Both the 0.25mg/0.5mg and 1mg pens are priced identically, so dose adjustments don’t affect the overall price.

Can the best Ozempic online Canada order be shipped to my doctor’s office?

No. Orders are shipped directly to the patient’s residence for personal use only, not to clinics, medical offices, or hospitals.

Are there alternatives if Ozempic isn’t the right fit?

Yes. Patients sometimes discuss other options with their doctor, and comparing Wegovy vs Saxenda for weight loss can provide useful context for those considering different treatment paths.

Medical Disclaimer

This content is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or changing any medication.

Sources

  1. New England Journal of Medicine — Clinical trial data on semaglutide and its effects on blood sugar regulation and weight outcomes.
  2. Mayo Clinic — Overview of GLP-1 receptor agonist medications and their role in diabetes and weight management.
  3. American Diabetes Association — Clinical guidance on injectable medications for type 2 diabetes management.
  4. Journal of the American Medical Association (JAMA) — Research on dosing strategies and patient outcomes for semaglutide therapy.
  5. Cleveland Clinic — Patient education resources on semaglutide medications, including Ozempic, and their clinical applications.


Bydureon vs Victoza: Which GLP-1 Injection Fits Your Routine?

Written by Sarah Whitfield, Health Content Writer | Medically Reviewed by Dr. Melissa Grant, PharmD

Last Updated: August 2026

Bydureon and Victoza are both GLP-1 receptor agonists prescribed for adults managing type 2 diabetes, but they differ in how often they are taken, how quickly they act, and how consistently they lower blood sugar over time. Victoza is a daily injection that tends to produce steadier results and slightly more weight reduction, while Bydureon offers the convenience of a single weekly dose with a slower, more gradual onset. The right choice usually depends on whether someone values simplicity of routine or wants the option that has historically shown stronger glucose control.

Key Takeaways

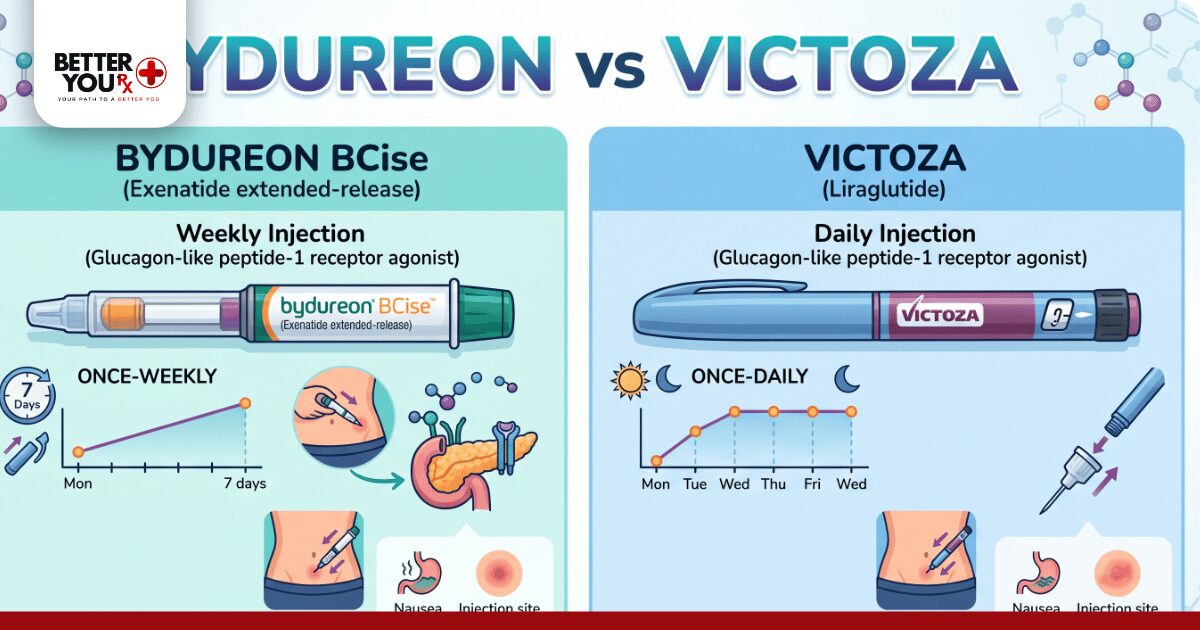
  • Bydureon (Exenatide extended-release) is a once-weekly injection, while Victoza (Liraglutide) is a once-daily injection, making dosing frequency the biggest practical difference between the two
  • Both medications belong to the GLP-1 receptor agonist class and are approved to help manage blood sugar in adults with type 2 diabetes
  • In head-to-head comparisons, Victoza has generally shown a stronger effect on blood sugar reduction and modest weight loss compared to Bydureon
  • Nausea and other digestive side effects tend to appear early with Victoza and taper off, while Bydureon’s side effects can persist longer due to its extended-release design
  • Choosing between the two often comes down to how someone prioritizes dosing convenience against symptom tolerance and glucose control goals

What Bydureon and Victoza Actually Are

Bydureon and Victoza sit in the same drug class, GLP-1 receptor agonists, but they are built on different molecules. Bydureon’s active ingredient is Exenatide, formulated as an extended-release suspension. Victoza’s active ingredient is Liraglutide, a compound that also forms the basis of the weight management medication Saxenda.

Both drugs mimic a natural gut hormone called glucagon-like peptide-1, which helps the pancreas release insulin when blood sugar rises, slows how quickly food leaves the stomach, and reduces appetite. The overlap in mechanism is part of why so many patients ask about Bydureon vs Victoza when a provider first suggests a GLP-1 medication, since the class-level effects sound similar even though the day-to-day experience of using each drug can feel quite different.

Bydureon vs Victoza: How the Dosing Schedules Compare

The most immediate difference patients notice in the Bydureon vs Victoza comparison is how often each medication is used. Victoza requires a daily injection, typically at a similar time each day, while Bydureon is designed to be injected once a week. This scheduling gap changes how each drug behaves in the bloodstream and how quickly a person feels its effects.

Because Victoza is dosed daily, blood levels of the medication stay more consistent from day to day. Bydureon’s extended-release formulation means the medication is released gradually over several days, so it can take a number of weeks before it reaches a steady effect in the body.

Feature Bydureon (Exenatide ER) Victoza (Liraglutide)
Dosing frequency Once weekly Once daily
Time to steady effect Several weeks About one to two weeks
Typical A1C reduction Moderate Moderate to strong
Average weight change Modest Modest to moderate
Common early side effect Nausea, injection site reaction Nausea, decreased appetite

Things To Know

  • Neither Bydureon nor Victoza is approved as a first-line treatment for type 1 diabetes or for managing diabetic ketoacidosis
  • Both medications are typically added to a treatment plan that already includes lifestyle changes such as diet and activity adjustments
  • Switching between a weekly and a daily GLP-1 medication should only be done under a licensed provider’s guidance, since the transition can affect blood sugar stability
  • People who struggle with remembering daily routines sometimes prefer the once-weekly option, while others like the flexibility of adjusting a daily dose based on how they feel

How Bydureon and Victoza Work in the Body

Even though Bydureon and Victoza both activate GLP-1 receptors, the way each drug is metabolized shapes the overall experience. Exenatide, the compound in Bydureon, is cleared from the body relatively quickly on its own, which is why the extended-release version relies on a special delivery system to stretch its effect across a full week. Liraglutide, the compound in Victoza, has a longer natural half-life, which is part of why a single daily dose can maintain fairly steady blood levels.
This difference matters clinically. A provider weighing Bydureon vs Victoza for a specific patient often considers how quickly blood sugar needs to come down against how much day-to-day fluctuation the person can tolerate. Some patients say the steadier daily rhythm of Victoza helps them notice appetite and glucose patterns more predictably, while others prefer how the once-weekly Bydureon dose fits into a busy schedule.

Healthcare providers who prescribe either medication generally follow established clinical protocols for titration and monitoring, adjusting the plan based on lab results and tolerance over the first several weeks.

According to the Cleveland Clinic, GLP-1 receptor agonists as a class are primarily used to improve blood sugar control in type 2 diabetes and, in certain formulations, to support weight management.

Bydureon vs Victoza

Weight Loss and Blood Sugar Results: What to Expect

Weight change is often a secondary benefit rather than the primary goal for people using Bydureon or Victoza, since both were developed mainly for glucose management. That said, appetite suppression from GLP-1 activation frequently leads to some degree of weight reduction.

In practical terms, patients using Victoza generally report slightly more consistent weight loss than those using Bydureon, though results vary based on diet, activity level, and how long someone stays on the medication. Neither drug produces the more pronounced weight loss associated with newer options like Zepbound or Wegovy, which work through different or dual-hormone mechanisms.

Category Bydureon Victoza
Primary use Type 2 diabetes management Type 2 diabetes management
Weight loss potential Modest Modest to moderate
Injection frequency Weekly Daily
Onset of noticeable effect Gradual, several weeks Faster, within days to two weeks
Related medication in same family Trulicity (Dulaglutide) Saxenda (Liraglutide, higher dose)

For people specifically comparing GLP-1 options for weight-focused goals rather than diabetes management, it may help to look at how Saxenda compares to Zepbound in this Saxenda vs Zepbound breakdown, or how Wegovy stacks up against Saxenda in this Wegovy vs Saxenda for weight loss comparison, since those pages focus more directly on weight outcomes than Bydureon or Victoza do.

Side Effects and Tolerability Differences

Digestive side effects are the most common complaint with both medications, and this is one of the more practical points people weigh when comparing Bydureon and Victoza. Nausea, mild stomach discomfort, and occasional vomiting tend to show up early with both drugs and typically settle down as the body adjusts.

Victoza’s daily dosing means side effects, when they occur, tend to appear and fade within a shorter window since the drug is cleared and reintroduced every day. Bydureon’s weekly, extended-release nature means side effects can linger longer, simply because the medication keeps releasing into the bloodstream over several days. Injection site reactions, including small lumps or redness, are also reported somewhat more often with Bydureon.

Providers typically start patients at a lower dose and increase it gradually, a standard approach with most GLP-1 medications that helps the digestive system adjust over time rather than all at once.

Things To Know

  • Report persistent vomiting, severe abdominal pain, or signs of an allergic reaction to a healthcare provider right away
  • People with a personal or family history of certain thyroid conditions are typically screened before starting either medication
  • Mild injection site bumps with Bydureon usually resolve on their own within a few weeks
  • Staying hydrated and eating smaller, more frequent meals can help ease nausea during the first few weeks on either drug

Which One Might Be the Better Fit

The honest answer to the Bydureon versus Victoza question depends on what a person values most in a treatment plan. Victoza tends to be the better fit for someone who wants steadier day-to-day control, is comfortable with a daily routine, and is looking for a medication with a somewhat stronger track record on both blood sugar and modest weight loss. Bydureon tends to suit someone who prioritizes convenience above all else, particularly those who travel frequently, have a demanding schedule, or simply find a once-weekly commitment easier to sustain than a daily one.

Why one option outperforms the other for a given patient usually comes down to individual metabolism, how consistently they manage a daily versus weekly routine, and how their body responds during the first month of use. A provider typically weighs recent lab work, current medications, and any history of digestive sensitivity before recommending one over the other, since the right medication is ultimately a shared decision between patient and provider rather than a one-size-fits-all answer.

Patients who have used both medications describe a familiar pattern: the daily habit of Victoza becomes routine within a few weeks, while the weekly Bydureon dose often needs a reminder, like a phone alarm, to avoid missing a week. Neither pattern is inherently better, but recognizing which one fits a personal routine tends to predict long-term consistency more than the clinical profile alone.

For people who are also managing insulin alongside a GLP-1 medication, understanding how the two drug classes interact is worth discussing with a provider, since options like Humalog or Humulin N are sometimes used in combination with GLP-1 therapy depending on individual blood sugar targets. Some patients on a GLP-1 already managing cholesterol or blood pressure alongside diabetes also ask their provider about Crestor as part of a broader treatment plan.

Better You Rx works as a prescription referral service connected to a licensed contracted dispensing department, helping patients in the United States access a valid prescription pathway for medications like Bydureon and Victoza once a licensed provider has determined the medication is appropriate. The overall cost of either medication can vary depending on dosage strength and quantity prescribed, which is one of the practical factors patients often discuss with their provider before starting treatment.

People newly diagnosed with type 2 diabetes sometimes also compare GLP-1 options against other diabetes medications entirely. For a broader look at how these drug classes differ, the is Trulicity a GLP-1 breakdown walks through how Dulaglutide fits into the same family as Bydureon and Victoza, while the Mounjaro vs Trulicity comparison covers how a dual-mechanism option stacks up against a traditional single-hormone GLP-1 drug.

Bydureon vs Victoza How the Dosing Schedules Compare

The Bottom Line on Bydureon and Victoza

Bydureon vs Victoza ultimately isn’t a question of one drug being universally superior. It’s a question of which weekly or daily rhythm fits a patient’s life, how their body tolerates early digestive side effects, and what their blood sugar goals look like over the following months. Victoza generally edges ahead on consistency and modest weight loss, while Bydureon wins on simplicity and reduced injection frequency.

Anyone weighing these two options should bring specific questions about dosing, side effects, and long-term goals to a licensed healthcare provider, since only a provider can evaluate personal health history and determine which medication, if either, is the appropriate next step.

Frequently Asked Questions

Do most people lose weight on Victoza?

Many people experience modest weight loss on Victoza, though it was primarily developed for blood sugar management rather than weight loss. Results vary based on dosage, diet, and activity level.

What is the difference between Victoza and insulin?

Victoza and insulin work through completely different mechanisms. Victoza stimulates the body’s own insulin release when blood sugar is elevated, while insulin directly replaces or supplements the hormone itself.

Which is more effective, GLP-1 or Semaglutide?

Semaglutide is itself a type of GLP-1 medication, so this isn’t an either-or comparison. Semaglutide-based options like Ozempic and Rybelsus are considered among the stronger performers in the GLP-1 class.

Are they discontinuing Liraglutide?

Liraglutide-based products like Victoza remain available through standard prescription channels as of this writing. Availability can shift as newer GLP-1 options enter the market, so confirm current status with a provider.

What is the cheapest GLP-1 drug I can buy without coverage?

Costs vary widely by medication, dosage, and where a prescription is filled, so there is no single cheapest option. Older GLP-1 medications like Bydureon sometimes cost less out of pocket than newer branded options.

Sources

  1. Cleveland Clinic: Overview of GLP-1 receptor agonists, how they work, and their approved uses in diabetes and weight management.
  2. Mayo Clinic: Patient education resource on type 2 diabetes treatment options, including injectable GLP-1 therapies.
  3. American Diabetes Association: Standards of care guidance on pharmacologic treatment approaches for type 2 diabetes.
  4. Journal of Clinical Endocrinology and Metabolism: Comparative research on GLP-1 receptor agonist efficacy and tolerability profiles.
  5. Diabetes Care: Published research on weight and glycemic outcomes associated with once-weekly versus once-daily GLP-1 therapy.

This article is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or changing any medication or treatment plan.

What Do Metformin Weight Loss Results Actually Look Like?

Metformin weight loss results generally land between 5 and 10 pounds over three to six months of consistent use, with some people seeing more and others barely noticing a change on the scale. The effect comes mostly from reduced appetite and better insulin sensitivity, not from any direct fat-burning action. People with prediabetes or insulin resistance tend to see the most noticeable metformin weight loss results, while those without those underlying issues often see very little movement. The numbers below break down the timeline, the factors that shape outcomes, and how Metformin stacks up against newer weight loss medications.

Key Takeaways

  • Most people see metformin weight loss results in the range of 5 to 10 pounds over three to six months, not dramatic overnight change.
  • Weight loss with Metformin happens mainly through appetite reduction and mild changes in how the body processes sugar, not direct fat burning.
  • Results vary widely based on starting weight, insulin resistance, dose, and how consistently the medication is taken.
  • Compared to GLP-1 medications like Ozempic, Metformin produces more modest results but has a much longer safety track record.
  • Belly fat and visceral fat tend to respond more noticeably than overall body weight in the first several months.

How Metformin Leads To Weight Loss In The First Place

Metformin was never designed as a weight loss drug. It was developed to lower blood sugar in people with Type 2 diabetes by reducing how much glucose the liver releases and improving how the body responds to insulin. Weight loss showed up as a side effect in clinical use, and researchers have spent decades trying to explain why it happens for some patients and not others.

The leading theory involves appetite. Metformin appears to act on the hypothalamus, the part of the brain that regulates hunger, and on gut hormones that signal fullness after eating. Many patients report eating smaller portions without consciously trying to diet, simply because they feel satisfied sooner than they used to. Gastrointestinal side effects, particularly in the first few weeks, also play a role. Nausea and mild stomach discomfort can naturally reduce calorie intake, especially at higher doses, though this effect usually fades as the body adjusts.

Insulin sensitivity is the second piece of the puzzle. When the body responds to insulin more efficiently, less of it circulates in the bloodstream. High circulating insulin levels tend to promote fat storage, so bringing those levels down can shift the body toward burning stored fat rather than holding onto it. This mechanism explains why weight change tends to be far more noticeable in people who started out with insulin resistance than in people with normal insulin function to begin with.

According to the Mayo Clinic, Metformin is primarily prescribed to manage blood sugar levels in people with Type 2 diabetes, and weight change is considered a secondary effect of improved insulin function rather than the medication’s main purpose.

Metformin Weight Loss Results By Timeline: What The Research Shows

Weight loss with Metformin does not happen in a straight line, and it rarely happens quickly. Most clinical studies that tracked metformin weight loss results over time found a similar pattern: a slow decline that builds gradually rather than a sharp drop in the first few weeks.

Timeline Average Weight Change What Is Happening
Weeks 1-4 0-2 pounds Appetite adjustment begins, possible GI side effects
Months 2-3 2-5 pounds Appetite reduction becomes more consistent
Months 4-6 5-10 pounds Insulin sensitivity improves, early plateau may begin
Months 7-12 8-15 pounds, varies widely Results often plateau unless paired with lifestyle changes
Beyond 12 months Highly individual Long-term outcomes depend heavily on diet and activity

A patient managing prediabetes on Metformin, for example, might notice their appetite shrinking around week three, then see the scale move steadily downward through month four before results level off. That plateau is common in clinical practice. Metformin is not a medication that produces continuous weight loss the way some newer GLP-1 options do. Most people reach a fairly stable range and stay there unless something else changes, whether that is dose, diet, or activity level.

Doses also matter here. Extended-release formulations, often prescribed specifically to reduce stomach upset, may produce slightly slower but steadier metformin weight loss results compared to immediate-release versions, where side effects hit harder early but taper off faster over the first month.

Metformin Weight Loss Results By Timeline

Things To Know About Metformin And Weight Loss

  • Metformin is not officially indicated as a weight loss medication, so any change on the scale is generally considered a secondary effect of treatment for insulin resistance or Type 2 diabetes.
  • Weight loss tends to be more noticeable in people with a higher starting body weight or existing insulin resistance.
  • Gastrointestinal side effects like nausea, bloating, and diarrhea are most common in the first two to four weeks and typically ease with time.
  • Extended-release Metformin generally causes fewer digestive side effects than immediate-release versions.
  • Results tend to plateau after about six months without additional dietary or activity changes.
  • Metformin does not cause the same degree of appetite suppression as GLP-1 medications like Ozempic or Wegovy.

How Much Weight Can You Realistically Lose On Metformin?

The honest answer is that metformin weight loss results are modest compared to newer prescription options, and setting realistic expectations matters. Clinical research generally places average weight loss somewhere between 2 and 7 percent of starting body weight over six to twelve months. For someone starting at 200 pounds, that translates to roughly 4 to 14 pounds, with most people landing closer to the middle of that range rather than either extreme.

Factor How It Affects Results
Starting insulin resistance Higher resistance often means more noticeable early changes
Dose Higher doses, within the prescribed range, tend to correlate with more consistent appetite reduction
Diet and activity Combining Metformin with dietary changes produces meaningfully better outcomes than medication alone
Consistency Skipping doses or stopping early resets the appetite-related effect
Underlying condition People with PCOS or prediabetes often report different results than people without a metabolic condition

Why does this matter for setting expectations? Because a medication that averages a modest reduction in body weight will simply not deliver the larger percentage losses associated with GLP-1 receptor agonists. Healthcare providers who prescribe Metformin for weight-related concerns typically frame it as a supportive tool for people managing insulin resistance, not as a primary weight loss strategy on its own. Most healthcare providers follow established clinical protocols when prescribing this medication for its metabolic benefits, treating any weight change as a welcome secondary outcome rather than the primary goal of treatment.

In practice, clinicians who manage patients on Metformin for prediabetes often describe a similar pattern: appetite softens within the first month, the scale moves slowly but steadily through mid-treatment, and then holds fairly stable unless the patient also adjusts diet or activity levels.

Metformin vs Ozempic A Side-by-Side Comparison

Metformin Vs Ozempic: Which Weight Loss Option Fits You

For people who have plateaued on Metformin or who need more significant weight loss, GLP-1 medications have become the more common next step. The two work through different mechanisms, and knowing the difference helps explain why the numbers differ so much between them.

Metformin works primarily by improving insulin sensitivity and modestly reducing appetite. Ozempic and other GLP-1 receptor agonists work by mimicking a natural gut hormone that slows digestion and strongly suppresses appetite, which is why clinical trials show average weight loss in the range of 10 to 15 percent of body weight, several times higher than what Metformin typically produces on its own.

Which option makes sense depends on the underlying goal. Someone managing early insulin resistance or prediabetes, without a strong need for significant weight loss, may find Metformin sufficient and appreciate its long safety history and lower cost. Someone whose primary goal is substantial weight loss, or who has already plateaued on Metformin, often finds a GLP-1 medication like Ozempic or Saxenda delivers results that Metformin cannot match on its own. For a closer look at how these categories compare, Saxenda vs Ozempic and Ozempic vs Trulicity break down the differences in more detail, while Wegovy vs Saxenda for weight loss covers how two GLP-1 options compare to each other.

Some healthcare providers prescribe the two together, using Metformin for its insulin-sensitizing effects and a GLP-1 medication for its stronger appetite suppression. This combination approach is increasingly common for patients managing both Type 2 diabetes and weight concerns simultaneously, and it often produces better overall metabolic outcomes than either medication used in isolation.

The Bottom Line On Metformin And Weight Loss

Metformin weight loss results are real but modest, generally landing in the 5 to 10 pound range over several months rather than delivering dramatic transformation. The medication works quietly in the background, easing appetite and improving how the body handles insulin, which makes it a reasonable option for people managing insulin resistance who also want some supportive weight change. For those seeking more significant results, pairing Metformin with lifestyle changes, or transitioning to a GLP-1 medication under medical guidance, tends to close the gap that Metformin alone cannot.

Anyone considering Metformin for weight-related concerns should work with a licensed healthcare provider to confirm it fits their health profile and current medications.

Frequently Asked Questions About Metformin Weight Loss Results

Can I Lose 20 Pounds On Metformin?

Short answer: It is possible, but not typical.

Most people see a total of 5 to 15 pounds over six to twelve months. A 20-pound loss usually requires a higher starting body weight, significant insulin resistance, and consistent dietary changes alongside the medication.

How Quickly Does Metformin Cause Weight Loss?

Short answer: Changes usually begin within four to six weeks.

Appetite reduction is often the first noticeable effect, with measurable weight change typically appearing by month two or three and continuing gradually through month six.

Has Anyone Actually Lost Weight On Metformin?

Yes, this is well documented in clinical research.

Multiple studies tracking Metformin in people with prediabetes and Type 2 diabetes report average losses between 2 and 7 percent of body weight over six to twelve months.

Which Is Safer, Ozempic Or Metformin?

Both have strong safety records, but their profiles differ.

Metformin has decades of clinical use and a well-understood safety profile, while Ozempic is newer with a shorter track record. A licensed healthcare provider can determine which fits a specific health history.

Will I Lose Belly Fat On Metformin?

Often, yes, more than overall body fat.

Because Metformin improves insulin sensitivity, visceral fat around the abdomen tends to respond more noticeably than subcutaneous fat elsewhere on the body.

Sources

  1. Mayo Clinic – Overview of Metformin’s uses, mechanism of action, and reported side effects.
  2. Diabetes Care, American Diabetes Association journal – Clinical research on Metformin’s effects on body weight in patients with insulin resistance and Type 2 diabetes.
  3. Cleveland Clinic – Patient education on insulin resistance, weight management, and metabolic health.
  4. The Journal of Clinical Endocrinology and Metabolism – Peer-reviewed research on GLP-1 receptor agonists compared with other metabolic medications.
  5. Endocrine Practice – Clinical guidance on medication-assisted management of Type 2 diabetes and associated weight changes.

Medical Disclaimer

This content is for informational purposes only and is not intended as medical advice. It is not a substitute for professional consultation, diagnosis, or treatment. Always speak with a licensed healthcare provider before starting, stopping, or changing any medication, including Metformin.

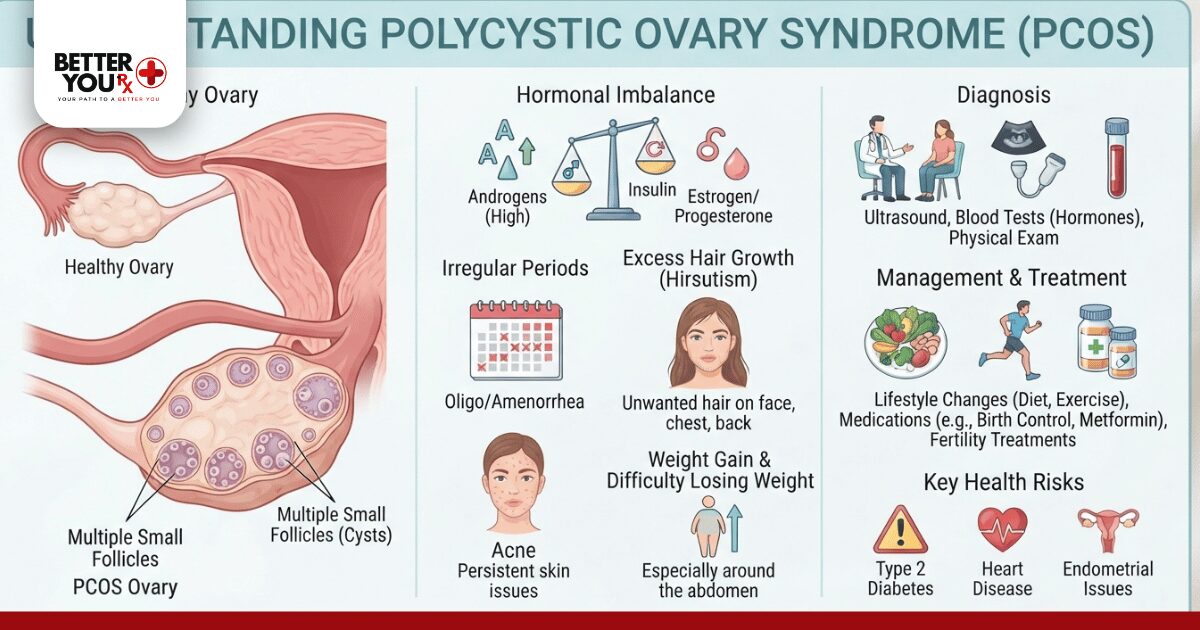
Does Metformin for PCOS Actually Work?

Metformin for PCOS is one of the most commonly prescribed non-hormonal options for managing insulin resistance, irregular cycles, and weight challenges tied to Polycystic Ovary Syndrome. It lowers glucose production in the liver and improves how the body responds to insulin, which often restores ovulation within a few months of consistent use. Results vary by person, dosage, and how closely the medication is paired with diet and activity changes, so it rarely works as a standalone fix. Providers typically start patients on a low dose and increase it gradually to limit stomach upset, with noticeable hormonal changes usually appearing after eight to twelve weeks.

Key Takeaways

  • Metformin primarily targets insulin resistance, a root driver of irregular ovulation and androgen excess in many women with PCOS.
  • Weight loss tends to be modest, often a small single-digit percentage of body weight over six to twelve months rather than a dramatic drop.
  • Cycle regularity and ovulation frequently improve before any noticeable change on the scale.
  • Most people stay on the medication for months to years, depending on symptom control, reproductive goals, and how well it is tolerated.

What Is Metformin for PCOS Used For?

Metformin was originally developed for type 2 diabetes, but it has become a standard off-label option for Polycystic Ovary Syndrome because so many women with the condition also have some degree of insulin resistance. When insulin levels run high, the ovaries tend to produce more androgens, which can disrupt ovulation, worsen acne, and contribute to excess hair growth. Metformin addresses this chain of events at its source rather than simply masking symptoms.

Doctors most often prescribe this medication when a patient has irregular or absent periods, is trying to conceive, or shows lab markers of insulin resistance alongside elevated androgens. It is also considered for women who are not ready for hormonal birth control, or who want a treatment that supports fertility rather than suppressing it. According to the Cleveland Clinic, insulin resistance affects a large share of women with PCOS regardless of body weight, which is part of why this treatment remains relevant across different body types.

There is also a practical reason many providers reach for Metformin first: it has decades of use behind it, a well-understood side effect profile, and it does not carry the fertility-suppressing effects that hormonal birth control does. For women who are not actively trying to conceive but still want cycle regulation, this makes it a comfortable middle-ground option between doing nothing and starting hormonal contraception.

Metformin Vs GLP 1 Agonists

How Metformin Works to Manage PCOS Symptoms

Metformin reduces the amount of glucose the liver releases into the bloodstream and makes muscle and fat tissue more responsive to insulin. With less insulin circulating, the ovaries typically produce fewer excess androgens, which allows the normal hormonal signals for ovulation to resume. This is why many women notice their cycles becoming shorter and more predictable before they see meaningful changes in weight or acne.

Patients who start this medication often report that their cycles become more consistent within the first two to three months, even before they notice changes on the scale. Providers frequently observe this cycle-regularity effect well ahead of measurable weight change, which is part of why cycle tracking is often the first marker used to judge whether treatment is working as intended. Most healthcare providers follow established clinical protocols when prescribing Metformin, starting low and titrating upward to balance effectiveness against digestive tolerance.

It typically takes longer for androgen-related symptoms like acne or excess facial hair to respond, since skin and hair follicles react to hormonal shifts on a slower timeline than the menstrual cycle does. Many patients are told to expect three to six months before judging whether these particular symptoms are improving.

Typical Metformin Dosing Pattern for PCOS

Stage Common Dose What to Expect
Starting Dose 500 mg once daily with food Mild digestive adjustment period
Titration 500 mg twice daily after one to two weeks Gradual increase to reduce stomach upset
Maintenance 1,500 to 2,000 mg daily, divided doses Ongoing insulin and cycle support


Metformin and Weight Loss in PCOS

Weight loss is one of the most searched aspects of this treatment, but expectations matter here. Metformin is not an appetite suppressant in the way GLP-1 medications are, so weight changes tend to be gradual and modest rather than dramatic. Many patients lose somewhere in the range of a few percentage points of body weight over six months to a year, particularly when the medication is combined with consistent meal timing and regular movement.

Some women ask whether a GLP-1 option such as Ozempic might be a faster route to weight loss, and the honest answer depends on the primary goal. Metformin tends to be favored when insulin resistance and fertility are the main concern, while GLP-1 medications are generally considered when weight loss itself is the priority.

Some providers combine Trulicity or a similar GLP-1 medication with this treatment when both insulin regulation and more noticeable weight loss are goals, though this decision always depends on individual health history. For a closer look at how these medication classes differ, the comparison in Ozempic vs Trulicity breaks down the mechanisms side by side, and Is Trulicity a GLP-1? explains how that drug class functions more broadly.

It is worth noting that weight loss on Metformin often plateaus after the first year unless paired with ongoing lifestyle adjustments, since the medication’s primary job is metabolic regulation rather than active fat loss. Patients who set expectations around steady, moderate progress tend to feel more satisfied with their results than those expecting rapid change.

Metformin vs. GLP-1 Medications for PCOS

Factor Metformin GLP-1 Medications (e.g., Ozempic)
Primary Action Improves insulin sensitivity, lowers liver glucose output Slows digestion, reduces appetite
Typical Weight Change Modest, gradual over months Often more pronounced
Administration Oral tablet Weekly injection
Best Fit For Insulin resistance, fertility support Weight loss as the primary goal
Common Timeline to Notice Effects 8 to 12 weeks for cycle changes Several weeks for appetite changes

Things To Know About Metformin for PCOS

  • Digestive side effects like nausea, bloating, or loose stools are common early on and usually settle within a few weeks.
  • Extended-release formulations are often gentler on the stomach than immediate-release tablets.
  • This medication does not directly treat acne or excess hair growth, though these can improve indirectly as androgen levels normalize.
  • Alcohol in excess should generally be avoided while taking Metformin due to a rare but serious risk of lactic acidosis.
  • Regular follow-up labs help a provider confirm the medication is still appropriate and well tolerated over time.
  • Fertility outcomes tend to improve most when treatment is combined with lifestyle changes rather than used in isolation.
  • Taking doses with meals, rather than on an empty stomach, meaningfully reduces the chance of nausea for most people.

Metformin for PCOS

Who Tends to Benefit Most From Metformin for PCOS

Women who show clear signs of insulin resistance, such as elevated fasting insulin or difficulty losing weight despite consistent effort, often respond best to this treatment. It is also a common first step for those hoping to conceive, since restoring regular ovulation is frequently the main obstacle to pregnancy in PCOS. Women whose symptoms are driven more by androgen excess than insulin resistance sometimes see less dramatic results and may need an additional treatment layered in.

Every treatment plan should be built around individual lab work and symptom patterns rather than a one-size-fits-all approach. A licensed provider is best positioned to determine whether Metformin alone is sufficient or whether it should be paired with another medication, such as Saxenda, based on the full clinical picture. Women managing PCOS alongside other conditions, such as elevated blood pressure or cholesterol, may also need their broader treatment plan coordinated, which is why ongoing communication with a provider matters more than any single medication decision.

The Bottom Line on Metformin for PCOS

Metformin remains a well-established starting point for women dealing with the insulin resistance side of Polycystic Ovary Syndrome, particularly when fertility and cycle regularity are priorities. Its effects build gradually, so patience through the first few months of dosing adjustments tends to pay off in more predictable cycles and better metabolic markers over time.

For those whose main goal is more significant weight loss, pairing this treatment with or substituting a GLP-1 option may be worth discussing with a provider, and resources like Saxenda vs Ozempic offer additional context on how those medications compare to each other. Whatever the path, working closely with a licensed provider ensures the treatment plan actually matches the underlying hormonal picture rather than guessing at symptoms alone.

Better You Rx is a prescription referral service connected to a licensed contracted dispensing department, helping patients access prescribed medications like Metformin and Ozempic through a straightforward referral process for personal use.

Frequently Asked Questions

Does metformin actually work for PCOS?

Yes, for many women. Metformin improves insulin sensitivity, which often restores more regular ovulation and can reduce androgen-related symptoms over several months of consistent use.

Will I lose weight if I take metformin for PCOS?

Possibly, but modestly. Weight loss is usually gradual, often a few percentage points of body weight over six months to a year, especially when paired with diet and activity changes.

Is Ozempic or metformin better for PCOS?

It depends on the goal. Metformin is often favored for insulin resistance and fertility support, while GLP-1 options like Ozempic tend to produce more noticeable weight loss.

How long should you take metformin for PCOS?

Often months to years. Duration depends on symptom control, fertility goals, and how well the medication is tolerated, and it should be reassessed periodically with a provider.

Can I lose 20 pounds on metformin?

It’s possible but not typical. Most people see modest, gradual weight changes rather than large drops, and results depend heavily on diet, activity, and individual metabolism.

Sources

  • Cleveland Clinic: Overview of Polycystic Ovary Syndrome, including insulin resistance and hormonal mechanisms.
  • The Journal of Clinical Endocrinology & Metabolism: Research on insulin-sensitizing agents and reproductive outcomes in PCOS.
  • American College of Obstetricians and Gynecologists (ACOG): Clinical guidance on PCOS diagnosis and management approaches.
  • Fertility and Sterility: Studies examining Metformin’s role in ovulation induction and fertility support for PCOS patients.
  • Mayo Clinic: Patient-focused overview of PCOS treatment options, including insulin-sensitizing medications.

This content is provided for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or changing any medication or treatment plan.

Free Doctor Consultation: How It Works Before Starting GLP-1 Treatment

A Free Doctor Consultation is a no-cost evaluation with a licensed provider that takes place before a prescription referral for treatments like Semaglutide, Tirzepatide, or Retatrutide moves forward. It gives a patient the chance to share their health history, list current medications, and confirm that the treatment they are requesting is a reasonable fit before any next step happens.

For many people researching weight management support or a specific GLP-1 medication, the biggest hesitation is not the treatment itself. It is not knowing what the first conversation with a provider actually looks like. A Free Doctor Consultation removes that uncertainty. It is built into the referral process at Better You Rx, a prescription referral service with a licensed contracted dispensing department that connects patients across the United States with treatment options once a doctor confirms appropriateness. What follows explains what happens during that conversation, why it comes before anything else, and how a patient can know whether the overall process fits their needs.

Here at Better You Rx, we are now providing the Free Doctor Consultation as a standard part of every treatment request. A patient no longer has to wonder whether a conversation with a provider is included or something they need to arrange separately. It is built into the process from the very first step, whether someone is asking about a well-established option or a newer one. 

Scan here to sign up for your free consultation.Scan

Key Takeaways

  • A Free Doctor Consultation is a no-cost review with a licensed provider that happens before any prescription referral moves forward.
  • The conversation confirms medical history, current medications, and whether a requested treatment such as Semaglutide or Tirzepatide fits a patient’s health profile.
  • Patients located in the United States can request a Free Doctor Consultation, though a prescription must ultimately come from a doctor licensed and practicing within the country.
  • The entire process happens remotely, so no travel to a clinic or office is required.
  • The consultation supports, rather than replaces, ongoing care from a patient’s regular healthcare provider.

What Happens During the Consultation

The conversation itself is straightforward. A licensed provider reviews what a patient shares about their health background, current medications, allergies, and the specific treatment they are curious about, whether that is Ozempic, Wegovy, or a newer option like Mounjaro. The goal is not to overwhelm anyone with paperwork. It is to confirm that a requested treatment lines up with a patient’s overall health picture before anything moves forward.

Providers commonly ask about existing conditions such as thyroid disorders, pancreatitis history, or kidney function, since these details matter for GLP-1 and dual-action treatments. Patients are also given room to ask questions of their own, whether that is about how a medication is typically dosed, what side effects tend to show up early on, or how long a titration schedule usually runs.

In practice, most patients say the hardest part is simply asking the first question. Providers who conduct these reviews report that the majority of appointments focus on confirming safety details rather than working through a lengthy interview, and many conversations wrap up faster than patients expect once the basic health history is on the table.
A patient who has recently switched from one treatment to another, for example moving from a once-weekly injection to a different dosing schedule, will usually spend a little more time on this part of the conversation than someone requesting a treatment for the first time. That is by design. The provider is not trying to slow anyone down. They are making sure the transition itself does not introduce a problem that would not have shown up with a first-time request.

Why This Consultation Comes Before Any Prescription Referral

Skipping straight to a medication request without a conversation first would leave out the exact details that make a treatment safe for one person and inappropriate for another. A Free Doctor Consultation exists to close that gap. The medical review itself carries no cost to the patient, separate from anything related to the treatment that may follow later, so cost is never a reason to avoid asking a question upfront.

This approach also reflects how most licensed providers already practice. Confirming a patient’s history before authorizing a prescription is standard clinical judgment, not an extra hurdle added on top of it. Most healthcare providers follow established clinical protocols when reviewing a request for Semaglutide, Tirzepatide, or Retatrutide, and a short conversation like this is typically the fastest way to confirm that a treatment plan actually makes sense for that patient.

How the Process Works, Step by Step

The path from a first request to a completed consultation generally follows the same sequence, regardless of which treatment a patient is asking about.

Step What Happens
1. Request submitted A patient shares basic health information and names the treatment they are interested in, such as Rybelsus or Zepbound.
2. Consultation scheduled A licensed provider reviews the request and reaches out to arrange a remote conversation.
3. Health history reviewed The provider discusses current medications, existing conditions, and any relevant lab history.
4. Treatment appropriateness confirmed The provider determines whether the requested treatment fits the patient’s health profile.
5. Referral processed Once confirmed, the request moves to the licensed contracted dispensing department for fulfillment.


Patients considering options like Ozempic or Wegovy often want to understand how these compare to other GLP-1 treatments before their appointment, and resources like the Ozempic vs Trulicity comparison can help frame those questions ahead of time.

Things to Know

  • A consultation like this is not an emergency service. Patients experiencing an urgent medical issue should contact a local provider or emergency service directly.
  • The conversation does not replace a patient’s primary care physician. It is meant to confirm appropriateness for a specific requested treatment, not to manage ongoing chronic conditions.
  • Prescriptions connected to this process must be issued by a doctor licensed and practicing within the United States, and written in English.
  • Shipments following a completed referral go directly to a patient’s residence for personal use, not to a clinic, doctor’s office, or hospital.
  • The appointment typically takes less time than patients expect, often a single remote conversation rather than multiple visits back and forth.

Free Doctor Consultation How It Works Before Starting GLP-1 Treatment

Which Option Is Best: A Consultation First, or a Direct Treatment Request

Some patients wonder whether they can skip the conversation altogether and request a specific medication outright. In practice, that is not how a safe referral process works, and it would not serve a patient’s best interest even if it were possible. Talking with a provider first is the better option for a simple reason: it puts a licensed professional between a patient’s request and any medication that follows, which is exactly the safeguard that makes a referral service trustworthy in the first place.

Why it matters: dosing for treatments like Tirzepatide or Semaglutide depends heavily on individual health factors that a provider needs to see before making a recommendation. How it works: the appointment surfaces those factors before a decision is made, rather than after one has already been reached. Which option is best: for essentially every patient, completing this step first is the appropriate and responsible path, since it is the part of the process that confirms a treatment is actually right for them, rather than simply requested by them.

Consider two patients who both ask about the same medication in the same week. One has no relevant medical history and a straightforward request. The other has a condition that changes how that same medication should be approached, or rules it out entirely. Neither patient would know which category they fall into without a conversation first. That is the practical reason a direct request, without a provider reviewing it, is never the better option, no matter how confident a patient feels about what they are asking for.

Treatment Category Examples Commonly Discussed For
GLP-1 receptor agonists Ozempic, Wegovy, Rybelsus Weight management and blood sugar support
Dual-action GIP and GLP-1 Mounjaro, Zepbound Weight management
Investigational GLP-1 research compounds Retatrutide Provider-guided research reference discussions only


Patients comparing dual-action options sometimes review the Mounjaro vs Trulicity comparison before their appointment, so they arrive with clearer questions for their provider.

Why This Consultation Comes Before Any Prescription Referral

Who Can Request This Consultation

Eligibility is straightforward, though it does come with a few boundaries worth knowing upfront. The service is intended for adult patients located within the United States. A prescription connected to the consultation must come from a doctor practicing within the United States, and it must be written in English. Prescriptions issued by a doctor practicing outside the country cannot be accepted, and completed orders are mailed only to a patient’s home address for their own personal use, never to a medical office or clinic.

This structure exists to keep the process consistent, safe, and easy for patients to follow from the first request through delivery. It also mirrors the way telehealth visits are generally structured across healthcare more broadly, where a remote conversation with a provider comes first, and any next step follows only once that conversation confirms it makes sense.

Patients weighing multiple treatment paths sometimes look at the Wegovy vs Saxenda for weight loss comparison to understand how their options differ before their scheduled appointment with a provider. A patient who arrives already familiar with the general differences between treatments tends to have a shorter, more focused conversation, since the provider can spend more time confirming personal health details rather than explaining background information.

Moving Forward With Your Consultation

A Free Doctor Consultation is the step that turns a general question about weight management treatment into a confirmed, provider-reviewed plan. It costs nothing to have that first conversation, and it is the safeguard that makes the rest of the referral process work the way it should, from confirming appropriateness through to a completed delivery at a patient’s own address. For anyone weighing a request for Semaglutide, Tirzepatide, or another GLP-1 option, starting with this conversation is not an extra step to get through. It is the step that makes everything after it trustworthy. Anyone with questions about scheduling or eligibility is welcome to call 1-647-576-2076 or email info@betteryourx.com to speak with our team directly.

Frequently Asked Questions

What is a Free Doctor Consultation?

It is a no-cost review with a licensed provider before any prescription referral begins. The conversation covers health history, current medications, and whether a requested treatment is appropriate for that patient.

Do I need a prescription already to request the consultation?

No, this conversation typically happens before any prescription decision is finalized. It exists to confirm that a treatment request makes sense before the referral moves forward.

How long does the appointment usually take?

Most consultations are completed in a single remote conversation, often under thirty minutes. The exact length can vary depending on a patient’s health history.

Is this consultation available for treatments like Mounjaro or Zepbound?

Yes, it applies to GLP-1 and dual-action treatment requests alike. A provider reviews the same health details regardless of which medication a patient is asking about.

Who is eligible for this consultation?

Adult patients located in the United States with a prescription from a US-licensed doctor. Prescriptions must be written in English and cannot come from a provider practicing outside the country.

Sources

  • Mayo Clinic – Overview of telehealth visits, virtual care structure, and how remote provider conversations are typically conducted.
  • New England Journal of Medicine – Clinical trial research on GLP-1 receptor agonist therapies and their role in weight management.
  • American Diabetes Association – Standards of care guidance covering GLP-1 and incretin-based therapy use.
  • Journal of the American Medical Association (JAMA) – Published research on patient outcomes associated with tirzepatide-based treatment.

Medical Disclaimer

This article is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or changing any medication or treatment plan.

What Does A Retatrutide Titration Chart Actually Show Patients?

Written by Sarah Collins, Clinical Content Writer | Medically Reviewed by Dr. Amanda Reyes, MD | Last Updated: July 2026

A Retatrutide titration chart is best understood as a visual reference for the general shape of dose progression, moving from a low starting point toward a higher, individualized level over a period of months. It is not a substitute for provider guidance, and the specific numbers, timing, and reconstitution details for any patient are set by their prescribing provider based on tolerability and response. Understanding how these charts are typically structured helps explain why no two patients follow an identical path, even when working with the same investigational compound.

Key Takeaways

  • A Retatrutide titration chart outlines the general stages of dose progression, not a fixed schedule that applies identically to every patient
  • Providers use these charts as a reference framework, adjusting timing and increments based on each patient’s tolerability
  • Retatrutide remains an investigational compound, so titration pacing is always determined through provider judgment rather than a standardized public protocol
  • Reconstitution and specific measurement instructions are handled directly between a patient and their prescribing provider, not through self-calculated amounts
  • Patients tend to have a smoother experience when they follow their provider’s individualized pace rather than a generic chart found online

What A Typical Retatrutide Titration Chart Looks Like

Most titration charts for investigational compounds like Retatrutide are organized around general stages rather than exact dates, since the actual pace depends entirely on how a patient responds at each step. A provider might use a chart like this as a starting reference before adjusting it to fit the individual.

Titration Stage General Pattern Clinical Purpose
Initial Phase Lowest starting tier Assessing baseline tolerability
Early Titration Gradual increase Monitoring gastrointestinal response
Mid-Range Adjustment Continued gradual increase Evaluating appetite and metabolic response
Advanced Titration Approaching higher tiers Confirming sustained tolerability
Maintenance Individualized ceiling Long-term monitoring and adjustment

This structure gives patients a general sense of what to expect, but the actual amounts, spacing between increases, and final maintenance level are always determined by the prescribing provider rather than read directly off a generic chart.

Why Titration Charts Are A Starting Point, Not A Prescription

A Retatrutide titration chart found online or in general educational material reflects the typical shape of dose progression seen across an investigational compound’s use, not a personalized plan for any one patient. Because Retatrutide targets three separate receptor pathways, GLP-1, GIP, and glucagon, individual responses vary more than with single-mechanism compounds like Semaglutide, which is one reason generic charts cannot substitute for provider-directed dosing.

In practice, providers often adjust the pace shown on a general chart based on what they observe. If a patient reports ongoing digestive discomfort, a provider may extend a given stage well beyond what a standard chart suggests. Patients who understand this distinction tend to have more realistic expectations than those who treat a chart as a fixed countdown.

Retatrutide Titration ChartThings To Know

  • A Retatrutide titration chart shows general stages, not exact amounts or timing for any specific patient
  • Reconstitution details and precise measurements are handled directly with a prescribing provider, not calculated independently
  • Providers frequently adjust pacing based on tolerability rather than following a chart exactly
  • Retatrutide remains investigational, so titration frameworks may continue to evolve as clinical understanding grows
  • Patients who follow their provider’s individualized pace generally report a more manageable adjustment period

Why Reconstitution And Dosing Calculators Are Handled By Providers

Reconstitution amounts and specific dosing calculations for an investigational compound are not something patients determine on their own, regardless of what a general chart or online tool might suggest. Because Retatrutide is not a standardized, publicly regulated medication with a uniform preparation protocol, the exact preparation and measurement steps a patient follows are set by their prescribing provider and the licensed contracted dispensing department involved in their care.

This is also why Better You Rx, working as a prescription referral service, does not publish or embed calculators for self-directed reconstitution or dosing. Most healthcare providers follow established clinical protocols when guiding patients through preparation and administration, and that guidance is tailored to the specific concentration and formulation a patient has been prescribed, which can vary between individuals.

Patients exploring related metabolic health options may also find it useful to compare Retatrutide and Tirzepatide, review Retatrutide’s potential benefits, or look into how Retatrutide is generally reconstituted as a starting point for a conversation with their provider, rather than as a substitute for individualized instructions.

How Titration Charts Fit Into A Broader Treatment Plan

A Retatrutide titration chart works best as a conversation tool between a patient and their provider, giving both a shared reference point for discussing progress. Providers typically review a patient’s response at each stage before deciding whether to move to the next point on the chart, hold steady, or adjust the pace entirely.

Compound General Titration Approach Primary Mechanism
Retatrutide Individualized, provider-managed GLP-1, GIP, and glucagon receptor activity
Tirzepatide Individualized, provider-managed GLP-1 and GIP receptor activity
Semaglutide Individualized, provider-managed GLP-1 receptor activity

This comparison shows that titration approaches across investigational and established compounds share a similar philosophy: gradual, monitored progression rather than a fixed public formula. Patients considering options such as Mounjaro or Zepbound can discuss with their provider how titration pacing differs across these choices.

Why Titration Charts Are A Starting Point, Not A Prescription

Moving Forward With A Titration Chart In Hand

A Retatrutide titration chart is a useful reference for understanding the general shape of dose progression, but it is not a replacement for individualized guidance from a licensed provider. The specific pace, amounts, and preparation steps for any patient depend on tolerability, response, and ongoing clinical judgment, which is why the same general chart can look very different in practice from one patient to the next.

Anyone exploring Retatrutide as part of a broader metabolic health plan can review additional resources such as what Retatrutide does in the body or Retatrutide side effects while preparing for a more informed conversation with their provider.

Frequently Asked Questions

How Should I Titrate Retatrutide?

Titration should be planned entirely with a prescribing provider. They determine starting amounts, pacing, and increases based on individual tolerability and response.

Is There A Standard Weekly Schedule For Retatrutide?

No, weekly schedules are set individually by a provider. Because Retatrutide is investigational, there is no standardized public schedule that applies to every patient.

Can I Calculate My Own Reconstitution Amounts?

No, reconstitution should be handled with your provider or dispensing team. Preparation details vary by formulation and are set on an individualized basis.

Where Can I Get Reconstitution Instructions?

Directly from your prescribing provider or licensed dispensing team. They provide instructions specific to your prescription rather than a general online formula.

Does A Titration Chart Replace Provider Guidance?

No, a chart is a general reference only. Actual dosing and preparation decisions always come from a licensed provider familiar with your individual treatment.

Sources

  1. New England Journal of Medicine — Clinical research on triple-receptor agonist compounds and their metabolic effects.
  2. The Lancet Diabetes & Endocrinology — Peer-reviewed data on GLP-1, GIP, and glucagon receptor co-agonism in metabolic treatment research.
  3. Mayo Clinic — Overview of investigational weight management medications and general dosing principles.
  4. Cleveland Clinic — Patient education resources on GLP-1 and multi-receptor agonist therapies.
  5. Journal of Clinical Endocrinology & Metabolism — Research on titration strategies and tolerability in metabolic compound studies.

Medical Disclaimer: This content is provided for informational purposes only and is not intended as medical advice. It does not replace consultation with a licensed healthcare provider. Anyone considering Retatrutide or any other treatment should speak with a qualified medical professional to determine what is appropriate for their individual health needs before starting, adjusting, or discontinuing any medication.


Retatrutide 2mg Dose: What This Research Level Means and Why It Requires Medical Guidance

Written by Maria Santos, BSc Health Communications | Medically Reviewed by Dr. Aleksandar Petrov, MD | Updated: July 2026

Last Updated: July 13, 2026

A Retatrutide 2mg dose is a specific amount that has appeared in published research examining this investigational compound’s effects on appetite regulation and metabolic function. It is not a number intended for independent use, and any decision involving this level of treatment should come from a licensed provider who has reviewed a patient’s full health picture.

Patients searching for this term are often trying to make sense of numbers they have seen referenced in research summaries, forums, or informal discussions. Understanding what this figure actually represents in a research context, and why that context does not translate into a personal instruction, helps clarify a topic that is frequently misunderstood.

Key Takeaways

  • A Retatrutide 2mg dose refers to one of several levels examined in clinical research, not a fixed amount recommended for general self-use.
  • Because Retatrutide remains an investigational compound, any reference to a Retatrutide 2mg dose online reflects research reporting rather than an approved prescribing standard.
  • Where a Retatrutide 2mg dose falls within a broader treatment plan depends entirely on an individual provider’s assessment of tolerance and health history.
  • Comparing a Retatrutide 2mg dose to other studied amounts is only meaningful in the context of a supervised, provider-guided plan.
  • Anyone curious about a Retatrutide 2mg dose should raise the topic directly with a licensed healthcare provider rather than relying on general online information.

What Does a Retatrutide 2mg Dose Represent in Research?

Clinical research examining Retatrutide has looked at several dose levels to understand how the compound behaves at different amounts, including how the body responds and what effects appear at each stage. A Retatrutide 2mg dose is one of the amounts that has appeared in published research, typically discussed alongside other levels as part of a broader study design.

It is important to separate this research context from personal application. A number appearing in a study does not mean it is the right amount, or even a safe amount, for any individual outside of that supervised research setting. Because Retatrutide has not completed the regulatory review process required for standard prescribing in the United States, there is no approved consumer-facing dosing standard tied to this level or any other specific amount at this time.

Researchers typically report findings across a full range of studied amounts rather than isolating a single figure, since the way a compound behaves at one level often only makes sense when compared against neighboring levels in the same study. This is part of why isolated numbers circulating outside of research papers can be misleading when taken out of that broader context.

Retatrutide 2mg Doses

Why a Retatrutide 2mg Dose Is Not a Self-Directed Figure

The appeal of a specific number is understandable, since it feels concrete and easy to reference. However, treating a Retatrutide 2mg dose as something to replicate independently overlooks the substantial amount of clinical oversight that surrounds any number referenced in research literature.

Providers who oversee any phased treatment plan typically consider a patient’s body weight, existing health conditions, other medications, and how the individual responded to earlier stages before determining what amount, if any, is appropriate at a given point. A figure that appears in a published study reflects the specific conditions of that research population, not a universal recommendation applicable to everyone reading about it.

Patients sometimes assume that because a number has been studied and published, it is inherently safe to use outside of that setting. This assumption does not hold up clinically. Research dosing occurs within a tightly monitored environment with regular safety checks, which is fundamentally different from an individual using a figure they found online without supervision.

Things To Know

  • A Retatrutide 2mg dose referenced in research reflects a study-specific context, not a general recommendation.
  • Retatrutide remains an investigational compound without an approved consumer dosing standard.
  • Any specific number, including this particular level, should only be discussed within a supervised clinical relationship.
  • Individual factors such as body weight, tolerance, and health history determine what a provider considers appropriate.
  • Most healthcare providers rely on established clinical protocols and ongoing monitoring when evaluating any phased treatment amount, rather than applying a single figure uniformly.

How This Level Fits Into a Broader Research Framework

Research involving Retatrutide has generally examined a range of levels as part of a phased approach, where a compound is introduced gradually and adjusted over time. The table below outlines this general framework in broad terms, without providing specific instructions for self-administration.


Research Stage General Description Clinical Relevance
Early Levels Lower amounts studied during initial phases Used to observe early tolerance patterns
Mid-Range Levels Amounts including a Retatrutide 2mg dose in some study designs Reviewed for both effect and tolerability
Higher Levels Amounts studied further into a research protocol Considered only after earlier levels were reviewed
Maintenance Levels Levels studied for longer-term observation Monitored on an ongoing basis within the research setting


This structure illustrates why a single figure cannot be understood in isolation. It exists within a sequence that research teams monitor closely, and its relevance depends entirely on the surrounding clinical context.

Factors That Determine Whether a Level Like This Is Appropriate

Several factors shape whether any specific amount would even be considered relevant to an individual patient’s plan. These factors are reviewed by a provider rather than determined independently by a patient.


Factor Why It Matters
Body weight and composition Influences how a provider evaluates any studied level
Prior tolerance Side effects at earlier stages affect what comes next
Overall health history Kidney, liver, or metabolic conditions change clinical judgment
Concurrent medications Interactions must be reviewed before any amount is considered
Treatment goals Providers weigh goals differently depending on the patient’s broader plan


Patients often report feeling more confident once they understand that a specific figure like this is only one data point within a much larger clinical picture, not a standalone target to pursue independently. Providers routinely explain this distinction during consultations, since it directly shapes how a treatment conversation should be framed.

Retatrutide 2mg Dose

Why Research Numbers Should Not Be Compared to Personal Circumstances

One of the more common misunderstandings involves treating a research figure as if it were interchangeable with a personal recommendation. A number reported in a study reflects the average or aggregate response of a specific study population under close medical supervision, monitored regularly for safety signals throughout the research period.

An individual reading about that figure outside of a research setting does not have access to the same monitoring infrastructure, lab work, or clinical oversight that shaped how that number was used in the original study. This is one of the central reasons providers caution against drawing direct conclusions from research literature without a full clinical evaluation first.

Patients sometimes describe feeling reassured once this distinction is explained clearly, since it shifts the conversation away from chasing a specific figure and toward understanding what a provider would actually need to know before any treatment plan, involving Retatrutide or otherwise, could be considered appropriate for their situation.

Comparing This Amount to Other Studied Levels

Research summaries sometimes place a Retatrutide 2mg dose alongside other levels to illustrate a broader pattern of how effects and tolerability changed across a study. This kind of comparison is useful for understanding research findings generally, but it does not translate into guidance for choosing between levels independently.

Patients considering established, currently available treatments such as Mounjaro or Zepbound may find it helpful to understand that these medications also follow provider-guided, individualized approaches to treatment planning, rather than a single amount applied the same way to every patient. The same principle applies to any conversation involving a Retatrutide 2mg dose.

Why a Retatrutide 2mg Dose Is Not a Self-Directed FigureWhat to Ask a Provider About This Topic

Patients who want to make the most of a conversation touching on a Retatrutide 2mg dose or any other researched level often find it helpful to prepare a short list of questions in advance. Asking a provider what factors they weigh most heavily, how they monitor tolerance over time, and what signs would prompt a change in plan gives the conversation more structure and helps a patient understand the reasoning behind any decision, rather than focusing on a single number in isolation.

It can also help to ask how a provider stays current on research involving investigational compounds, since this area of medicine continues to evolve. A provider who can explain both the research landscape and the clinical reasoning behind their recommendations is generally better positioned to guide a patient through decisions involving a level like this, compared to relying on informal sources alone.

Bringing a written summary of any relevant health history, current medications, and specific questions to an appointment tends to make these conversations more efficient. Providers routinely note that patients who arrive prepared are able to cover more ground in a single visit, which can be especially valuable when the topic involves a compound still under active research.

Frequently Asked Questions

What is a Retatrutide 2mg dose used for?

A research reference point, not a personal instruction. This figure has appeared in published research examining the compound’s effects, but it is not a number intended for independent or self-directed use.

Is a Retatrutide 2mg dose a starting amount or a later stage?

It depends on the specific study. Different research designs have placed this level at different points, so its position within any framework varies rather than following one fixed pattern.

How does a Retatrutide 2mg dose compare to other studied levels?

It is one point among several. Research has examined multiple levels, and this figure is generally discussed as part of that broader range rather than as a standalone number.

What should someone know before considering a Retatrutide 2mg dose?

It requires a provider’s full assessment. Any consideration of this level should involve a licensed provider reviewing health history, tolerance, and treatment goals first.

Can a Retatrutide 2mg dose be self-administered without supervision?

No, this is not recommended. This figure, as referenced in research, reflects a supervised clinical setting, and using it independently falls outside safe, provider-guided practice.

Sources

  1. National Institutes of Health, National Library of Medicine, ClinicalTrials.gov – Registry entries and study protocols for triple agonist metabolic compounds under investigation.
  2. The New England Journal of Medicine – Peer reviewed clinical trial data on multi-receptor agonist compounds and metabolic outcomes.
  3. Mayo Clinic – General patient education on phased dosing approaches for metabolic and weight management treatments.
  4. Cleveland Clinic – Overview of how healthcare providers assess and monitor gradual treatment adjustments.
  5. American Diabetes Association – Clinical guidance on metabolic treatment monitoring and patient safety considerations.

Medical Disclaimer

This content is provided for general informational and educational purposes only and does not constitute medical advice. It is not a substitute for professional consultation, diagnosis, or treatment from a licensed healthcare provider. Retatrutide referenced in this article is discussed in its current investigational context. Readers should consult a licensed healthcare provider before starting, stopping, or adjusting any treatment plan.

Retatrutide Needle Size 101: A Provider-Guided Approach

Medically Reviewed by Dr. Amanda Reyes, MD | Last Updated: July 2026

Retatrutide needle size is not something patients look up and select independently. A licensed provider determines the appropriate equipment based on the specific formulation being used, the patient’s current dosing stage, and other individual clinical factors. Because Retatrutide is still an investigational compound, there is no standardized product insert covering equipment the way approved medications typically have, which is exactly why this decision stays with the prescribing provider rather than general online resources.

Key Takeaways

  • Retatrutide needle size is selected by a licensed provider based on formulation, dosing stage, and individual patient needs
  • No standardized equipment sheet exists for Retatrutide since it remains an investigational compound
  • Providers typically walk patients through administration details during consultation rather than relying on generic instructions
  • Needle gauge, injection depth, and supply sourcing are all decisions that stay within the provider’s clinical oversight
  • Patients benefit most by treating their provider as the single source of truth for equipment and technique questions

Why This Decision Belongs To A Provider, Not A Search Engine

It’s a natural instinct to search for practical details like gauge or depth before starting any injectable treatment. But with an investigational compound like Retatrutide, those specifics vary from patient to patient and even from one dosing stage to the next. A provider factors in the formulation being dispensed, how far along a patient is in their titration schedule, and any individual anatomical or comfort considerations before recommending equipment.

This is a meaningful difference from approved, widely prescribed injectables that come with consistent, standardized patient guides. Retatrutide’s investigational status means that guidance is built around the individual, not a printed instruction sheet meant for a general population.

A Look At What Providers Actually Weigh

Factor Why It Matters Who Decides
Formulation type Different preparations may call for different equipment Prescribing provider
Current dosing stage Titration phase can affect volume and technique Prescribing provider
Patient anatomy and comfort Individual differences influence what works best Provider, with patient input
Prior tolerability Past experience shapes ongoing recommendations Prescribing provider

Providers use this kind of framework as a starting point, then adjust based on how each patient responds throughout treatment.

Things To Know

  • Retatrutide needle size is never a fixed number patients can apply universally to their own situation
  • Investigational compounds lack the standardized patient literature that comes packaged with approved medications
  • Providers often cover equipment questions in the same visit where dosing schedules are discussed
  • Patients frequently report feeling more confident once they have a direct provider relationship to ask these questions, rather than piecing together answers from scattered sources
  • Most healthcare providers follow established clinical protocols when guiding injectable treatment planning, prioritizing individualized safety over generic assumptions

How This Compares To Approved GLP-1 Options

Patients who have used approved medications such as Ozempic, Trulicity, or Wegovy are often used to clear, standardized instructions included with the product. Retatrutide doesn’t follow that same model yet, since it remains under clinical investigation. That distinction matters because it shifts the responsibility for administration guidance almost entirely onto the provider-patient relationship rather than a printed insert.

Providers prescribing investigational compounds tend to spend more time on this kind of individualized education specifically because there isn’t a one-size-fits-all sheet to hand out. This is one more reason ongoing, open communication with a provider carries more weight with a compound like this than it might with a long-established medication.

Retatrutide Needle SizeWhat A Typical Consultation Looks Like

In practice, providers commonly walk new patients through every practical detail of their investigational treatment plan during the first consultation, equipment included, so nothing is left to guesswork. Patients often mention that having this laid out clearly upfront, instead of trying to piece it together from general searches, gives them more confidence heading into treatment. Providers may revisit these same details at later visits, since needs can shift as a patient moves through different stages of titration.

This reflects a broader pattern in metabolic health care: consistent, individualized provider communication tends to produce smoother experiences than relying on assumptions borrowed from other medications. Patients researching Retatrutide’s benefits or comparing Retatrutide versus Tirzepatide will notice this same individualized approach applies across nearly every practical aspect of care, not only dosing.

Where To Direct Supply And Sourcing Questions

Questions about where to obtain appropriate injection supplies should go to the prescribing provider or treatment team, not general retailers or unrelated sources. Providers typically coordinate supply needs as part of the broader treatment plan, so patients aren’t left guessing at specifications that may not even apply to their particular formulation or stage.

Better You Rx functions as a prescription referral service with a licensed contracted dispensing department, connecting patients with providers who manage treatment planning, including equipment guidance, on an individualized basis. Patients weighing other options can also look into Zepbound or Mounjaro while discussing the full range of provider-directed choices available to them.

For more context on how Retatrutide fits into an overall treatment picture, it may help to review what Retatrutide does in the body and documented Retatrutide side effects, both useful starting points for a more informed provider conversation.

How This Compares To Approved GLP-1 Options

The Bottom Line On Equipment Decisions

Every practical question tied to Retatrutide needle size, whether it’s gauge, depth, or where to source supplies, comes back to the same answer: a licensed provider makes this call directly with each patient. Investigational compounds require a degree of individualized oversight that generic instructions simply can’t replace safely. Patients who keep communication open with their provider throughout treatment tend to move through these details with far more clarity than those trying to apply standardized answers to a plan that isn’t standardized at all.

Anyone starting or continuing Retatrutide treatment is best served by treating their provider as the go-to source for every equipment and technique question, keeping their plan safe, appropriate, and built around their own needs.

Frequently Asked Questions

What Gauge Needle For Retatrutide?

This is determined by the prescribing provider. Since Retatrutide is investigational, gauge selection depends on the individual’s formulation and treatment plan rather than a general standard.

How Deep Do You Inject Reta?

Injection depth is a provider-directed decision. Patients should discuss technique directly with their provider instead of relying on general online guidance.

Where To Get Needles For Retatrutide?

Supply sourcing goes through the prescribing provider or treatment team. They coordinate equipment as part of an individualized plan.

What Size Needle For GLP1?

Needle size varies by medication and provider protocol. Approved GLP-1 medications often include standardized supplies, while investigational compounds require direct provider input.

What Is 2.5 Units On A Syringe?

This refers to a volume marking on the syringe barrel. A provider explains exact measurements relevant to each patient’s individual dosing plan.

Sources

  1. New England Journal of Medicine — Clinical research on injectable metabolic compounds and administration protocols.
  2. The Lancet Diabetes & Endocrinology — Peer-reviewed data on GLP-1 and multi-receptor agonist administration practices.
  3. Mayo Clinic — Patient education on injectable medication administration and provider-guided treatment planning.
  4. Cleveland Clinic — Overview of individualized treatment approaches for metabolic health medications.
  5. Journal of Clinical Endocrinology & Metabolism — Research on investigational compound protocols and clinical oversight standards.

Medical Disclaimer: This content is provided for informational purposes only and is not intended as medical advice. It does not replace consultation with a licensed healthcare provider. Anyone considering Retatrutide or any other treatment should speak with a qualified medical professional regarding administration, equipment, and dosing before starting, adjusting, or discontinuing any treatment.


Sign Up For Newsletter

Please enable JavaScript in your browser to complete this form.

Join 60.000+ Subscribers and get a new discount coupon on every Saturday.

Address

PO Box 29631, Mississauga RPO Central Parkway, ON L5A 4H2

Phone Number

1-647-576-2076

better you rx big letter logo

Discover convenience with Better You Rx, your trusted pharmacy-affiliated partner. We work with leading pharmacies to deliver prescriptions and over-the-counter medications right to your doorstep. Enjoy cost-effective solutions on a platform that’s easy to use. We focus on safety and efficacy in all products. Our dedicated team ensures a smooth experience. From ordering to delivery, we simplify your healthcare needs. Choose Better You Rx for reliable service and expert support. Trust us for all your medication requirements. Experience the ease of modern pharmacy care.

Categories

Operating Hours: 
10:00AM – 6:00PM CST
Monday – Friday

Our Payment Partners :

Copyright © 2026 BetteryouRX. All Rights Reserved.
Join The Waitlist Be among the first to know when becomes available.
Add to cart