Retatrutide Hydration Needs: What Research Participants Should Know

Written by Amanda Cole, RD, Clinical Content Writer  |  Medically Reviewed by Dr. Priya Nandakumar, MD  |  Updated: July 2026

Last Updated: July 28, 2026

Retatrutide hydration needs typically increase during dose titration because the medication’s effect on appetite and digestion slows gastric emptying and frequently triggers nausea, vomiting, or diarrhea. Because Retatrutide remains an investigational triple agonist studied for weight management, every fluid and electrolyte recommendation here is a research reference point that should be reviewed with a supervising physician, not a self-directed protocol.

Key Takeaways

  • Retatrutide hydration needs often rise during the first few weeks after a dose increase, when gastrointestinal side effects are most pronounced
  • Slowed gastric emptying is the main reason thirst cues can feel unreliable during titration phases
  • Plain water, electrolyte solutions, and broth-based fluids each serve a different hydration purpose
  • Persistent vomiting, dark urine, dizziness, or a rapid heartbeat are signs that fluid loss needs medical attention
  • All dosing figures referenced in Retatrutide research are provider-supervised checkpoints, not self-administration guidance

Why Retatrutide Hydration Needs Increase During Titration

Retatrutide belongs to a newer class of investigational therapies that act on GLP-1, GIP, and glucagon receptors simultaneously. This triple mechanism is part of why appetite suppression and gastric slowing are more pronounced than with single-receptor medications. When the stomach empties more slowly, nausea becomes more likely, and nausea often reduces how much fluid a person voluntarily drinks at exactly the point when the body needs more of it.

Diarrhea and vomiting, when they occur, compound the problem by removing fluid and electrolytes directly rather than simply reducing intake. This combination, reduced drinking plus increased fluid loss, is the core reason Retatrutide hydration needs shift upward during active titration phases rather than staying constant throughout a research protocol.

Patients enrolled in GLP-1 and GIP receptor agonist research programs frequently report that the first ten to fourteen days after a dose increase are when thirst signals feel muted or delayed, and supervising providers often note this pattern during routine check-ins. Most healthcare providers overseeing investigational GLP-1 based therapies follow established clinical protocols for monitoring hydration status and electrolyte balance throughout titration, rather than waiting for symptoms to appear.

Things To Know

  • Thirst is not a reliable early warning sign during dose titration; scheduled sipping works better than waiting to feel thirsty
  • Fluid needs are typically highest in the 48 to 72 hours following a dose adjustment, based on general GLP-1 and GIP research patterns
  • Caffeinated and alcoholic beverages do not count toward hydration goals and can worsen nausea
  • Cold or room-temperature water is often better tolerated than warm liquids when nausea is present
  • Any specific fluid target should come from a supervising physician, since individual tolerance during Retatrutide research varies considerably

How Gastrointestinal Side Effects Drive Fluid Loss

Common Side Effect Why It Raises Fluid Needs Practical Response
Nausea Reduces voluntary fluid intake even though the body still needs water Small, frequent sips rather than large glasses at once
Vomiting Removes fluid and electrolytes directly from the body Clear fluids first, then broth or an electrolyte solution once tolerated
Diarrhea Rapid loss of water, sodium, and potassium Oral rehydration solutions or electrolyte-enhanced water
Reduced appetite Less fluid consumed through food, since food itself contains water Water-rich foods like broth, melon, or cucumber when eating resumes
Slowed gastric emptying Can create a false sense of fullness that discourages drinking Spacing fluids apart from meals rather than with them


Patients who have previously used medications such as Mounjaro Kwikpen or Zepbound Kwikpen often recognize this pattern, since GLP-1 and GIP receptor agonists share a similar gastrointestinal side effect profile even though Retatrutide’s triple mechanism is still under investigation.
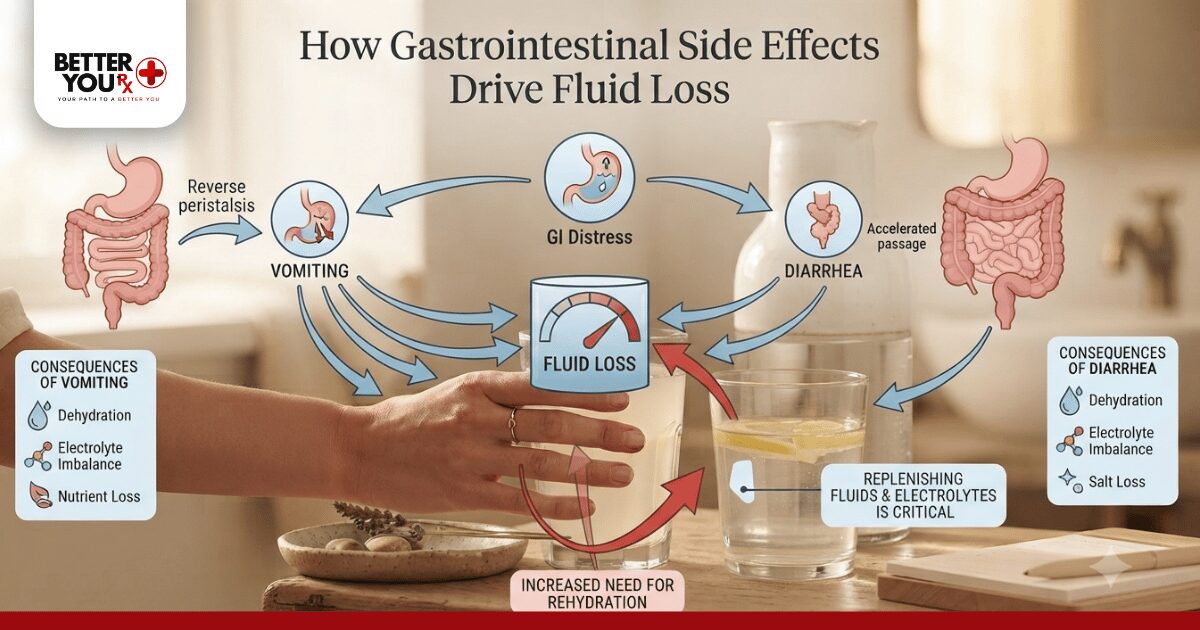
How Gastrointestinal Side Effects Drive Fluid Loss

Which Hydration Strategy Works Best

Choosing the right fluid depends on what symptom is driving the loss. Plain water restores volume but does not replace electrolytes lost through vomiting or diarrhea. Electrolyte solutions replace sodium and potassium but are not meant to be a person’s only fluid source throughout the day. Broth-based fluids offer sodium and a small amount of nutrition when solid food is difficult to tolerate.

Hydration Method Best For Why It Helps
Plain water General daily fluid maintenance Simple, calorie-free volume replacement
Oral electrolyte solution Active vomiting or diarrhea Replaces sodium and potassium alongside water
Broth or bouillon Low appetite with nausea Provides sodium and mild nutritional support
Water-rich fruit or vegetables Reduced fluid intake without acute GI symptoms Adds fluid volume through food when drinking feels difficult


The most applicable option is rarely just one of these on its own. Most providers recommend layering plain water as the baseline and adding an electrolyte solution specifically during flare-ups of vomiting or diarrhea, rather than relying on electrolyte drinks continuously.

Why Retatrutide Hydration Needs Increase During Titration

Recognizing When Fluid Loss Needs Medical Attention

Mild dehydration can usually be managed at home with deliberate fluid intake. According to the Mayo Clinic’s overview of dehydration symptoms, warning signs such as dark urine, dizziness, confusion, or a rapid heartbeat indicate that fluid loss has progressed beyond what home measures can safely address. Anyone experiencing these symptoms during Retatrutide research participation should contact their supervising physician rather than waiting to see if symptoms resolve on their own.

Persistent vomiting that prevents keeping any fluids down for more than a few hours is another signal that professional evaluation is needed. This is consistent with general clinical guidance for any medication that affects gastric emptying, not unique to Retatrutide specifically.

For readers weighing Retatrutide against other investigational options, the comparison in Retatrutide vs Tirzepatide covers how side effect timing differs between the two, while Retatrutide side effects outlines the broader symptom picture beyond hydration alone.

Building a Daily Fluid Routine

A steady routine works better than reactive drinking. Spacing eight to ten small servings of fluid throughout the day, rather than two or three large ones, tends to sit better with a slowed digestive system. Keeping a water bottle visible as a passive reminder, setting phone alerts during the first week after a dose change, and pairing fluid intake with existing habits like waking up or finishing a meal are simple structural changes that make a measurable difference for many patients.

Patients transitioning between weight management options sometimes ask their provider whether alternatives such as Wegovy carry the same hydration considerations. The general answer is yes, since gastric slowing is a shared mechanism across this medication class, though individual tolerance still varies. Reviewing Retatrutide benefits alongside these practical fluid strategies gives a fuller picture of what a titration period may involve.

Things To Know During Dose Changes

  • Fluid needs typically peak shortly after a dose increase, then taper as the body adjusts
  • Reintroducing food slowly after a vomiting episode helps avoid re-triggering nausea before hydration is restored
  • Sports drinks marketed for athletic performance often contain more sugar than needed for simple rehydration
  • A supervising physician can adjust the pace of any research protocol if hydration challenges become difficult to manage

Staying Ahead of Retatrutide Hydration Needs

Fluid management during Retatrutide research participation comes down to anticipating symptoms rather than reacting to them. Understanding why gastric slowing affects thirst, layering the right fluid type for the right symptom, and knowing which warning signs require a call to a supervising physician all make titration periods more manageable. Anyone participating in a Retatrutide research protocol should treat these hydration strategies as a starting conversation with their provider rather than a fixed set of rules to follow alone.

Frequently Asked Questions

Does Retatrutide cause dehydration directly?

Retatrutide does not cause dehydration on its own; the risk comes from associated nausea, vomiting, or diarrhea. These gastrointestinal effects reduce fluid intake or increase fluid loss, which is what actually drives dehydration risk during titration.

How much water should I drink during Retatrutide research participation?

There is no universal number, since fluid needs depend on symptoms and body size. A supervising physician can set an individualized target based on tolerance and any gastrointestinal side effects experienced.

What are early signs that hydration needs attention?

Dark yellow urine, dry mouth, and unusual fatigue are early indicators. These typically appear before more serious symptoms like dizziness or a rapid heartbeat develop.

Do electrolyte drinks help with hydration during titration?

Yes, particularly during active vomiting or diarrhea episodes. Outside of those episodes, plain water is usually sufficient for daily maintenance.

Why does thirst feel unreliable during a dose increase?

Slowed gastric emptying and appetite suppression can dull normal thirst signals. This is why scheduled sipping is often recommended over waiting to feel thirsty during the first weeks after a dose change.

Sources

  • Mayo Clinic — Overview of dehydration symptoms, causes, and when fluid loss requires medical evaluation.
  • National Institute of Diabetes and Digestive and Kidney Diseases — Information on gastrointestinal symptoms, including diarrhea-related fluid and electrolyte loss.
  • Nutrients (peer-reviewed journal) — Research on rehydration strategies and fluid replacement physiology.
  • Cleveland Clinic — Patient-facing overview of dehydration recognition and general fluid replacement guidance.

Medical Disclaimer: This article is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Retatrutide remains an investigational medication, and any dosing, titration, or hydration guidance referenced here should be discussed with and supervised by a licensed healthcare provider. Always consult a physician before starting, adjusting, or discontinuing any treatment.

Retatrutide Coffee Caffeine: What Happens When You Mix Your Morning Cup With Research-Phase Treatment

Retatrutide coffee caffeine questions come up constantly among people following triple-agonist research protocols, and theshort answer is that caffeine is not off-limits, but it can intensify the same side effects Retatrutide is already known for. Nausea, a racing heart, and appetite suppression can all get stronger when caffeine is added on top of a compound that already slows digestion and affects hunger signals.

Retatrutide, a compound still under research and provider-supervised evaluation for its effects on Glucagon-like peptide-1, GIP, and glucagon receptors, is administered only under professional oversight, and none of the information below should be used to self-manage dosing or treatment decisions.


Key Takeaways

  • Caffeine is not banned during Retatrutide research protocols, but it can amplify nausea, jitteriness, and appetite suppression
  • The so-called “2 hour coffee rule” is a spacing habit some people use, not a formal clinical requirement
  • Tea is generally gentler on the stomach than coffee for people managing Retatrutide-related nausea
  • Caffeine does not meaningfully affect thyroid function on its own, though thyroid health is still worth monitoring during any metabolic treatment
  • Alcohol, greasy foods, and excessive caffeine are the three things people managing Retatrutide side effects report struggling with most

Why Retatrutide Coffee Caffeine Combinations Feel Different Than They Used To

Retatrutide slows gastric emptying, meaning food and liquid sit in the stomach longer than they normally would. Caffeine, on its own, stimulates the release of stomach acid and speeds up gut motility in ways that can clash with that slower digestion. People who never had an issue with a morning espresso before starting Retatrutide sometimes find that the same cup now triggers acid reflux, queasiness, or an uncomfortably full feeling.

There is also a compounding effect on appetite. Both caffeine and Retatrutide can suppress hunger independently. Combined, some people notice they barely feel like eating at all in the first few hours of the day, which can lead to skipped meals, low blood sugar sensations, and fatigue if it happens repeatedly.

Heart rate is another factor worth understanding. Retatrutide research has tracked mild increases in heart rate in some participants, and caffeine is a known stimulant that raises heart rate on its own. Stacking the two does not automatically cause harm for most healthy adults, but for anyone who already notices palpitations or lightheadedness, reducing caffeine intake is a reasonable and commonly recommended adjustment.

Things To Know About Caffeine While On Retatrutide

  • Caffeine sensitivity often increases during the first four to eight weeks of a research protocol, then tends to level out as the body adjusts
  • Cold brew and espresso are more concentrated than drip coffee, so smaller amounts can still deliver a large caffeine dose
  • Energy drinks combine caffeine with sugar and other stimulants, making them a less predictable choice than plain coffee or tea
  • Hydration matters more than usual, since caffeine has a mild diuretic effect and Retatrutide can already reduce overall fluid intake if appetite and thirst cues are dulled
  • Providers overseeing Retatrutide research protocols generally suggest tracking symptoms alongside caffeine intake rather than eliminating it outright, since individual tolerance varies considerably

The Retatrutide Coffee Caffeine Timing Debate: What The “2 Hour Rule” Actually Means

The 2 hour coffee rule is a habit that circulated among people managing GLP-1 and multi-agonist treatments, and it generally means waiting roughly two hours after a dose or after the first meal of the day before drinking coffee, rather than having caffeine on a completely empty, medicated stomach. It is not a formal medical guideline published anywhere, and no clinical protocol requires it. That said, the reasoning behind it holds up reasonably well: caffeine on an already slow-emptying, possibly still-adjusting stomach tends to produce sharper nausea than caffeine taken after some food has settled.

People who find mornings rough sometimes shift their first coffee to mid-morning instead of first thing, pairing it with a small, bland snack like crackers or toast. Providers who work with Retatrutide research participants often describe this as one of the more effective, low-effort adjustments patients make once nausea becomes a pattern rather than an occasional issue.

Coffee, Tea, Or Something Else: Which Option Actually Works Best

Beverage Typical Caffeine Content How It Tends To Sit With Retatrutide
Black coffee 95–165 mg per 8 oz cup Can trigger reflux and nausea on an empty stomach; better tolerated after food
Green tea 25–45 mg per 8 oz cup Gentler on digestion, lower caffeine load, often the easiest option
Herbal tea (caffeine-free) 0 mg Safest choice for people with pronounced nausea or reflux
Cold brew 150–200+ mg per 8 oz cup Higher concentration makes overstimulation more likely
Espresso 60–75 mg per 1 oz shot Small volume but very concentrated; easy to underestimate the dose

Tea is generally the more forgiving option because it delivers less caffeine per serving and contains compounds that are typically easier on an already sensitive stomach. Herbal, caffeine-free varieties are the gentlest choice of all and are often recommended first for anyone dealing with morning nausea. Coffee is not something people need to give up entirely, but shifting to a smaller cup, adding it later in the morning, or diluting it with more water are all practical middle-ground options.

Why does the type of beverage matter this much? Because Retatrutide’s effect on digestion means the stomach is doing more work with less predictable timing, and caffeine’s stimulating properties interact directly with that slower system. How this plays out varies by person, which is why tracking symptoms for the first couple of weeks tends to be more useful than following a blanket rule. Which option is best genuinely depends on individual tolerance, but starting with tea or a smaller, later coffee and adjusting from there is the approach most people land on successfully.

Patients navigating Retatrutide research protocols often report that the first two to three weeks are the period where caffeine sensitivity is most noticeable, and that small changes like switching to tea or moving coffee later in the day make a meaningful difference before the body adjusts further.

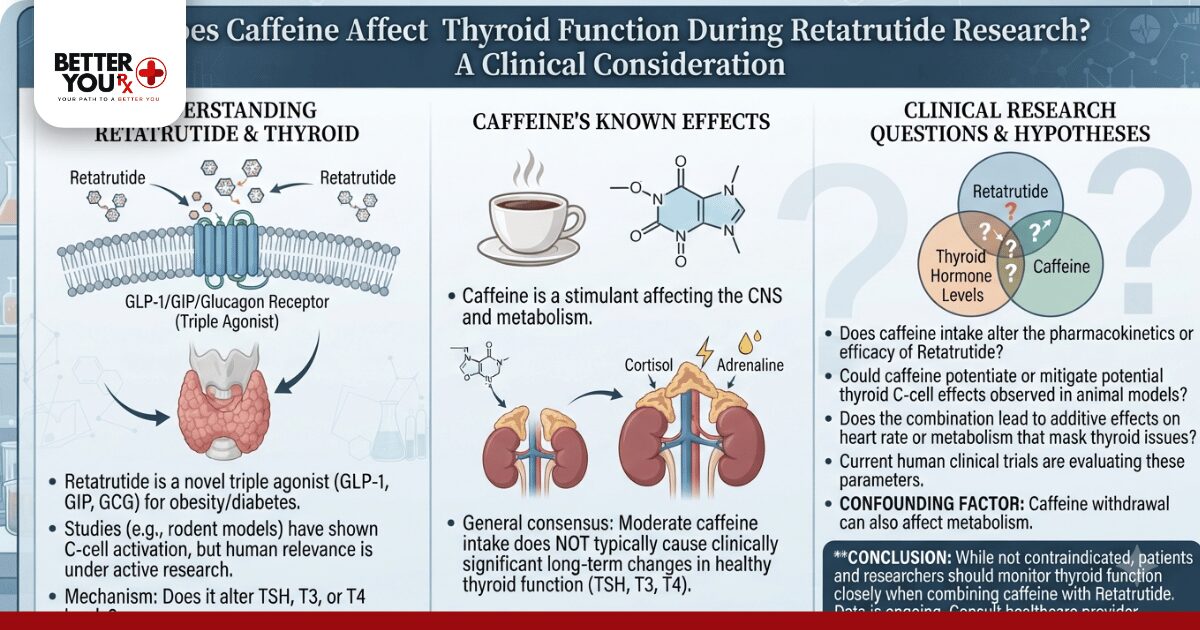
Does Caffeine Affect Thyroid Function During Retatrutide Research

Does Caffeine Affect Thyroid Function During Retatrutide Research

This question comes up often because thyroid health is part of the broader conversation around metabolic treatments. Caffeine itself does not meaningfully suppress or overstimulate thyroid hormone production in typical dietary amounts. Some research has suggested caffeine can modestly reduce the absorption of thyroid medication if taken too close together, which is a timing issue rather than a direct effect on the thyroid gland itself. For anyone with an existing thyroid condition, spacing caffeine and thyroid medication by at least 30 to 60 minutes is a standard, widely accepted practice, according to information published by Cleveland Clinic.

This aligns with established clinical understanding of how caffeine interacts with hormone-related medications generally, and most healthcare providers overseeing Retatrutide research protocols apply the same general caution here that they would for any other metabolic or hormone-adjacent treatment.

What To Avoid While Managing Retatrutide Side Effects

Category Why It Tends To Cause Problems Better Alternative
Alcohol Compounds nausea and dehydration risk Sparkling water with citrus
Greasy or fried foods Digests slowly, worsens fullness and reflux Lean proteins, steamed vegetables
High caffeine intake Stacks stimulant effects with appetite suppression Smaller portions, later timing
Carbonated sugary drinks Can increase bloating and discomfort Herbal tea, plain or infused water
Very large meals Overwhelms a slower-emptying stomach Smaller, more frequent meals

Practical Tips For Managing Coffee And Caffeine Day To Day

Start the day with water before coffee, even a small glass, since Retatrutide can dull thirst cues and mild dehydration makes nausea worse. Pair the first cup of coffee with something small in the stomach rather than drinking it completely fasted. Keep an eye on total daily caffeine from all sources, including chocolate and certain medications, since it adds up faster than people expect. If jitteriness or a racing heart shows up consistently, cutting the daily amount in half for a week is a reasonable, low-risk adjustment to try before assuming it is unrelated to caffeine at all.

Anyone exploring metabolic or weight-related treatment options can review current offerings such as Zepbound, Mounjaro, or Ozempic to understand how different approaches compare. For more background specific to this compound, Retatrutide side effects, Retatrutide vs Tirzepatide, and Retatrutide benefits go into more detail on related questions people frequently ask.

Better You Rx operates as a prescription referral service with a licensed contracted dispensing department, connecting patients across the United States with prescriptions issued by their own licensed medical doctor. Prescriptions must be written in English by a physician practicing within the United States, and all orders are mailed directly to the patient’s residence for personal use only.

Retatrutide Coffee Caffeine

Bottom Line On Retatrutide Coffee And Caffeine Habits

Coffee and tea do not need to disappear from a morning routine just because Retatrutide is part of the picture, but paying attention to timing, portion size, and beverage choice makes a real difference in how the stomach handles both. Tea tends to be the gentler option, spacing caffeine away from doses and empty-stomach moments reduces nausea, and keeping total caffeine intake moderate protects against compounding appetite suppression and heart rate changes. Small, consistent adjustments around Retatrutide coffee and caffeine habits tend to matter far more than cutting caffeine out completely.

Frequently Asked Questions

Can I drink caffeine on Retatrutide?

Yes, in moderation. Caffeine is not prohibited, but it can intensify nausea, appetite suppression, and heart rate increases, so smaller amounts and later timing tend to work best.

What is the 2 hour coffee rule?

It means waiting about two hours after a dose or first meal before coffee. It is a common personal habit, not an official medical guideline, and it helps reduce nausea on an already slower digestive system.

Can you drink tea on Reta?

Yes, tea is usually easier to tolerate than coffee. Green tea and herbal, caffeine-free varieties tend to sit better with a stomach that is digesting more slowly.

Can caffeine affect your thyroid?

Not directly in normal amounts. Caffeine can reduce absorption of thyroid medication if taken too close together, so spacing them by 30 to 60 minutes is generally recommended.

What to avoid on Retatrutide?

Alcohol, greasy foods, and excessive caffeine top the list. These tend to worsen nausea, reflux, and dehydration more than most other dietary choices.

Medical Disclaimer: This content is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Retatrutide remains under research and provider-supervised evaluation. Always consult a licensed healthcare provider before starting, stopping, or adjusting any treatment, medication, or supplement.

Sources:

  1. Mayo Clinic — Overview of caffeine’s effects on digestion, heart rate, and hydration.
  2. Cleveland Clinic — Guidance on thyroid function, hormone interactions, and medication timing.
  3. Harvard Health Publishing — Research summaries on GLP-1 and multi-receptor agonist compounds and gastrointestinal side effects.
  4. American Heart Association — Information on caffeine’s cardiovascular effects and general intake guidance.
  5. The Journal of Clinical Endocrinology & Metabolism — Peer-reviewed research on incretin-based and multi-agonist metabolic treatments.


Retatrutide for Prediabetes: What the Research Actually Shows

Written by Zas Editorial Team, Health Content Specialist | Medically Reviewed by Dr. Aiden Cross, MD | Last Updated: July 2026

Retatrutide for prediabetes is being investigated because of how the compound interacts with three separate metabolic receptors rather than just one. Early trial data shows meaningful reductions in body weight and improvements in blood sugar markers, but Retatrutide has not completed the research pathway that Semaglutide and Tirzepatide have already gone through for blood sugar management. That distinction matters for anyone trying to understand where this compound actually stands right now.

Prediabetes affects a large share of adults, and many only find out after a routine blood panel flags an elevated A1C or fasting glucose result. The condition sits in a gray zone: blood sugar is higher than normal, but not high enough to be classified as Type 2 diabetes. This is exactly the window where early intervention tends to matter most, and it is also why newer compounds like Retatrutide are being watched closely by researchers and clinicians alike.

Key Takeaways

  • Retatrutide for prediabetes is an active area of clinical research, not an approved standard treatment, and any use requires oversight from a licensed provider
  • Retatrutide works on three metabolic pathways at once (GLP-1, GIP, and glucagon receptors), which is why researchers are interested in its effect on blood sugar
  • Tirzepatide and Semaglutide have more established research behind them for prediabetes and early blood sugar concerns compared to Retatrutide
  • Dosing figures discussed in trials are research reference points only and are not a guide for self-administration
  • A1C improvement and weight reduction are the two outcomes most often measured in current Retatrutide researchWhy Retatrutide Is Being Studied for Prediabetes

Retatrutide belongs to a newer class of compounds sometimes called triple agonists. Instead of activating a single hormone receptor, it targets GLP-1, GIP, and glucagon receptors together. This combination is why early researchers became interested in Retatrutide for prediabetes specifically, since each of these pathways plays a distinct role in how the body regulates insulin sensitivity, appetite, and fat metabolism.

GLP-1 activation slows digestion and increases insulin release when blood sugar rises. GIP activation appears to improve how fat tissue processes energy. Glucagon receptor activity, the newest addition compared to older medications, is thought to increase energy expenditure. Combined, these three actions are the reason researchers have reported both weight loss and glycemic improvement in trial participants, which is a big part of why Retatrutide for prediabetes discussions keep appearing in clinical literature and patient forums alike.

Healthcare providers who follow current clinical research generally note that the interest in Retatrutide is proportional to the strength of its early trial results, not to any approval for prediabetes treatment specifically. Most providers still rely on Metformin and lifestyle intervention as the established starting point for prediabetes, while newer agents remain under closer evaluation.

How Retatrutide Compares to Other Options Studied for Blood Sugar

Retatrutide is not the only compound researchers are looking at for early blood sugar concerns. Tirzepatide, which activates two of the same three receptors, has a longer research and prescribing history. Semaglutide, a single GLP-1 agonist, has the most established track record of the three.

Compound Receptors Targeted Research Status for Blood Sugar
Retatrutide GLP-1, GIP, Glucagon Investigational, ongoing trials
Tirzepatide GLP-1, GIP Established prescribing history
Semaglutide GLP-1 Established prescribing history
Metformin Insulin sensitivity pathway Long-standing first-line option

This is where the “which option” question usually comes up. Retatrutide’s triple-receptor approach may eventually show advantages in trial data, but Tirzepatide and Semaglutide currently have more real-world prescribing experience behind their use for blood sugar related concerns. A person newly diagnosed with prediabetes is far more likely to be started on Metformin or a GLP-1 medication with an established track record, with Retatrutide remaining a research-stage option that a provider would only discuss in the context of clinical trial participation or emerging off-label interest.

Patients who ask about Retatrutide for prediabetes during a consultation are often redirected toward Semaglutide or Tirzepatide first, simply because those options have more data supporting long-term safety monitoring. This is a pattern most prescribers report seeing consistently, and it reflects how clinical decision-making tends to favor established evidence over newer compounds still under investigation.Talking to a Provider About Retatrutide for PrediabetesThings To Know About Retatrutide and Prediabetes
 

  • Retatrutide has not gone through the same review process as Semaglutide or Tirzepatide for blood sugar related use
  • Trial dosing figures such as 2mg, 4mg, 8mg, and 12mg are research reference points, not instructions for personal use
  • Weight loss and A1C changes are usually reported together in trial data because the two outcomes tend to move in parallel
  • A prediabetes diagnosis alone does not automatically qualify someone for GLP-1 based treatment, since providers typically consider A1C level, weight, and other risk factors together
  • Anyone interested in emerging options like Retatrutide should raise the topic directly with a licensed provider rather than attempting to source or dose it independently

What the Dosing Research Actually Looks Like

Clinical trials studying Retatrutide have used a titration structure, meaning the dose is increased gradually over a period of weeks rather than starting at a high amount immediately. The table below reflects publicly discussed research reference points only and is not a treatment or self-administration guide of any kind.

Trial Phase Reference Point Purpose in Research
2mg Initial titration phase studied for tolerability
4mg Mid-range titration point observed in trial data
8mg Higher dose range studied for metabolic response
12mg Upper dose range explored in later trial phases

These figures come from published trial structures and are included here purely for context. Determining whether any dose range is appropriate, along with how titration should proceed, is a decision that belongs entirely to a licensed provider working directly with a patient’s full medical history.

Why A1C and Weight Are the Two Numbers That Matter Most

Most Retatrutide research measures success using two data points: change in A1C and change in body weight. This mirrors how prediabetes itself is typically assessed and monitored over time. An A1C between 5.7 and 6.4 percent generally falls into the prediabetes range, and providers often recheck this number every three to six months to track whether it is improving, staying flat, or moving toward a Type 2 diabetes diagnosis.

Weight matters because excess body fat, particularly around the abdomen, is strongly linked to insulin resistance. This is part of why compounds like Retatrutide, which affect both appetite regulation and fat metabolism, draw so much research interest for metabolic conditions broadly, even though prediabetes specific approval has not been established.

For more detail on how Retatrutide performs across broader metabolic outcomes, Retatrutide benefits covers what current research shows beyond blood sugar alone, and Retatrutide vs Tirzepatide breaks down how the two compounds compare directly.

Retatrutide for Prediabetes

Which Option Is Actually the Right Starting Point

For most people newly diagnosed with prediabetes, the honest answer is that Retatrutide is not typically the starting point at all. Lifestyle changes, Metformin, and in some cases established GLP-1 options remain the more commonly used approach. Retatrutide’s role, for now, sits closer to ongoing research and early clinical interest rather than routine prescribing for prediabetes specifically.

That said, some patients ask their providers about Retatrutide after reading about its multi-receptor mechanism, particularly if weight has been a significant factor alongside blood sugar concerns. A provider evaluating this request will typically weigh current A1C level, weight history, other health conditions, and how established the alternative options are before considering anything outside of standard first-line treatment. This is consistent with how most healthcare providers approach any newer compound: established options are considered first, and newer research-stage compounds are discussed only when there is a clear clinical reason to do so.

To review the broader mechanism behind how Retatrutide functions in the body, what does Retatrutide do walks through the receptor activity in more detail.

Talking to a Provider About Retatrutide for Prediabetes

Bringing up Retatrutide for prediabetes during an appointment tends to go more smoothly when the conversation includes actual lab history. Providers generally want to see recent A1C results, fasting glucose numbers, and any prior attempts at lifestyle intervention before discussing whether a newer compound is even worth exploring. A patient who arrives with this information tends to have a more productive conversation than one who only mentions having read about the medication online.

Because Retatrutide remains investigational, prescribing patterns for it are still developing, and providers may take a more conservative approach compared to established options like Ozempic or Metformin. For general background on established GLP-1 options that are more commonly discussed in early blood sugar management, Ozempic, Rybelsus, and Metformin remain the more frequently prescribed starting points that a provider may bring up first.

According to a general overview published by the Mayo Clinic on prediabetes, lifestyle changes combined with regular monitoring remain the foundation of most treatment plans, regardless of which medication option is eventually considered.

Final Thoughts on Retatrutide for Prediabetes

Retatrutide for prediabetes represents an active research direction rather than a finished, provider-ready treatment option. The triple-receptor mechanism has produced encouraging early data on both weight and blood sugar, but Semaglutide, Tirzepatide, and Metformin remain the more established starting points that most providers reach for first. Anyone curious about where Retatrutide fits into their own health picture should bring lab results and questions directly to a licensed provider rather than drawing conclusions from trial headlines alone.

For a closer look at how Retatrutide’s side effect profile has been documented in research so far, Retatrutide side effects covers what current trial data has reported.

Frequently Asked Questions

Can retatrutide be used for diabetes?

Retatrutide is still investigational and is not an established treatment for diabetes. Current research is exploring its effect on blood sugar and weight, but it has not gone through the same review process as Semaglutide or Tirzepatide. Anyone with diabetes or prediabetes should discuss treatment options directly with a licensed provider.

Which GLP-1 is best for prediabetes?

Semaglutide and Tirzepatide currently have the most established research behind them for blood sugar related concerns. Both have a longer prescribing history compared to newer compounds like Retatrutide. The right option ultimately depends on individual lab results and health history, which is why provider guidance matters.

Can I use tirzepatide if I have prediabetes?

Tirzepatide is sometimes discussed by providers for patients with elevated blood sugar and weight concerns. Whether it is appropriate depends on A1C level, weight history, and other individual health factors. A licensed provider is the only one who can determine if it fits a specific case.

Does retatrutide damage kidneys?

Current research has not established a direct link between Retatrutide and kidney damage. Long-term safety data is still being collected since the compound remains in clinical trial phases. Anyone with existing kidney concerns should raise this directly with their provider before considering any GLP-1 based option.

Does reta lower A1C?

Early trial data shows Retatrutide is associated with A1C reductions in study participants. This is one of the primary outcomes researchers track alongside weight change. These results come from clinical trials rather than routine prescribing data, so individual outcomes can vary.

Medical Disclaimer: This article is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or changing any medication or treatment plan.

Sources

  1. The New England Journal of Medicine — Clinical trial data on triple hormone receptor agonists and glycemic outcomes.
  2. The Lancet — Phase 2 trial results examining Retatrutide’s effect on weight and metabolic markers.
  3. Diabetes Care (American Diabetes Association journal) — Clinical guidance on prediabetes screening and management approaches.
  4. Mayo Clinic — Patient-facing overview of prediabetes causes, risk factors, and treatment approaches.


Retatrutide For PCOS: What The Current Research Shows

Written by Amanda Cole, MSN, FNP-C | Medically Reviewed by Dr. Priya Raman, MD | Updated: July 2026

Last Updated: July 30, 2026

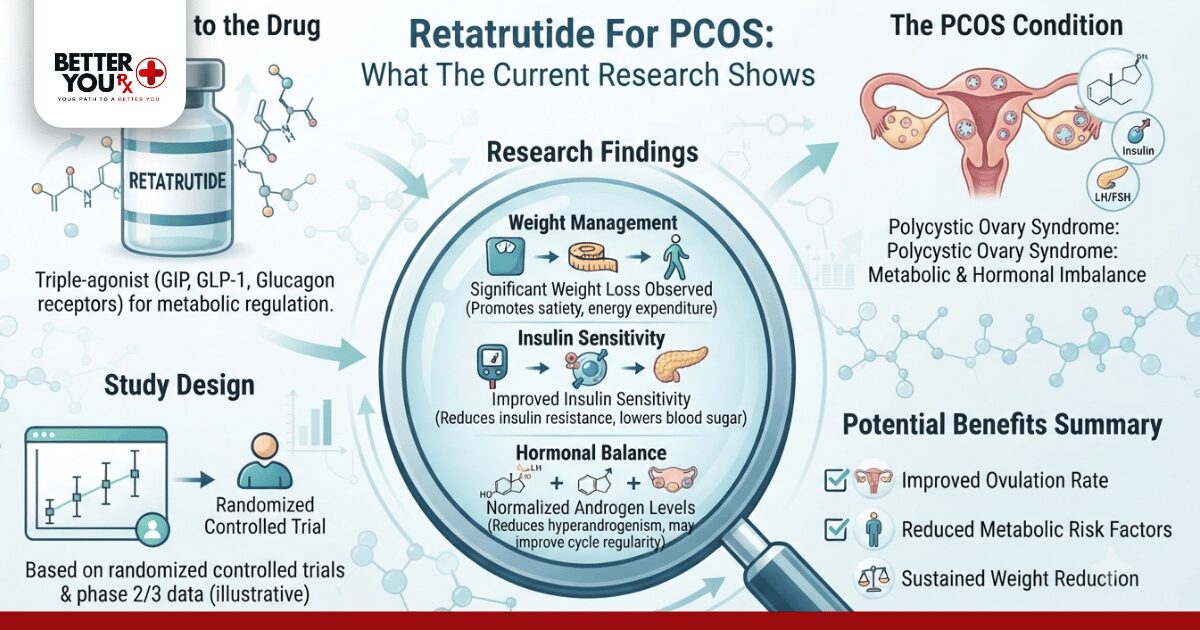
Retatrutide for PCOS is a topic more women are searching for as interest in GLP-1 and triple agonist medications grows, but the short answer is that Retatrutide is not currently approved for PCOS or any hormonal condition. It remains investigational and studied primarily for weight and metabolic outcomes, and any connection to PCOS symptom improvement is indirect, coming from how weight loss and improved insulin sensitivity tend to affect ovulation and androgen levels. Women considering this path are better served understanding the mechanism, the current evidence, and where a licensed provider fits in, rather than searching for a way to source or dose the medication independently.

Key Takeaways

  • Retatrutide for PCOS is currently a research-stage interest, not an approved treatment for Polycystic Ovary Syndrome, and any dosing information belongs to clinical trials rather than personal use
  • Retatrutide targets three gut hormone receptors at once, which is why researchers are curious about its effect on the insulin resistance that drives many PCOS symptoms
  • Weight reduction alone, achieved through any method, tends to improve ovulation and hormone markers in women with PCOS, which is the real reason Retatrutide keeps coming up in this conversation
  • Tirzepatide and Semaglutide have far more published data in women with PCOS than Retatrutide does, since Retatrutide is still investigational
  • A licensed provider who understands both PCOS and metabolic medication is the only appropriate source for a personalized recommendation

The Direct Answer: Is Retatrutide For PCOS An Established Treatment?

No. Retatrutide has not been established as a treatment for Polycystic Ovary Syndrome. It remains in clinical research for weight management and related metabolic markers, and its investigational status means dosing protocols, injection guidance, and self-administration details are appropriately left to structured trials and prescribing providers, not personal experimentation.

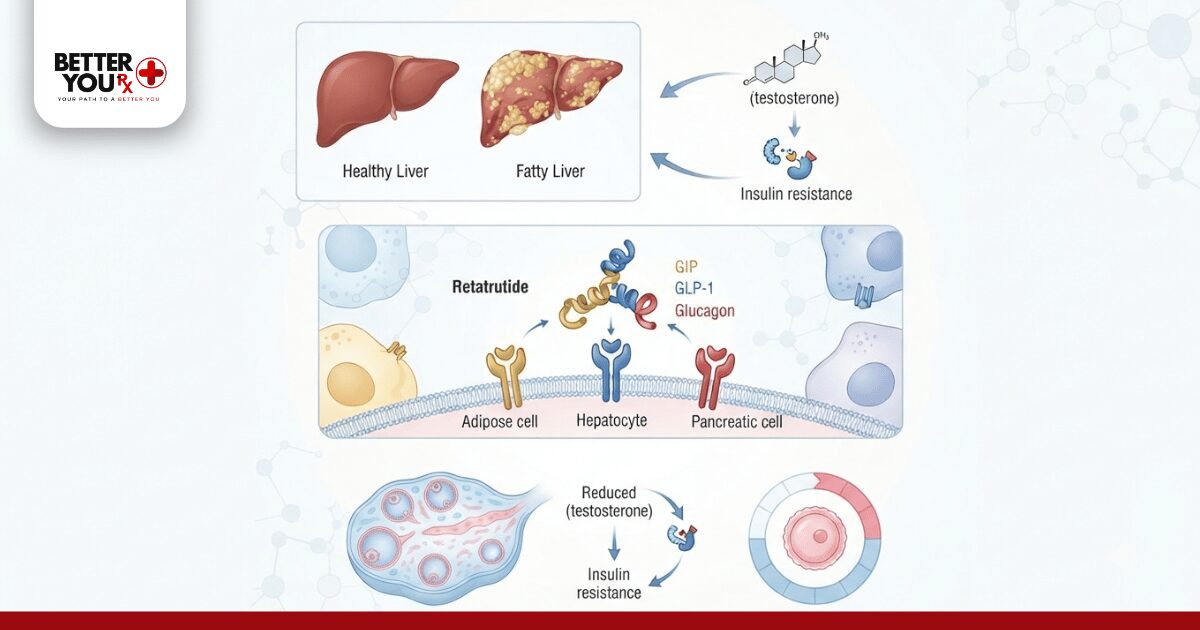
The interest comes from a reasonable place. PCOS is closely tied to insulin resistance in a large share of women who have it, and medications that improve insulin sensitivity and support weight reduction have a track record of easing some PCOS symptoms, including irregular cycles. Retatrutide’s mechanism overlaps with medications already studied in PCOS populations, which is why the question keeps surfacing even though research on Retatrutide itself is still early.

What PCOS Actually Involves

Polycystic Ovary Syndrome affects roughly one in ten women of reproductive age and shows up differently from person to person. Common features include irregular or absent periods, elevated androgen levels that can cause acne or excess hair growth, and small cysts on the ovaries visible on ultrasound. A large portion of women with PCOS also carry some degree of insulin resistance, meaning their cells do not respond to insulin as efficiently, which pushes the body to produce more insulin. That excess insulin is believed to stimulate the ovaries to produce more androgens, feeding back into irregular cycles and other symptoms.

This is why metabolic medications keep entering PCOS conversations. When insulin resistance improves, several downstream symptoms often improve with it, even though the medication itself was never designed specifically to treat PCOS.

How Retatrutide Works And Why It Is Different

Retatrutide is a triple agonist, meaning it activates receptors for GLP-1, GIP, and glucagon simultaneously. Most currently available medications, including Semaglutide, act on GLP-1 alone, while Tirzepatide combines GLP-1 and GIP. Adding the glucagon receptor is what distinguishes Retatrutide in ongoing research, and early trial data has shown meaningful effects on weight and metabolic markers in study participants.

Because insulin resistance sits at the center of so many PCOS symptoms, a medication that produces significant improvements in insulin sensitivity and weight is naturally of interest to researchers and clinicians who treat PCOS. That said, interest and evidence are not the same thing, and Retatrutide’s PCOS-specific research base is still thin compared to more established options.

Why Retatrutide For PCOS Keeps Coming Up In Research Conversations

Three overlapping factors explain the growing interest.

First, PCOS and obesity frequently coexist, and even modest weight loss, in the range of five to ten percent of body weight, has been shown to restore ovulation in some women with PCOS. A medication associated with substantial weight reduction naturally draws attention from clinicians managing this population.

Second, insulin resistance is a shared thread between PCOS and the metabolic conditions Retatrutide is being studied for, so the underlying biology overlaps even without PCOS-specific trials.

Third, patients frequently ask their providers about newer options they encounter online, and clinicians report that questions about triple agonist medications have increased noticeably as awareness of these compounds has spread. This curiosity is common and reasonable, and it is exactly the sort of question best directed toward a provider who can weigh individual health history against the current evidence.

Retatrutide Vs Tirzepatide For PCOS: Comparing What Is Actually Known

Factor Retatrutide Tirzepatide
Approval status Investigational, not approved for any indication Approved for type 2 diabetes and weight management
Receptor targets GLP-1, GIP, and glucagon GLP-1 and GIP
PCOS-specific trial data Very limited Emerging, small studies underway
Weight loss data available Strong early trial results Well established across multiple trials
Provider familiarity Lower, still emerging Higher, more prescribing experience


Tirzepatide currently has more real-world prescribing history and a stronger safety record simply because it has been available and studied longer. That does not mean Tirzepatide is automatically the better long-term choice for every patient, but it does mean the evidence supporting its use is more mature today. Retatrutide’s ceiling may prove higher once more PCOS-specific research is published, but that conclusion is not yet supported by the data available now.

Women exploring Retatrutide vs Tirzepatide for their own situation often find that the right choice depends on prior medication history, other health conditions, and what their provider has the most experience prescribing.

Things To Know

  • Retatrutide remains investigational, so self-administration guidance, reconstitution steps, and dosing schedules are not something to source outside of a clinical trial or a prescribing provider
  • Weight loss itself, not the specific medication used to achieve it, is the strongest predictor of symptom improvement in PCOS
  • Insulin resistance testing is a reasonable starting point before any metabolic medication conversation with a provider, including one about Retatrutide for PCOS
  • PCOS symptom patterns vary widely, so what works well for one woman may not be the right fit for another
  • A provider will typically want baseline labs, including hormone panels, before recommending any metabolic treatment approach

Retatrutide For PCOS

What The Research Says About Hormonal Balance

Direct evidence that Retatrutide improves hormonal imbalance in PCOS specifically is limited, since most published Retatrutide trials have focused on weight and general metabolic markers rather than reproductive hormones. What is better documented is that weight loss and improved insulin sensitivity, achieved through various methods, are associated with lower androgen levels and more regular ovulation in women with PCOS. According to MedlinePlus, lifestyle changes and medications addressing insulin resistance are commonly part of standard PCOS management.

In practice, providers who manage PCOS often describe a familiar pattern: patients who lose weight through any effective, medically supervised method frequently report their cycles becoming more predictable within a few months, even before androgen-related symptoms fully resolve. This lines up with the broader metabolic research, and it is one reason providers stay attentive to a patient’s whole metabolic picture rather than treating PCOS as a purely reproductive issue.

PCOS Symptom Believed Mechanism Relevance To Metabolic Medications
Irregular ovulation Elevated insulin driving excess androgen production Improved insulin sensitivity may support more regular cycles
Acne and excess hair growth Androgen excess affecting skin and hair follicles Weight and insulin improvements may modestly reduce androgen levels
Weight gain resistance Insulin resistance affecting fat storage Medications supporting weight loss address this mechanism directly
Fatigue and low energy Blood sugar swings tied to insulin resistance More stable glucose levels may improve daily energy

Which Option Is Actually The Best Fit

There is no single answer that applies to every woman with PCOS. For someone with more established insulin resistance, a provider may lean toward an approved option like Tirzepatide or Semaglutide simply because more prescribing experience exists. For someone earlier in their PCOS journey with milder symptoms, lifestyle changes alongside Metformin remain a well established first step many providers still recommend before considering a GLP-1 class medication at all.

Most healthcare providers follow established clinical protocols when evaluating metabolic medication options for PCOS, weighing a patient’s full history rather than reacting to a single medication name a patient has read about. The best fit is the one a licensed provider builds around an individual’s labs, symptom pattern, and treatment goals, not the newest compound in circulation.

Getting Started: What To Bring To The Conversation With Your Provider

Before discussing any metabolic medication for PCOS, it helps to arrive prepared. Bring a record of your cycle pattern over the past several months, any prior lab work including insulin and androgen levels, and a clear list of symptoms that bother you most. Providers appreciate specifics far more than a general request for “something new.”

Many women researching this topic are also exploring established options already used for weight and metabolic support, including Mounjaro Kwikpen, Zepbound Kwikpen, and Metformin, all with a longer track record in metabolic management than Retatrutide currently has.

Better You Rx operates as a prescription referral service with a licensed contracted dispensing department, connecting patients in the United States with the medications their provider prescribes once a valid prescription from a licensed physician is in place.

How Retatrutide Works And Why It Is Different

Retatrutide’s Investigational Status Deserves Respect

Retatrutide remains investigational, meaning it has not completed the review process required for approved medications, and trial data should not be treated as a green light for self-directed use. Reconstitution steps, injection technique, and dosing schedules for an investigational compound are not appropriate topics for general guidance, and any legitimate access happens through clinical trial enrollment or a prescribing provider working within an approved framework, should one become available.

For readers comparing options more broadly, resources covering Retatrutide benefits and Retatrutide side effects offer additional context on what current research does and does not support.

Moving Forward With Retatrutide For PCOS

Retatrutide for PCOS is a research question still being written, not a finished answer. Weight loss and improved insulin sensitivity, however achieved, tend to help many PCOS symptoms, and Retatrutide’s mechanism makes it a reasonable subject for future study, even though it is not yet an approved or established PCOS treatment. Women exploring metabolic medication for PCOS today have more established, better studied options available through a licensed provider, and that conversation is where real progress starts.

Is Retatrutide Safe For PCOS Patients?

Not established yet. Retatrutide is investigational, so its safety profile specifically in women with PCOS has not been formally studied or confirmed, and any use outside of clinical trials falls outside approved medical guidance.

Can Retatrutide Help With Hormonal Imbalance?

Indirectly, possibly. Retatrutide has not been directly studied for hormonal imbalance, but the weight loss and insulin improvements associated with it may support more balanced hormone levels, similar to patterns seen with other metabolic medications.

Is Reta Or Tirzepatide Better For PCOS?

Tirzepatide has more evidence. Tirzepatide is approved and has more real-world prescribing history, while Retatrutide remains investigational with far less PCOS-specific data available today.

Which GLP Is Best For PCOS?

It depends on the individual. Semaglutide and Tirzepatide currently have the most supporting data for PCOS-related weight and metabolic improvement, though the right choice depends on a person’s health history and provider guidance.

Can Reta Cause Infertility?

No evidence supports this. There is no established research linking Retatrutide to infertility, and in fact, weight loss achieved through metabolic medications has more often been associated with improved, not reduced, fertility markers in women with PCOS.

Sources

  • Journal of Clinical Endocrinology and Metabolism, Endocrine Society: Clinical research on insulin resistance and its role in Polycystic Ovary Syndrome
  • Mayo Clinic: Overview of Polycystic Ovary Syndrome causes, symptoms, and standard management approaches
  • The Lancet Diabetes and Endocrinology: Published trial data on triple agonist and dual agonist metabolic medications
  • American Society for Reproductive Medicine: Clinical guidance on weight management and ovulatory function in PCOS
  • New England Journal of Medicine: Peer reviewed trial results on GLP-1 and multi-receptor agonist compounds

Medical Disclaimer: This content is for informational purposes only and is not intended as medical advice. It does not replace a consultation with a licensed healthcare provider. Always speak with a qualified physician before starting, stopping, or changing any medication or treatment plan, particularly regarding investigational compounds such as Retatrutide.

Is Retatrutide For Fatty Liver An Effective Option?

Written by The Better You Rx Clinical Content Team | Medically Reviewed by Dr. Sarah Mitchell, MD | Last Updated: August 2026

Retatrutide for fatty liver has become one of the most researched questions in metabolic medicine today. Early clinical research suggests this investigational peptide may reduce liver fat by supporting significant weight loss and improving insulin sensitivity, though it remains under study and is not yet a standard treatment. Retatrutide targets three separate hormone receptors, GIP, GLP-1, and glucagon, a combination that appears to produce more pronounced metabolic effects than single-receptor therapies. For people managing excess liver fat alongside obesity or prediabetes, this triple-action approach is drawing significant attention from both researchers and patients.

Key Takeaways

  • Retatrutide for fatty liver research is still emerging, but early trial data shows meaningful reductions in liver fat content among participants with obesity.
  • Retatrutide activates GIP, GLP-1, and glucagon receptors simultaneously, a mechanism that distinguishes it from Semaglutide and Tirzepatide.
  • Weight loss and improved insulin sensitivity appear to be the primary pathways through which Retatrutide may support liver health.
  • Retatrutide remains an investigational medication, and any use should occur only under the guidance of a licensed healthcare provider.
  • Comparing GLP-1 and multi-receptor options helps patients and providers determine which approach best fits individual metabolic goals.


The Direct Answer On Retatrutide For Fatty Liver

Retatrutide shows early promise for reducing liver fat, primarily as a downstream result of substantial weight loss and improved metabolic function rather than a direct liver-targeted mechanism. Clinical researchers have observed that participants using Retatrutide in study settings experienced measurable reductions in liver fat percentage alongside broader improvements in body weight and blood sugar regulation.

This does not mean Retatrutide functions as a dedicated liver medication. Fatty liver improvement observed in research settings appears connected to the same mechanisms that drive weight reduction: appetite regulation, slower gastric emptying, and improved how the body processes glucose and fat. Because excess liver fat is closely tied to obesity and insulin resistance, medications that meaningfully address those two factors often show secondary benefits for liver health.

What Is Fatty Liver Disease and How Metabolic Health Plays a Role

Fatty liver disease develops when fat accumulates in liver cells beyond what is considered normal. It ranges from a milder buildup with no symptoms to a more advanced form involving inflammation and scarring. According to the Cleveland Clinic’s overview of nonalcoholic fatty liver disease, the condition is closely linked to obesity, type 2 diabetes, and elevated cholesterol, making it one of the most common liver conditions affecting adults today.

Metabolic health and liver fat are deeply connected. When the body struggles to regulate blood sugar and insulin, the liver often compensates by storing more fat. This creates a cycle where excess liver fat can worsen insulin resistance, which in turn can allow more fat to accumulate. Breaking this cycle typically requires addressing the underlying metabolic drivers rather than the liver in isolation, which is part of why medications like Retatrutide, originally developed for weight management, are being studied for their liver-related effects.

For patients researching Retatrutide for fatty liver, knowing the baseline severity of liver fat buildup matters before starting any new treatment. Providers typically rely on bloodwork markers such as liver enzymes, alongside imaging when available, to establish a starting point. This baseline allows for meaningful comparison later in treatment, since liver fat changes are gradual and best tracked over months rather than weeks. Patients with mild fat accumulation and those with more advanced changes may see different rates of improvement, which is another reason individualized provider guidance carries so much weight in this process.

Retatrutide For Fatty Liver

How Retatrutide May Support Liver Fat Reduction

Retatrutide’s triple-receptor mechanism appears to influence liver fat through several connected pathways rather than a single direct action. GLP-1 receptor activation slows digestion and reduces appetite, GIP receptor activation may improve how fat cells store and release energy, and glucagon receptor activation is believed to increase energy expenditure. Together, these actions support the kind of substantial weight loss that research has repeatedly linked to liver fat reduction.

Mechanism How It May Support Liver Fat Reduction
GLP-1 Receptor Activation Reduces appetite and slows digestion, supporting sustained calorie reduction
GIP Receptor Activation May improve fat cell metabolism and insulin sensitivity
Glucagon Receptor Activation Believed to increase resting energy expenditure, supporting fat loss
Combined Weight Loss Effect Substantial weight reduction is consistently associated with lower liver fat percentage in research settings


Providers who discuss Retatrutide for fatty liver with patients typically emphasize that liver fat improvement tracks closely with overall weight loss progress. Patients who lose a meaningful percentage of body weight during treatment tend to show the most noticeable reductions in liver fat on imaging, which is consistent with what clinicians observe across other weight management therapies as well.

Things To Know

  • Retatrutide is still considered investigational and has not been established as a first-line treatment specifically for fatty liver disease.
  • Liver fat reduction observed in research appears connected to weight loss rather than a standalone liver-targeted effect.
  • Most healthcare providers follow established clinical protocols when considering GLP-1 and multi-receptor therapies for patients with metabolic risk factors, including elevated liver fat.
  • Any decision to pursue Retatrutide should involve bloodwork, imaging, and ongoing monitoring by a licensed healthcare provider.
  • Lifestyle factors such as diet quality, physical activity, and alcohol intake continue to play a meaningful role in liver health regardless of medication use.

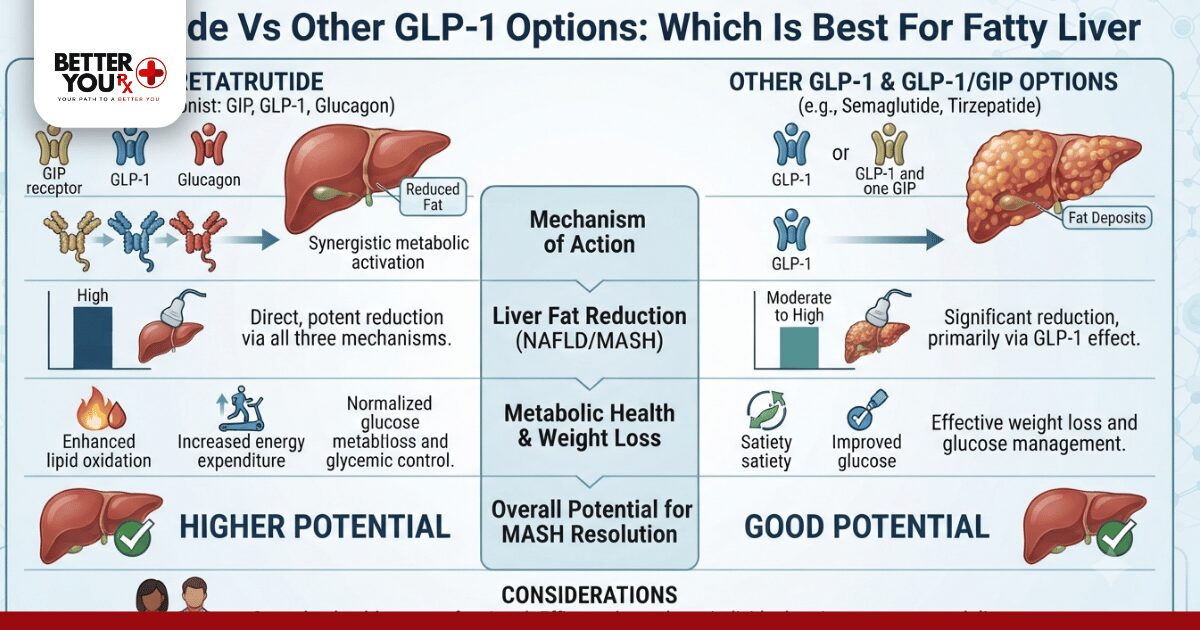
Retatrutide Vs Other GLP-1 Options: Which Is Best For Fatty Liver

Choosing between Retatrutide, Tirzepatide, and Semaglutide often comes down to how each medication’s receptor activity aligns with a patient’s specific metabolic profile. Semaglutide, sold under brand names like Ozempic and Wegovy, works through GLP-1 receptor activation alone. Tirzepatide, found in Mounjaro and Zepbound, combines GLP-1 and GIP receptor activity. Retatrutide adds a third receptor, glucagon, to that combination.

Medication Receptor Activity Why It May Matter For Liver Fat
Semaglutide GLP-1 only Reliable weight loss with a well-established research history
Tirzepatide GLP-1 and GIP Dual mechanism associated with greater average weight loss than GLP-1 alone
Retatrutide GLP-1, GIP, and Glucagon Triple mechanism under study for potentially greater metabolic and weight loss effects

Why does the number of receptors matter for liver fat specifically? Because liver fat reduction in research has consistently correlated with the magnitude of weight loss achieved. How this plays out clinically is that medications producing greater average weight loss in trials have also shown greater average reductions in liver fat on imaging.

Which option is best depends on the individual, since Semaglutide may be appropriate for patients seeking a well-established option, while Tirzepatide or Retatrutide may be considered for patients with higher metabolic burden who have not achieved sufficient results with single-receptor therapy. A licensed healthcare provider is best positioned to weigh these factors against a patient’s full medical history.

What Patients And Providers Typically Observe During Treatment

In clinical practice, providers often report that patients pursuing GLP-1 and multi-receptor therapies for metabolic concerns describe steady, gradual changes rather than immediate results.

Liver fat reduction is not something a patient feels day to day. It is typically identified through follow-up imaging or bloodwork ordered by a provider tracking metabolic progress over several months. Patients frequently mention noticing improved energy and reduced appetite before any liver-specific improvement becomes measurable, which aligns with the sequence researchers have observed: weight loss tends to precede detectable liver fat reduction.

This gradual pattern is one reason ongoing provider supervision matters throughout treatment. Adjustments to dosing, monitoring for side effects, and tracking metabolic markers are all part of a structured approach that a qualified provider oversees, rather than something managed independently by the patient.

A common scenario providers describe involves a patient who begins treatment primarily focused on weight loss, only to discover during a routine follow-up that liver enzyme levels have also improved. This kind of secondary finding reinforces why regular check-ins matter, even when a patient feels the treatment is “just” working on appetite or weight. Metabolic health tends to improve across several markers together, and liver fat is often one of the last changes to become visible on imaging, even though the underlying improvement may already be underway.

Getting Started With Retatrutide

For patients whose provider has determined that Retatrutide or a related metabolic medication may be appropriate, Better You Rx operates as a prescription referral service with a licensed contracted dispensing department, connecting patients across the United States with contracted partners who fulfill valid prescriptions issued by a licensed U.S. medical provider. Patients exploring Mounjaro Kwikpen or Zepbound Kwikpen as GLP-1 and dual-receptor options, or Saxenda as an additional weight management alternative, can review these options alongside their provider before deciding on the right fit.

Every referral requires a valid prescription written in English by a licensed medical doctor practicing in the United States. Once a prescription is confirmed, medications are mailed directly to the patient’s residence for personal use only, with no clinic or office deliveries involved.

To better understand how Retatrutide compares to related therapies, patients often review Retatrutide benefits, explore Retatrutide vs Tirzepatide for a side-by-side breakdown, or read more on what Retatrutide does in the body before discussing options with their provider.

How Retatrutide May Support Liver Fat Reduction

The Bottom Line On Retatrutide For Fatty Liver

Retatrutide for fatty liver represents a genuinely promising area of ongoing research, grounded in the well-established relationship between weight loss, improved insulin sensitivity, and reduced liver fat. The medication’s triple-receptor mechanism sets it apart from earlier GLP-1 therapies, and early data suggests meaningful potential for patients managing both excess weight and elevated liver fat. Because Retatrutide remains investigational, decisions about whether it fits a patient’s treatment plan should always involve a licensed healthcare provider who can evaluate bloodwork, imaging, and overall metabolic history before moving forward.

Frequently Asked Questions

Can retatrutide help fatty liver?

Early research suggests Retatrutide may reduce liver fat, primarily through weight loss and improved insulin sensitivity rather than a direct liver-targeted effect. Ongoing studies continue to evaluate the extent and consistency of this benefit.

Which GLP-1 is best for fatty liver?

No single GLP-1 medication is universally best, since the right option depends on a patient’s metabolic profile and how much weight loss is needed. Tirzepatide and Retatrutide have shown larger average weight loss than Semaglutide alone in research settings.

How quickly does retatrutide work?

Weight loss and metabolic changes typically build gradually over several months of consistent use under provider supervision. Liver fat reduction tends to follow weight loss rather than occurring immediately.

What is the best peptide for fatty liver?

There is no single confirmed “best” peptide for fatty liver, though Retatrutide’s triple-receptor mechanism is being studied for its potential metabolic benefits. A provider can help determine which option aligns with individual health needs.

Does retatrutide help visceral fat?

Early research indicates Retatrutide may reduce visceral fat as part of its broader effect on total body weight and fat distribution. Visceral fat reduction is closely linked to the same metabolic improvements associated with liver fat reduction.

Sources

  1. Cleveland Clinic, Nonalcoholic Fatty Liver Disease, overview of causes, risk factors, and the connection between liver fat and metabolic health.
  2. Journal of Hepatology, peer-reviewed research on the relationship between weight loss interventions and liver fat reduction in patients with obesity.
  3. Mayo Clinic, Obesity and Metabolic Health, overview of how excess weight contributes to insulin resistance and related liver changes.
  4. American Liver Foundation, patient-facing resource on fatty liver disease progression and lifestyle-related risk factors.
  5. Diabetes, Obesity and Metabolism, clinical research publication covering multi-receptor peptide therapies and their metabolic effects.

Medical Disclaimer

This content is provided for informational purposes only and is not intended as medical advice. It should not be used to diagnose or treat any health condition and does not replace the guidance of a licensed healthcare provider. Always consult a qualified medical professional before starting, stopping, or changing any medication or treatment plan, including Retatrutide or any related therapy.

Retatrutide for Sleep Apnea: What Patients Should Know

Written by Amanda Reyes, BSN, RN | Medically Reviewed by Dr. Michael Torres, MD | Updated: August 2026

Last Updated: August 2026

Retatrutide for sleep apnea has not been studied directly, but the substantial weight loss associated with it in early research works through the same mechanism that makes Tirzepatide and Semaglutide effective for reducing sleep apnea severity in people carrying excess weight around the neck and airway. Because Retatrutide remains investigational, providers currently lean on medications with more established research when sleep apnea is the primary concern, while Retatrutide continues to be studied for broader metabolic outcomes. Weight loss, sleep disruption during early treatment, and which option currently has the strongest evidence behind it for sleep apnea specifically are the questions patients ask most.

Key Takeaways

  • Retatrutide for sleep apnea works indirectly through significant weight loss, since weight loss is one of the most reliable ways to reduce obstructive sleep apnea severity.
  • Retatrutide is still investigational, so figures referenced in research are reference points only. A licensed provider determines what is appropriate for any individual.
  • Sleep disruption is commonly reported during early weight loss treatment, often tied to appetite changes or digestive adjustment.
  • Tirzepatide and Semaglutide currently have more published data specific to sleep apnea than Retatrutide.
  • Public figures like Shaquille O’Neal have drawn attention to sleep apnea and weight management, but individual results vary and are never a substitute for a sleep study.

Does Retatrutide Help With Sleep Apnea?

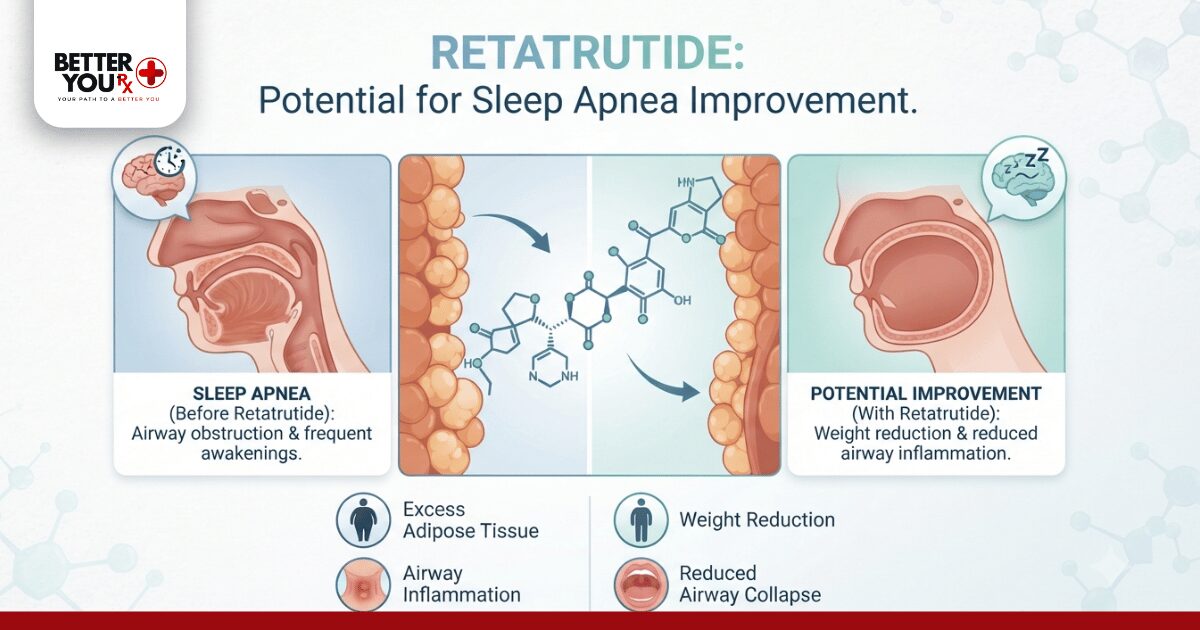
Retatrutide has not been the subject of a dedicated sleep apnea study the way some other incretin-based medications have. What it does have is strong early data showing substantial reductions in body weight, and weight is one of the most significant contributing factors to obstructive sleep apnea. When neck circumference and abdominal fat decrease, airway collapsibility during sleep tends to decrease as well, which is why weight loss medications in general are relevant to a sleep apnea conversation even without a trial designed around sleep as the primary outcome.

Sleep medicine specialists describe obstructive sleep apnea as a mechanical problem where soft tissue in the throat relaxes and narrows the airway during sleep. Excess fat around the neck and tongue base makes that narrowing more likely and more severe. Reducing that fat load through meaningful weight loss is one of the few interventions that can change the underlying anatomy rather than simply managing symptoms overnight.

What Is Retatrutide?

Retatrutide is an investigational triple agonist medication that acts on three separate gut hormone receptor pathways involved in appetite regulation and metabolism. It belongs to the same broader medication family as Tirzepatide and Semaglutide, though it targets an additional pathway that early researchers believe contributes to its notably strong weight loss results in research settings. Because Retatrutide is still investigational, dosing figures in research literature are reference points for scientific context only, never a substitute for what a licensed provider determines appropriate for an individual patient. Providers prescribing this medication class typically follow established clinical protocols, extending extra caution where long-term safety data is still limited.

Retatrutide for Sleep Apnea: What the Research Shows

The connection between Retatrutide and sleep apnea outcomes is currently indirect. Researchers have not published a trial measuring apnea-hypopnea index changes specifically for Retatrutide. What does exist is early phase research showing average body weight reductions larger, on a percentage basis, than those typically observed with older weight management medications.

Because obstructive sleep apnea severity correlates closely with body weight, especially visceral and neck fat, clinicians reasonably expect similar weight reductions from Retatrutide to produce similar downstream improvements in breathing during sleep. That expectation, however, is extrapolation from weight data, not a confirmed clinical finding. Patients considering Retatrutide for sleep apnea should understand this distinction before assuming the outcome is guaranteed.

Medication Sleep Apnea Specific Research Typical Reported Weight Loss Range*
Tirzepatide Dedicated sleep apnea research published 15% to 20%
Semaglutide Related cardiometabolic and weight research available 10% to 15%
Retatrutide Weight loss research only; no dedicated sleep apnea trial published 17% to 24%

*Figures reflect published research averages and are reference points only, not individual guarantees.

A sleep medicine provider evaluating a patient with obesity and diagnosed obstructive sleep apnea typically considers several factors before recommending any medication in this class, including current apnea-hypopnea index, cardiovascular history, and how much weight loss would realistically change airway function.

Retatrutide for Sleep Apnea

Things To Know

  • Weight loss of even 10% of body weight has been linked to measurable reductions in sleep apnea severity in published research.
  • Retatrutide’s third receptor pathway is believed to drive its comparatively larger average weight loss results, though this mechanism is still being studied.
  • Sleep apnea severity is typically measured using the apnea-hypopnea index, which counts breathing interruptions per hour of sleep.
  • A continuous positive airway pressure device remains the standard first-line treatment for moderate to severe obstructive sleep apnea regardless of weight loss progress.
  • No weight loss medication, including Retatrutide, is intended to replace a diagnosed sleep apnea treatment plan.

How Weight Loss Changes Airway Function During Sleep

The throat is surrounded by soft tissue, muscle, and fat that naturally relax during sleep. In people carrying extra weight around the neck and upper body, that relaxed tissue has less room to move without partially or fully blocking airflow, which is why obstructive sleep apnea is so strongly linked to body weight.

As body weight decreases, soft tissue around the airway typically decreases too, reducing how often the airway collapses during sleep. Patients who lose a meaningful percentage of body weight often report needing lower pressure settings on their airway devices. According to the Sleep Foundation, weight management is considered one of the most effective non-device strategies for improving sleep apnea outcomes over time.

This is also why Tirzepatide, sold under the brand names Mounjaro and Zepbound, has become a frequent topic in sleep medicine circles. Its weight loss results were large enough that researchers measured whether that weight loss translated into fewer breathing interruptions during sleep, and results showed a meaningful reduction in apnea events for many participants.

Which GLP-1 Option Is Best for Sleep Apnea?

Choosing between Retatrutide, Tirzepatide, and Semaglutide for a sleep apnea related goal depends on what stage of research each medication has reached.

Why weight loss magnitude matters: Sleep apnea improvement tends to track with the amount of weight lost, so a medication associated with larger average weight reductions has a plausible advantage on paper. This is part of why Retatrutide draws interest, since its early research shows some of the largest average weight loss figures reported among this medication class.

How providers currently decide: Providers weigh how much clinical evidence exists for a medication in the specific context being treated. Tirzepatide currently has dedicated published research showing improvement in breathing events during sleep, which gives providers more confidence recommending it for that particular goal.

Which option is generally considered best: Tirzepatide currently has the most direct supporting research for sleep apnea, followed by Semaglutide, with broader cardiometabolic data supporting its safety profile. Retatrutide remains a reasonable option to discuss for weight management broadly, but not yet the option with dedicated sleep apnea research behind it. A provider reviewing a patient’s sleep study, weight history, and overall health is best positioned to determine what fits.

Consideration Tirzepatide Semaglutide Retatrutide
Sleep apnea specific data Available Limited Not yet available
Receptor pathways targeted Two One Three
Research maturity Established Established Investigational

Patients interested in learning more about how Retatrutide compares to Tirzepatide in broader research contexts can review how the two medications differ beyond sleep apnea specifically, since overall metabolic effects, side effect profiles, and research maturity all factor into a provider’s recommendation.

Retatrutide for Sleep Apnea What the Research Shows

Why Sleep Problems Can Happen During Treatment

Some patients starting a GLP-1 or triple agonist medication report new sleep difficulty rather than improvement, at least in the early weeks. This is a real and commonly reported experience with a few explanations rather than one single cause.

Appetite suppression can shift when and how much a person eats in the evening, and digestive adjustment, including nausea or delayed stomach emptying, can make lying down uncomfortable at bedtime. Some patients also describe lighter sleep during the first few weeks as their body adjusts to hormonal changes affecting appetite and digestion signaling. Sleep specialists commonly observe that this early disruption tends to ease as the body adapts, though persistent sleep difficulty should always be raised with a provider rather than left to resolve on its own.

For patients taking Retatrutide, this is layered with the medication’s investigational status. Because long-term data is more limited than for Tirzepatide or Semaglutide, providers tend to monitor patients more closely for new symptoms, including sleep changes, during early treatment.

What Are the Risks of Taking a Medication Like Retatrutide?

Retatrutide shares a general side effect profile with other medications in its family, including nausea, digestive discomfort, and appetite changes most pronounced early in treatment. Because it is investigational, its long-term safety profile is less established than Tirzepatide or Semaglutide, both of which have years of broader clinical use behind them.

Patients considering Retatrutide should discuss their full medical history with a provider, including any thyroid, pancreatic, or gastrointestinal concerns. A provider is the appropriate person to determine whether current sleep apnea severity, cardiovascular health, and weight history make this class of medication reasonable at all.

Is Retatrutide for Sleep Apnea a Realistic Option Right Now?

Retatrutide for sleep apnea is a reasonable topic to raise with a provider, particularly for patients already candidates for weight management treatment who also carry a sleep apnea diagnosis. It is not currently positioned as a first-line sleep apnea treatment the way Tirzepatide has become for some patients, simply because the dedicated research has not caught up yet.

Patients exploring their weight management medication options often ask their provider to walk through established versus investigational choices, and a thorough sleep history combined with a current sleep study gives a provider the clearest picture of what fits. Reviewing how Retatrutide affects the body more broadly also helps patients understand what to expect beyond the sleep apnea question.

Getting Started

Patients exploring whether a GLP-1 or triple agonist medication fits their weight and sleep health goals typically start with their prescribing provider, followed by a referral through Better You Rx, a prescription referral service with a licensed contracted dispensing department that connects patients with appropriate options once a prescription has been issued.


Final Word on Retatrutide for Sleep Apnea

Retatrutide for sleep apnea is an emerging area of interest rather than an established treatment path today. The weight loss associated with Retatrutide in early research is meaningful, and weight loss remains one of the most reliable ways to reduce obstructive sleep apnea severity over time, but the direct research connecting Retatrutide to sleep apnea outcomes has not yet been published.

Patients with a sleep apnea diagnosis considering weight management treatment are best served by a conversation with their provider, a current sleep study, and an honest look at which medication currently has the strongest evidence behind it. For further reading, patients can review Retatrutide benefits for additional context on how this medication class is evolving, and learn more about Saxenda as another established weight management option.

Frequently Asked Questions

Does Retatrutide Help With Sleep Apnea?

Not directly, but the weight loss associated with Retatrutide can reduce sleep apnea severity in the same way weight loss from other medications does. No dedicated Retatrutide sleep apnea trial has been published, so this remains an extrapolation from weight loss data rather than a confirmed outcome.

What Are the Risks of Taking Retatrutide?

Common risks include nausea, digestive discomfort, and appetite changes, along with less established long-term safety data since Retatrutide is investigational. A provider should review personal medical history, including thyroid and pancreatic conditions, before considering this medication.

Which GLP-1 Drug Is Best for Sleep Apnea?

Tirzepatide currently has the most dedicated sleep apnea research behind it, making it the option providers most often discuss for that specific goal. Semaglutide follows with broader supporting data, while Retatrutide remains under investigation for this particular use.

Why Can’t I Sleep on Retatrutide?

Early sleep disruption is a commonly reported experience, often linked to appetite changes, digestive adjustment, or the body adapting to new hormonal signaling. This tends to ease over the first several weeks, though persistent issues should be discussed with a provider.

How Did Shaq Fix His Sleep Apnea?

Shaquille O’Neal has spoken publicly about managing his sleep apnea through a combination of weight-focused lifestyle changes and consistent use of a CPAP device as advised by his medical team. His experience reflects a broader pattern where weight management and standard sleep apnea treatment work together rather than either approach standing alone.

Sources

  1. New England Journal of Medicine: Clinical research on GLP-1 and triple agonist receptor medications and weight loss outcomes.
  2. The Lancet: Peer-reviewed research on incretin-based therapies and metabolic health.
  3. Mayo Clinic: Patient education on the causes and treatment of obstructive sleep apnea.
  4. Cleveland Clinic: Clinical overview of weight management medications and their role in metabolic health.
  5. Sleep Foundation: Research summaries on the relationship between weight loss and sleep apnea severity.

This content is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or changing any medication or treatment plan.

Retatrutide For Postpartum Weight Loss: What New Mothers Should Know


Written by Sarah Mitchell, Health and Wellness Writer  |  Medically Reviewed by Dr. Amanda Cole, MD  |  Updated: August 2026

Last Updated: August 5, 2026

Retatrutide for postpartum weight loss is a topic drawing attention as new mothers look for medically guided ways to manage weight gained during pregnancy. Retatrutide itself is a triple-hormone receptor agonist still moving through clinical trials, and it has not been established as a standard treatment for postpartum weight loss specifically.

Because hormone shifts, breastfeeding needs, and physical recovery all shape a mother’s health after delivery, any interest in Retatrutide or a similar medication should begin with a conversation with a licensed healthcare provider familiar with her full history.

Weight loss after birth tends to respond best to a combination of balanced nutrition, gradual movement, adequate rest, and, when appropriate, medical guidance tailored to whether a mother is breastfeeding, how her delivery recovery is progressing, and what her broader health picture looks like.

Key Takeaways

  • Retatrutide is an investigational medication still moving through clinical research, and it is not currently an established, routine treatment specifically for postpartum weight loss
  • Postpartum weight loss differs from general weight loss because of hormonal shifts, breastfeeding demands, and the body’s physical recovery timeline after childbirth
  • Retatrutide is designed to act on three separate hormone receptor pathways tied to appetite and metabolism, which sets it apart from single or dual-action medications like Semaglutide or Tirzepatide
  • Safety data on Retatrutide use during breastfeeding is limited, so any treatment decision for a new mother should involve a licensed healthcare provider
  • A gradual, provider-guided approach that accounts for nutrition, activity, and recovery timing tends to produce steadier, more sustainable results than searching for a fast fix

Retatrutide For Postpartum Weight Loss: The Direct Answer

There is currently no established clinical protocol for using Retatrutide specifically for postpartum weight loss. Retatrutide remains a research compound, meaning it is still being studied in clinical trials for weight management in the general population, and dedicated research on new mothers, postpartum recovery, or breastfeeding has not been completed. Providers who discuss Retatrutide with patients typically frame it as an emerging option worth watching rather than a therapy that is ready to prescribe for postpartum use today.

That distinction matters because postpartum bodies are not the same as bodies at other life stages. Hormone levels are shifting, milk supply may depend on adequate caloric intake, and recovery from vaginal delivery or a cesarean birth requires time. Any medication considered during this window, including Retatrutide, needs to be evaluated against those specific factors rather than treated as interchangeable with weight loss approaches used outside of the postpartum period.

What Is Retatrutide?

Retatrutide is part of a newer class of injectable medications being studied for weight management. Unlike Semaglutide, which acts primarily on the GLP-1 receptor, Retatrutide is designed as a triple agonist, meaning it targets three separate receptors: GLP-1, GIP, and Glucagon. Researchers believe combining these three pathways may produce a stronger effect on appetite regulation and energy expenditure than medications that act on just one or two of them.

Tirzepatide, found in Mounjaro and Zepbound, already combines two of these pathways, GLP-1 and GIP, and has shown meaningful results in clinical trials. Retatrutide adds the glucagon receptor to that combination, which is part of why it has generated so much interest among researchers and patients following weight management news. Because the compound is still investigational, dosing protocols, injection technique, and administration details are not something a patient should attempt to learn or apply without direct guidance from a licensed prescriber, and this piece intentionally does not walk through those steps.

Retatrutide For Postpartum Weight Loss What New Mothers Should Know

Why Postpartum Weight Loss Is Different From Other Weight Loss

Losing weight after having a baby is not simply a smaller version of general weight loss. Several factors are unique to this stage of life, and providers weigh all of them before recommending any approach, medication-based or otherwise.

Hormone levels, including estrogen, progesterone, and prolactin, shift dramatically after delivery and continue adjusting for months. These changes affect appetite, metabolism, mood, and even how the body stores and releases fat. A mother who is exclusively breastfeeding also has different caloric needs than one who is not, since milk production requires consistent energy intake.

Sleep deprivation is another factor that rarely gets enough attention. Many new mothers report that interrupted sleep affects cravings and energy levels in ways that make weight management harder than it was before pregnancy. Physical recovery matters as well. A body recovering from a cesarean delivery, for example, needs time before returning to more vigorous activity, and pushing too soon can slow healing rather than support it.

How Retatrutide Works In The Body

To understand why Retatrutide for postpartum weight loss keeps coming up in conversation, it helps to understand the mechanism researchers are studying. The medication is designed to mimic three naturally occurring hormones involved in digestion and metabolism. GLP-1 slows stomach emptying and signals fullness to the brain. GIP is involved in insulin regulation and fat metabolism. Glucagon affects how the body uses stored energy.

By acting on all three pathways at once, Retatrutide is intended to produce a more pronounced effect on appetite and calorie burning than medications that target only one or two of these receptors. Clinical trial data in general adult populations has shown notable weight loss results, which is part of why interest in the medication has grown quickly, including among people evaluating options after childbirth.

Medication Receptor Targets Approval Status Common Brand Examples
Semaglutide GLP-1 Established, widely studied Ozempic, Wegovy, Rybelsus
Tirzepatide GLP-1 and GIP Established, widely studied Mounjaro, Zepbound
Retatrutide GLP-1, GIP, and Glucagon Investigational, still in clinical trials Not yet commercially branded

Why Postpartum Weight Loss Is Different From Other Weight Loss

Things To Know

  • Retatrutide is not currently available as a standard prescription option because it remains under clinical investigation
  • No dedicated safety studies currently exist on Retatrutide use during breastfeeding or immediately postpartum
  • Weight loss medications in general are typically not recommended in the earliest weeks after delivery while the body is still healing
  • A primary care provider or OB-GYN is the appropriate first point of contact for any postpartum weight management question
  • Nutrition adequacy matters more than speed of weight loss for mothers who are breastfeeding, since milk supply depends on consistent caloric intake
  • Weight retained after pregnancy often decreases gradually over 6 to 12 months for many mothers, even without medication intervention

Which Option Is Applicable? Comparing Postpartum Weight Management Approaches

New mothers considering how to approach postpartum weight loss usually fall into a few different categories, and the right approach depends heavily on individual circumstances such as breastfeeding status, delivery recovery, and overall health. The table below outlines how providers commonly think through these categories, though every recommendation should ultimately come from a one-on-one conversation with a healthcare provider.

Situation Typical First-Line Approach Why It Is Recommended
First 6 weeks postpartum, any delivery type Rest, hydration, gentle movement, no medication The body needs time to heal before adding new variables
Exclusively breastfeeding Nutrition-focused approach with provider monitoring Caloric restriction or new medications can affect milk supply
Not breastfeeding, fully healed, 3 months or more postpartum Structured nutrition and activity plan, medication discussion if appropriate More flexibility exists once healing and hormone shifts have stabilized
History of postpartum depression or anxiety Coordinated care between mental health and physical health providers Weight management plans work better alongside emotional wellbeing support

In practice, many healthcare providers see mothers who ask about medications like Retatrutide within the first few postpartum visits, often after reading about the medication online. Providers generally explain that while the science behind triple-hormone agonists is promising, the honest answer for now is that patience, a realistic timeline, and provider-guided nutrition remain the most dependable starting point, with medication options like Semaglutide or Tirzepatide sometimes entering the conversation later, once breastfeeding status and recovery allow it. This mirrors how most healthcare providers currently approach postpartum weight questions, following established clinical practices rather than newer, still-developing research.

Breastfeeding And Retatrutide: What Providers Consider

One of the most common questions new mothers ask is whether a medication like Retatrutide is safe to use while breastfeeding. At this time, there is not enough research to answer that question with confidence. Because Retatrutide is still investigational, studies specifically examining whether it passes into breast milk, and what effect that might have on an infant, have not been completed or published in a way that allows for a clear safety recommendation.

This is a case where general caution applies. Newer medications, even ones that appear promising in adult weight management studies, are typically not recommended during breastfeeding until enough data exists to understand any potential risk to a nursing infant. A helpful outside resource that summarizes how medication safety during breastfeeding is generally evaluated can be found through Healthline’s overview of breastfeeding and medication safety, which explains the broader framework providers use when weighing these decisions, even though it does not address Retatrutide specifically since the medication is so new.

For mothers who are breastfeeding and interested in weight management now rather than waiting, providers often discuss nutrition timing, activity levels appropriate for postpartum recovery, and, when medically appropriate, established options rather than investigational ones.

Getting Started

Mothers who want to explore weight management options after childbirth typically start with a visit to their primary care provider or OB-GYN. That conversation should include current breastfeeding status, any complications from delivery, mental health history, and overall health goals. From there, a provider can walk through what options make sense, whether that means nutrition counseling, a referral to a specialist, or, once appropriate, a conversation about medication.

Final Thoughts On Retatrutide For Postpartum Weight Loss

Retatrutide for postpartum weight loss remains a research topic rather than an established treatment path, and the most reliable approach for new mothers today still centers on rest, nutrition, gradual activity, and open communication with a healthcare provider.

As triple-hormone agonist research continues to develop, more clarity may eventually emerge about how compounds like Retatrutide interact with postpartum recovery and breastfeeding, but that clarity is not available yet.

Mothers exploring their options in the meantime can learn more through related reading on Retatrutide’s studied benefits, how Retatrutide works in the body, and how Retatrutide compares to Tirzepatide. For established weight management medications that providers may discuss once breastfeeding and recovery allow, options such as Mounjaro, Zepbound, and Wegovy are worth discussing with a provider directly.

Frequently Asked Questions About Retatrutide For Postpartum Weight Loss

Can you take Retatrutide after birth?

There is no established protocol for taking Retatrutide after birth. It remains investigational, and any use should only happen under direct guidance from a licensed healthcare provider who has reviewed a mother’s full recovery and health history.

What is the best weight loss after giving birth?

Gradual, nutrition-focused weight loss paired with rest and light activity tends to work best after giving birth. Most healthcare providers recommend waiting until healing is well underway before adding structured exercise or considering medication.

Can I take reta peptides while breastfeeding?

Current research has not established whether Retatrutide is safe during breastfeeding. Because data is limited, most providers advise against using investigational peptides while nursing until more safety information becomes available.

What medication is used for postpartum weight loss?

There is no medication specifically approved for postpartum weight loss. Providers sometimes discuss established options like Semaglutide or Tirzepatide once breastfeeding status and physical recovery allow, based on individual evaluation.

What are the best peptides for postpartum?

No peptide has been established as a standard, recommended option for postpartum use. Investigational compounds like Retatrutide require further research before providers can offer clear postpartum-specific guidance.

Sources

  1. American College of Obstetricians and Gynecologists Journal (Obstetrics & Gynecology): Peer-reviewed research on postpartum recovery, weight retention patterns, and maternal health guidance.
  2. Journal of Clinical Endocrinology & Metabolism: Published research on GLP-1, GIP, and glucagon receptor agonists and their metabolic effects.
  3. Mayo Clinic: Patient-facing overview of postpartum weight loss, recovery timelines, and general nutrition guidance.
  4. Cleveland Clinic: Clinical overview of incretin-based medications, including triple-hormone receptor agonists in development.
  5. Academy of Nutrition and Dietetics: Guidance on nutritional needs during breastfeeding and postpartum recovery.

Medical Disclaimer: This content is for informational purposes only and is not intended as medical advice. It is not a substitute for professional consultation, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or changing any medication or treatment plan, particularly during pregnancy, postpartum recovery, or breastfeeding.


Retatrutide Subcutaneous Injection: What Patients Should Know Before Starting Treatment

Medically Reviewed by Dr. Priya Nathan, MD, Endocrinology | Last Updated: July 2026

Retatrutide subcutaneous injection is the administration route used in current research on this investigational triple-agonist peptide, delivering the compound into the fatty tissue layer just beneath the skin. Because Retatrutide remains investigational and is not yet approved for routine self-administration, every aspect of dosing and injection technique is handled under direct provider oversight rather than through independent trial and error at home.

Key Takeaways

  • Retatrutide subcutaneous injection refers to delivery into the subcutaneous fat layer, the same general route used for other GLP-1 and GIP-based peptide therapies
  • Retatrutide is still investigational, so administration decisions, including technique and site selection, are directed by a licensed provider rather than self-taught
  • Common subcutaneous sites used in clinical research settings include the abdomen, thigh, and upper arm
  • Absorption through subcutaneous tissue is generally slower and steadier than intramuscular or intravenous delivery, which supports a more gradual release profile
  • Patients considering Retatrutide should expect provider-guided scheduling, monitoring, and technique review rather than a standardized home-injection kit

Why Retatrutide Subcutaneous Injection Is the Standard Administration Route

Peptide compounds like Retatrutide are structured as proteins, which means they cannot be taken orally without breaking down in the digestive tract before reaching the bloodstream. Subcutaneous delivery bypasses this problem entirely by placing the compound directly into the fatty layer beneath the skin, where a dense network of small blood vessels gradually absorbs it into circulation.

This is the same general mechanism used across the GLP-1 and dual or triple agonist category, including approved options like Mounjaro Kwikpen and Zepbound Kwikpen. The subcutaneous route allows for a slower, more sustained release compared to intramuscular or intravenous administration, which is part of why these medications are typically dosed weekly rather than daily.

Retatrutide Subcutaneous Injection

Things To Know

  • Subcutaneous tissue has fewer nerve endings than muscle, which is part of why this route tends to be more comfortable for weekly dosing schedules
  • Retatrutide’s investigational status means dosing protocols, injection frequency, and technique are still being refined through ongoing research rather than fixed by long-standing clinical practice
  • A provider reviewing injection technique in person catches issues, like improper site rotation or angle, that are easy to miss when learning from written instructions alone

How Subcutaneous Absorption Works in the Body

Once a compound is placed into the subcutaneous layer, it does not enter the bloodstream immediately. Instead, capillaries in the fatty tissue absorb it gradually over hours, which is what allows for the extended dosing intervals seen with this drug class. This is different from an intramuscular injection, where absorption happens faster because muscle tissue has a richer blood supply.

Patients working with a prescribing provider often ask why the injection site matters at all if the medication eventually reaches the same bloodstream regardless of location. In practice, providers note that absorption rate can vary slightly between common sites, which is one reason site selection and rotation are part of the broader administration plan a provider builds around each patient rather than a detail left to guesswork.

Administration Route Absorption Speed Typical Use Case
Subcutaneous Slow and steady Weekly peptide therapies, insulin, GLP-1 and GIP agonists
Intramuscular Faster Vaccines, certain antibiotics
Intravenous Immediate Hospital settings requiring rapid effect


Common Subcutaneous Sites Used in Clinical Research Settings

Across the broader category of injectable peptide therapies, three general body areas are typically used for subcutaneous administration. These are not unique to Retatrutide but reflect standard practice for this route across the drug class.

Injection Site General Characteristics
Abdomen Widely used site with a consistent fat layer, avoiding the area directly around the navel
Thigh Front or outer thigh, often preferred for self-visibility during provider-guided sessions
Upper arm Back of the upper arm, sometimes harder to reach without assistance


A provider will typically walk a patient through which site fits their body type, activity level, and comfort, and will explain why rotating between sites over time supports tissue health. This kind of individualized guidance is part of why Retatrutide subcutaneous injection protocols in research settings are always paired with clinical supervision rather than a one-size-fits-all handout.

Why Provider Oversight Matters for an Investigational Compound

Retatrutide has not completed the same regulatory pathway as established medications, which changes how administration is approached. Providers who work with patients considering Retatrutide typically spend more time on technique review, site rotation planning, and monitoring for injection-site reactions than they might with a long-established therapy, precisely because the safety and dosing profile is still being defined through ongoing research.

Most healthcare providers follow established clinical protocols when overseeing injectable peptide therapies, adapting monitoring and follow-up based on how new compounds like Retatrutide compare to better-characterized options already on the market, such as Ozempic or Wegovy. This is also why dosing figures referenced in research, such as 2mg, 4mg, 8mg, or 9mg, are treated as research reference points rather than a fixed at-home dosing chart, and why any decision about a specific milligram amount belongs in conversation with a prescribing provider rather than in a general article.

External resource: For general patient education on subcutaneous injection anatomy and technique across drug classes, MedlinePlus offers a plain-language overview of subcutaneous injection basics.

Which Approach Is Right: Why, How, and What Applies

The “why” behind subcutaneous administration is straightforward: it is the only practical delivery method for a peptide compound that would otherwise be broken down before reaching the bloodstream. The “how” is where individualization matters most, since site selection, rotation schedule, and timing are shaped by a patient’s body composition, daily routine, and how their provider is monitoring the investigational treatment. The “which” question, meaning which specific approach applies to a given patient, is not something a general guide can answer responsibly. That determination sits with the prescribing provider, who weighs the patient’s full health picture against what current research on Retatrutide actually supports.

Patients who are also comparing options across the broader category often find it helpful to look at how Retatrutide differs from Tirzepatide or to review the researched benefits associated with Retatrutide before a consultation, so the conversation with a provider starts from an informed baseline rather than from scratch.

Why Retatrutide Subcutaneous Injection Is the Standard Administration Route

Timing and Scheduling Considerations

Weekly dosing schedules are common across this medication category, and providers generally recommend choosing a consistent day and time that fits a patient’s routine, since consistency supports steadier absorption patterns over the following days. Some patients prefer scheduling around a day off from work, in case they experience mild, temporary injection-site tenderness. Others simply pick whichever day is easiest to remember, like a Sunday evening.

A provider will also account for how a chosen schedule interacts with any other medications or appointments, which is part of the broader monitoring plan built around an investigational compound like Retatrutide. Patients exploring how this compares to more established weekly injectables sometimes review what Retatrutide actually does in the body as background before their first consultation.

Getting Started With a Provider

Better You Rx operates as a prescription referral service with a licensed contracted dispensing department, connecting patients with providers who can evaluate whether a treatment like Retatrutide fits their overall health picture. Because this compound is investigational, the process typically begins with a consultation focused on medical history, current medications, and treatment goals, rather than a direct request for a specific product.

Patients interested in established, already-approved weekly injectable options while discussing Retatrutide with a provider often review products like Mounjaro Kwikpen, Zepbound Kwikpen, or Saxenda as points of comparison during that same conversation.

Things To Know Before Your First Consultation

  • Bring a full list of current medications and supplements, since some can interact with peptide therapies
  • Ask your provider directly about site rotation, since reusing the same spot repeatedly can affect tissue over time
  • Mention any history of needle anxiety in advance, since providers can adjust the pace of the first session accordingly
  • Keep track of which day you dosed, since consistency matters more than the exact hour

Bringing It All Together

Subcutaneous administration remains the foundation of how Retatrutide is used in current research, and every meaningful decision beyond that basic fact, from site selection to timing to technique, belongs in a conversation with a licensed provider rather than a general reference article. Patients weighing Retatrutide subcutaneous injection against more established options can start that conversation informed, but the specifics of their own treatment plan will always come down to individualized medical guidance.

Patients researching cost and access considerations across GLP-1 therapies may also find it useful to review how Trulicity compares to Mounjaro as part of understanding the broader weekly injectable landscape before their consultation.

Frequently Asked Questions

Should Retatrutide be injected subcutaneously?

Yes, subcutaneous is the administration route used in current research on Retatrutide. It allows the compound to absorb gradually through the fatty layer beneath the skin, and any specific injection decision should be guided directly by a prescribing provider given the compound’s investigational status.

Where is the best place to inject Retatrutide?

The abdomen, thigh, and upper arm are the general sites used across this medication category. A provider will help determine which site and rotation pattern fits an individual patient’s body type and comfort level.

How to inject Retatrutide with a syringe?

Technique should be demonstrated and reviewed in person by a licensed provider, not learned from a written guide. Because Retatrutide is investigational, hands-on instruction ensures proper handling, angle, and site care specific to each patient.

What is the correct technique for subcutaneous injection?

Correct technique depends on individual factors like body composition and the specific product, and should be taught directly by a healthcare provider. General subcutaneous principles include using the fatty tissue layer rather than muscle, but exact steps are provider-guided.

When is the best time to inject Retatrutide?

Most patients are guided toward a consistent day and time each week that fits their routine. A provider will help select timing that also accounts for any other medications or monitoring needs.

Medical Disclaimer: This article is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Retatrutide is an investigational compound, and readers should consult a licensed healthcare provider before considering any treatment involving it or any other prescription medication.

Sources

  • The New England Journal of Medicine — Clinical trial data on triple-agonist peptide compounds and metabolic outcomes.
  • Mayo Clinic — Patient education overview of subcutaneous injection technique and injectable medication classes.
  • MedlinePlus (National Library of Medicine) — Plain-language patient instructions for subcutaneous injection basics.
  • The Lancet — Peer-reviewed research on GLP-1 and GIP receptor agonist mechanisms of action.
  • Journal of Diabetes Science and Technology — Comparative research on subcutaneous absorption rates across injection sites.

Retatrutide Injection Technique: What Patients Should Know Before Starting Treatment

Medically Reviewed by Dr. A. Santos, MD | Updated: July 2026

Last Updated: July 2026

Retatrutide injection technique is not something patients are expected to figure out alone. Because Retatrutide is still an investigational treatment being studied for weight management and metabolic support, every aspect of how it is administered is handled directly between a patient and their prescribing provider. This is different from many well-established injectable medications, where general public guidance is more widely available.

Patients researching this topic are often looking for reassurance that there is a right way and a wrong way to approach treatment, and that reassurance is fair. There is a right way. It just comes from a licensed medical professional who has reviewed the individual’s health history, not from a generic walkthrough.

Key Takeaways

  • Retatrutide injection technique is taught directly by a licensed provider, not through self-guided instructions, since Retatrutide remains an investigational compound
  • Proper technique centers on consistent site rotation, timing, and follow-up with the prescribing provider rather than independent trial and error
  • Getting the best results depends more on consistency and provider communication than on any single injection habit
  • Concerns about depth, angle, or comfort during injections should always be directed to the prescribing provider rather than answered through general guides
  • Working with a provider throughout treatment reduces the chances of technique-related issues and keeps dosing aligned with the individualized plan

Why Injection Technique Matters More With Investigational Treatments

Any injectable treatment carries some degree of risk if administered incorrectly, but that risk is elevated when a compound is still investigational. Established medications typically come with standardized patient materials refined over years of real-world use. Retatrutide does not yet have that same body of public-facing guidance, which is exactly why providers take a more hands-on role.

Healthcare providers who work with patients on Retatrutide typically walk through the process in person during an initial visit, then confirm technique again at follow-up appointments. This reflects established clinical practice for handling compounds still under active study.

Patients often report feeling more confident after that first supervised session than after reading any amount of written material, simply because a provider can watch their technique and correct small habits in real time.

The Role of the Prescribing Provider

The prescribing provider is the only appropriate source for the specific mechanics of Retatrutide injection technique. This includes decisions about site selection, rotation schedule, and how to handle any discomfort or unusual reactions. A provider factors in body composition, prior injection experience, and overall treatment plan, none of which a general article can account for.

Patients should feel comfortable asking questions at every visit, including ones that might seem basic. Providers expect these questions and generally welcome them, since a patient who fully understands their technique is less likely to run into avoidable issues.

Retatrutide Injection Technique What Patients Should Know Before Starting Treatment

What General Injection Care Looks Like

While the specific technique for Retatrutide is provider-directed, there are broad categories of injection care that apply across most injectable treatments and are worth understanding in general terms.

Category General Consideration Why It Matters
Site rotation Providers typically recommend rotating between a few approved areas Reduces irritation and supports consistent absorption
Timing consistency Many treatment plans favor a similar time of day or week Helps maintain a steady routine the patient can follow
Storage handling Providers give specific storage instructions for the prescribed product Protects the integrity of the medication between uses
Follow-up check-ins Regular appointments allow technique review Catches small habits before they become patterns

This table reflects general categories only. The specific instructions a patient receives will always come from their own provider and may differ based on individual circumstances.

Things To Know

  • Retatrutide is still being studied, which is why self-administration instructions are intentionally left out of general health content
  • Providers usually demonstrate technique in person before a patient administers a first dose independently
  • Comfort and confidence with injections tend to improve after the first few provider-supervised sessions
  • Any unusual reaction at an injection site should be reported to the provider rather than managed independently
  • Retatrutide injection technique will look slightly different for each patient depending on their individualized treatment plan

How Patients Get the Best Results With Retatrutide

The patients who tend to have the smoothest experience are not necessarily the ones with the most injection experience. They are usually the ones who stay consistent with their provider check-ins and follow their individualized plan closely.

Consistency matters more than any single habit. Sticking to the schedule a provider outlines, keeping appointments, and reporting any concerns promptly all contribute more to a positive experience than small variations in personal preference. Providers commonly observe that patients who ask questions early, rather than waiting until something feels off, have fewer complications overall.

Lifestyle factors also play a supporting role. Adequate hydration, following any dietary guidance provided alongside treatment, and maintaining regular sleep patterns all support how a patient responds to their overall plan. None of these factors replace medical guidance, but they work alongside it.

For patients comparing options, understanding what does Retatrutide do and reviewing Retatrutide vs Tirzepatide can offer helpful context before a first consultation.


What General Injection Care Looks LikeCommon Questions Patients Bring to Their Provider
Patients frequently want to know whether their technique matches what is expected, whether mild discomfort is normal, and how to know if something needs attention. A provider is best positioned to answer these, since the response often depends on the individual’s specific plan and history.

Patient Question Type Best Answered By Reason
Technique specifics (angle, depth, pinching) Prescribing provider Depends on individual anatomy and plan
Reconstitution details Prescribing provider or contracted dispensing team Requires precise, individualized instruction
General comfort or timing preferences Prescribing provider Adjusts based on patient feedback over time
Site reaction concerns Prescribing provider May require an in-person evaluation

Patients exploring related metabolic treatments sometimes also review Retatrutide benefits to better understand the broader treatment goals before their first appointment.

Working With a Prescription Referral Service

Better You Rx operates as a prescription referral service with a licensed contracted dispensing department, connecting patients with the medications their provider has prescribed. Patients interested in exploring GLP-1 and related metabolic treatment options can review products such as Mounjaro, Zepbound, or Saxenda alongside a conversation with their provider about whether Retatrutide fits their individualized plan.

Prescriptions must come from a primary care physician or licensed medical doctor practicing in the USA, and all documentation must be issued in English. This keeps the referral and dispensing process aligned with each patient’s own medical team, which is especially important for a treatment still under investigation.

Final Thoughts on Retatrutide Injection Technique

Retatrutide injection technique is one of the clearest examples of why investigational treatments call for a closer relationship with a prescribing provider rather than a self-guided approach. The mechanics of administration, from site selection to timing, are worked out between patient and provider, adjusted as needed, and revisited at follow-up visits.

Patients who lean on their provider rather than piecing together instructions from scattered sources tend to feel more settled in their routine and better equipped to notice when something needs a second look. That collaborative approach is really the heart of getting Retatrutide injection technique right.

Frequently Asked Questions

What is the correct injection technique?

The correct technique is demonstrated directly by the prescribing provider during an in-person visit, based on the patient’s individualized plan, not through general instructions.

How is Retatrutide mixed before use?

Mixing and reconstitution steps are handled or explained directly by the prescribing provider or the licensed contracted dispensing team, since precise handling matters for an investigational compound.

How can patients get the best results from Retatrutide?

Consistency with the provider’s plan, regular follow-up appointments, and prompt communication about any concerns lead to the best outcomes.

Is injection technique something a provider walks patients through?

Yes. Providers typically demonstrate technique in person before a patient administers any dose independently.

What should a patient do if something feels off during or after an injection?

Any discomfort, unusual reaction, or uncertainty should be reported to the prescribing provider promptly rather than managed alone.

Medical Disclaimer: This content is for informational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a licensed healthcare provider before starting, stopping, or making any changes to a medication or treatment plan, particularly with investigational compounds such as Retatrutide.

Sources:

  1. New England Journal of Medicine — Clinical trial data on GLP-1 and multi-agonist receptor treatments for weight management.
  2. Mayo Clinic — General patient education on injectable medication administration and site care.
  3. Journal of Clinical Endocrinology & Metabolism — Research on incretin-based investigational therapies for metabolic conditions.
  4. Cleveland Clinic — Patient guidance on working with prescribers during investigational or newly introduced treatments.
  5. American Diabetes Association Clinical Compendium — Reference material on injectable therapy management and patient follow-up practices.


What Does A Retatrutide Weekly Injection Schedule Look Like?

Written by Sarah Collins, Clinical Content Writer | Medically Reviewed by Dr. Amanda Reyes, MD | Last Updated: July 2026

A Retatrutide weekly injection schedule means administering one injection every week, on a day that stays fairly consistent from week to week, with the specific amount set and adjusted by a provider based on tolerability and progress. This once-weekly rhythm is common across several investigational and approved metabolic compounds, and it exists to keep blood levels steady rather than causing the peaks and dips that more frequent dosing can create. Understanding how this weekly pattern works, and why consistency matters more than the exact day chosen, helps patients build a routine that supports their broader treatment plan and reduces unnecessary guesswork week to week.

Key Takeaways

  • A Retatrutide weekly injection schedule involves one injection per week, with the amount determined and adjusted by a provider over time
  • Consistency in timing each week matters more than the exact day or hour chosen, since a stable weekly rhythm supports steadier results
  • Retatrutide remains an investigational compound, so injection amounts follow an individualized titration path rather than a fixed public standard
  • Missing an occasional dose does not automatically undo progress, but any changes to the schedule should be discussed with a provider
  • Working with a provider familiar with GLP-1, GIP, and glucagon receptor compounds helps ensure the weekly routine stays safe and appropriate

Retatrutide Weekly Injection

Why Retatrutide Follows A Weekly Rather Than Daily Pattern

The once-weekly design behind a Retatrutide weekly injection schedule comes down to how the compound is metabolized in the body. Compounds built for weekly administration are formulated to release gradually, maintaining a steady level of activity across receptor pathways for several days at a time. This is different from medications that need to be taken daily to maintain consistent effects, and it is part of why weekly dosing has become a common format across several newer metabolic treatments.

Because Retatrutide acts on three separate receptor pathways, GLP-1, GIP, and glucagon, a steady weekly rhythm helps avoid the kind of fluctuation that could otherwise affect tolerability. Providers generally recommend picking a day of the week that fits naturally into a patient’s routine, since a predictable pattern makes it easier to remember and reduces the chance of accidentally skipping a dose. Choosing a day tied to an existing weekly habit, such as meal prep on Sundays or a weekly grocery run, often works better than picking a day arbitrarily.

There is also a practical benefit to the weekly format beyond convenience. Because each dose is designed to remain active over several days, small variations in exact timing, injecting a few hours earlier or later than usual, tend to have far less impact than they would with a medication that needs to be taken at precise daily intervals. This built-in flexibility is one of the reasons providers describe the weekly structure as more forgiving for patients juggling busy schedules.

A Sample Weekly Structure

While the exact amount and timing of any Retatrutide weekly injection schedule is always determined individually by a provider, the general weekly structure tends to follow a consistent shape.

Weekly Element General Guidance Why It Matters
Injection Frequency Once every seven days Maintains steady receptor activity between doses
Day Selection Same day each week Reduces the chance of missed or delayed doses
Time of Day Consistent, but flexible Supports habit formation rather than strict timing
Amount Set and adjusted by provider Based on tolerability and titration stage
Site Rotation Rotating injection sites weekly Supports skin comfort and consistent absorption

This structure reflects general practice rather than a fixed protocol, since the specific amount and any adjustments to timing are always guided by the prescribing provider based on individual response. Some patients settle into this rhythm within the first few weeks, while others take a bit longer to find a day and time that consistently works with their schedule, and that adjustment period is entirely normal.

Things To Know

  • A Retatrutide weekly injection schedule works best when the same general day is used consistently, even if the exact hour shifts slightly
  • Rotating injection sites each week, such as alternating between the abdomen, thigh, and upper arm, can support comfort and more consistent absorption over time
  • The amount injected each week is set by a provider and typically increases gradually during titration, not on a fixed weekly basis
  • Occasional questions about timing, storage, or technique are common and worth bringing directly to a provider rather than guessing
  • Patients who keep a simple weekly log of injection day and any side effects often find it easier to have productive conversations with their provider at follow-up visits
  • Storing supplies in a consistent, visible location can reduce the chance of a missed dose simply due to forgetfulness

How Providers Approach Timing And Consistency

Providers generally emphasize that the specific day chosen for a Retatrutide weekly injection schedule matters less than sticking with that day consistently. A patient who injects every Sunday morning, for example, is building a routine that is easy to remember and track, which in turn makes it easier to notice if a dose has been missed or delayed.

In clinical practice, providers often observe that patients who anchor their injection to an existing weekly habit, such as a specific morning routine or a recurring day off work, tend to maintain their schedule more reliably than those who try to inject at a different time each week. This small structural choice can meaningfully reduce the number of missed or delayed doses over the course of a longer titration period. Most healthcare providers follow established clinical protocols when guiding patients on injection timing, prioritizing steady adherence over strict precision to the hour.

Patients exploring related options such as Mounjaro or Ozempic may notice that weekly dosing patterns are common across several metabolic compounds, though each has its own specific guidance that a provider will tailor to the individual. Some patients transitioning between compounds ask whether the weekly day needs to change, and this is another detail best confirmed directly with a provider rather than assumed.

What Happens If A Dose Is Delayed Or Missed

Life occasionally interferes with even the most consistent weekly routines, and providers generally have specific guidance for what to do if a dose within a Retatrutide weekly injection schedule is delayed by a day or two versus missed entirely. In many cases, a brief delay can be managed by administering the dose as soon as it is remembered, then resuming the regular weekly day going forward. A longer gap may call for a different approach, depending on how much time has passed and where the patient is in their titration process.

Because these situations depend heavily on individual circumstances, providers strongly discourage guessing or making adjustments independently. A quick conversation with a provider or their care team is generally the safest way to handle a missed or delayed dose, rather than assuming the same guidance that applies to another medication or another patient’s situation applies universally. Travel, illness, and simple forgetfulness are among the most common reasons patients report a missed or delayed dose, and providers are generally well prepared to help patients get back on a steady schedule without unnecessary worry.

Comparing Weekly Dosing Across Compounds

Several metabolic compounds share a similar weekly injection structure, though the specific amounts, titration pace, and individual guidance differ across each option.

Compound Injection Frequency Primary Mechanism
Retatrutide Once weekly, provider-determined amount GLP-1, GIP, and glucagon receptor activity
Tirzepatide Once weekly, provider-determined amount GLP-1 and GIP receptor activity
Semaglutide Once weekly, provider-determined amount GLP-1 receptor activity

This comparison shows that while the weekly rhythm itself is fairly consistent across these compounds, the appropriate amount and the pace of any increases depend entirely on which compound a provider has selected and how an individual patient responds. There is no universal weekly amount that applies across compounds or patients, only the specific plan a provider builds around one person’s needs.

For readers researching related topics, comparing Retatrutide and Tirzepatide or reviewing documented Retatrutide side effects can add helpful context before a provider conversation, along with a closer look at Retatrutide’s potential benefits for patients weighing their overall options.

What Happens If A Dose Is Delayed Or Missed

Building A Routine That Supports The Full Treatment Plan

A Retatrutide weekly injection schedule works best when it fits naturally into a patient’s broader week rather than feeling like an extra task to remember. Many patients find it helpful to pair the injection with an existing habit, keep supplies stored in a visible and consistent location, and note the injection date somewhere easy to reference, whether that is a phone reminder or a simple paper calendar.

Beyond the injection itself, a supportive weekly routine often includes checking supply levels ahead of time, confirming the next injection site rotation, and briefly noting how the previous week felt in terms of appetite, energy, or any mild digestive symptoms. This kind of light, ongoing tracking gives both the patient and provider useful information without requiring extensive daily effort.

Better You Rx works within a prescription referral model, connecting patients with providers and a licensed contracted dispensing department, and does not set or recommend individual dosing schedules, since those decisions always rest with the prescribing provider based on each patient’s specific circumstances.

Practical Tips For Staying Consistent Week To Week

Small habits tend to make the biggest difference in maintaining a reliable Retatrutide weekly injection schedule over the long term. Setting a recurring phone reminder for the chosen injection day, rather than relying on memory alone, is one of the simplest ways patients avoid accidental delays. Keeping an extra alcohol swab and a sharps container within easy reach of the storage location also removes small friction points that can otherwise turn a quick weekly task into something patients put off.

Some patients find it useful to link their injection to a specific weekly event they already track, such as a recurring calendar appointment, a weekly grocery trip, or a regular check-in with a workout partner. Anchoring the injection to something already happening on a predictable day tends to work better than trying to remember an isolated task in the middle of a busy week. Providers often ask about these small logistical details during early follow-up visits, since patients who have a workable system in place from the start tend to have fewer questions about missed or delayed doses later in treatment.

Travel and schedule changes are among the most common disruptions to a weekly routine. Patients who plan ahead before a trip, confirming storage requirements and packing supplies with enough buffer time, generally avoid the scramble of trying to figure out logistics at the last minute. A provider can offer specific guidance on how to handle travel across time zones or extended trips where the usual weekly day might shift slightly.

Keeping The Weekly Routine On Track

A consistent Retatrutide weekly injection schedule is one of the simpler parts of an overall treatment plan to manage once a routine is established, but it still benefits from attention to timing, site rotation, and open communication with a provider about any missed doses or side effects. Patients who treat their weekly injection as a fixed part of their routine, rather than an afterthought, tend to report a smoother overall experience with fewer surprises along the way.

Anyone exploring related metabolic health resources can also review what Retatrutide does in the body or consider other provider-directed options such as Saxenda while discussing the full range of choices available for a personalized plan.

Frequently Asked Questions

How Many Times Should I Inject Retatrutide A Week?

Once per week is the standard pattern. The specific amount and day are set by a provider as part of an individualized titration plan.

How Many Units A Week Of Reta?

This varies entirely by individual titration stage. A provider determines the exact amount based on tolerability and treatment goals, so there is no single standard unit count.

How Much Weight Can I Lose In 4 Weeks On Retatrutide?

Results vary significantly between individuals. Early titration stages are focused on tolerability rather than maximum effect, and a provider can offer more specific guidance based on an individual’s plan.

Can I Skip A Week Of Retatrutide?

This should be discussed with a provider rather than decided independently. Guidance on delayed or missed doses depends on individual titration stage and timing.

Is 2Mg Of Retatrutide Enough?

This depends entirely on the individual patient and provider’s plan. What is considered adequate varies based on tolerability, response, and treatment goals.

Sources

  1. New England Journal of Medicine — Clinical research on triple-receptor agonist compounds and their metabolic effects.
  2. The Lancet Diabetes & Endocrinology — Peer-reviewed data on GLP-1, GIP, and glucagon receptor co-agonism in metabolic treatment research.
  3. Mayo Clinic — Overview of investigational weight management medications and general dosing principles.
  4. Cleveland Clinic — Patient education resources on GLP-1 and multi-receptor agonist therapies.
  5. Journal of Clinical Endocrinology & Metabolism — Research on titration strategies and injection administration in metabolic compound studies.

Medical Disclaimer: This content is provided for informational purposes only and is not intended as medical advice. It does not replace consultation with a licensed healthcare provider. Anyone considering Retatrutide or any other treatment should speak with a qualified medical professional to determine what is appropriate for their individual health needs before starting, adjusting, or discontinuing any medication.

Sign Up For Newsletter

Please enable JavaScript in your browser to complete this form.

Join 60.000+ Subscribers and get a new discount coupon on every Saturday.

Address

PO Box 29631, Mississauga RPO Central Parkway, ON L5A 4H2

Phone Number

1-647-576-2076

better you rx big letter logo

Discover convenience with Better You Rx, your trusted pharmacy-affiliated partner. We work with leading pharmacies to deliver prescriptions and over-the-counter medications right to your doorstep. Enjoy cost-effective solutions on a platform that’s easy to use. We focus on safety and efficacy in all products. Our dedicated team ensures a smooth experience. From ordering to delivery, we simplify your healthcare needs. Choose Better You Rx for reliable service and expert support. Trust us for all your medication requirements. Experience the ease of modern pharmacy care.

Categories

Operating Hours: 
10:00AM – 6:00PM CST
Monday – Friday

Our Payment Partners :

Copyright © 2026 BetteryouRX. All Rights Reserved.
Join The Waitlist Be among the first to know when becomes available.
Add to cart